
Impact of Serum Adiponectin Level on Insulin and hs-CRP in Patients with Type 2 Diabetes: A Case-Control Study
DOI:
https://doi.org/10.71079/ASIDE.IM.03182550Abstract
Introduction: Type 2 diabetes mellitus (T2DM) is marked by insulin resistance, hyperglycemia, and systemic inflammation. Adiponectin—a hormone produced mainly by adipose tissue—enhances insulin sensitivity and exhibits anti‐inflammatory properties. This study evaluated serum adiponectin and related metabolic markers in Iraqi patients with T2DM versus healthy controls.
Methods: In a case-control design, 84 Iraqi subjects were recruited (45 patients with T2DM and 39 controls). Fasting blood samples were obtained to measure adiponectin, insulin, high-sensitivity C-reactive protein (hs-CRP), fasting serum glucose (FSG), and Homeostatic Model Assessment-Insulin Resistance (HOMA-IR) using standardized ELISA and biochemical assays. Correlations between adiponectin and anthropometric parameters were also analyzed.
Results: Controls showed significantly higher serum adiponectin and insulin levels (p < 0.05) compared to patients with T2DM. In contrast, hs-CRP, FSG, and HOMA-IR were significantly elevated in the diabetic group (p < 0.05). Moreover, adiponectin demonstrated significant negative correlations with both height and weight among controls, with their lower body weight suggesting enhanced fatty acid oxidation.
Conclusions: These findings indicate that elevated adiponectin is associated with improved insulin sensitivity and reduced inflammatory markers. The data support the potential role of adiponectin in mitigating insulin resistance, hyperglycemia, and overweight risks in T2DM, warranting further investigation into its therapeutic utility.
Keywords:
Adiponectin, Insulin, hs-CRP, Type 2 Diabetes Mellitus (T2D), HOMA-IR, OverweightFull Text
Introduction
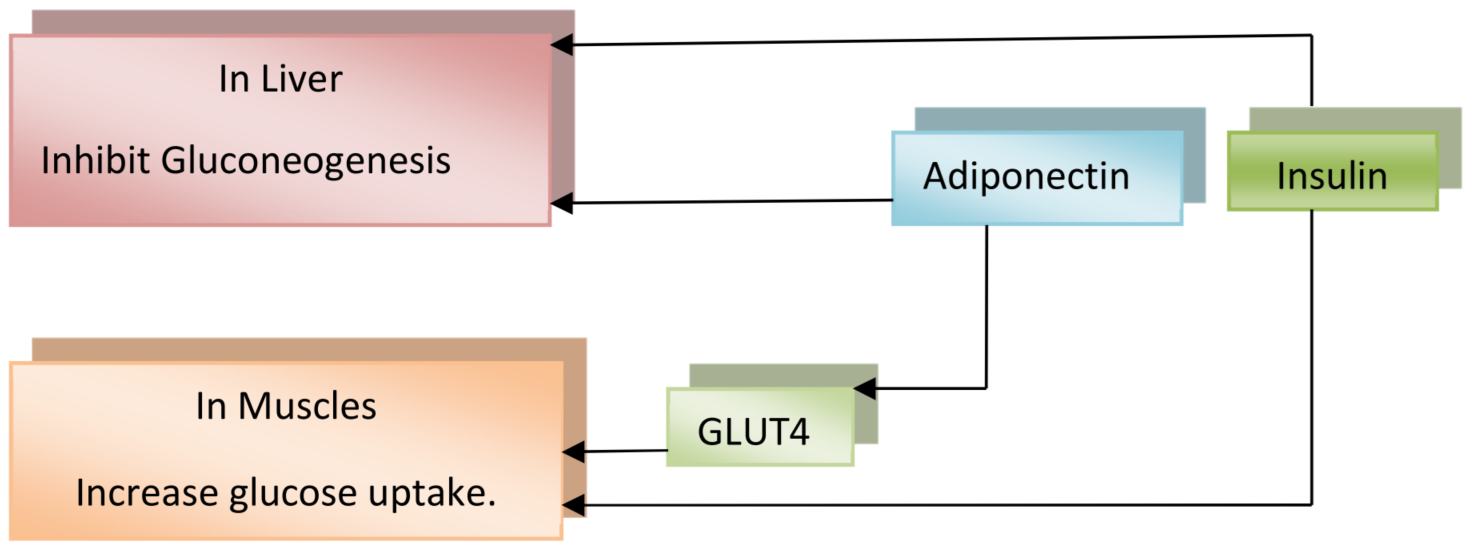
The prevalence of diabetes in 2021 had been reported to be about 537 million people and is expected to rise to 783 million in 2045 worldwide [1]. A conjugation of demographic and economic changes, with the association of large shifts in physical activity and dietary patterns, are properly considered a primary driver for the rise in diabetes in low- and middle-income countries [2]. Diabetes mellitus (DM) is a chronic disease causing insulin action resistance that leads to prolonged hyperglycemia besides metabolic disorders of lipids and protein [3]. Type 2 diabetes (T2DM), the most common type of DM, is characterized by an insulin resistance state that leads to a progressive decrease of adequate insulin secretion from -cells [4]. Many results show increased levels of Homeostatic Model Assessment-Insulin Resistance HOMA-IR and fasting serum glucose FSG in patients with diabetes when compared to non-diabetics [5]. Although an individual’s susceptibility to T2DM is determined by genetic predisposition, which is related to more than 88 genetic loci involved in susceptibility to T2DM [4], the increase in obesity, a sedentary lifestyle, industrialization, and energy-dense diets are responsible for making T2DM a widespread state [6]. Adiponectin was first described in 1995; it is a 30 kDa peptide generated in adipose tissues [7] exclusively produced by adipose tissue. Also, it is produced from skeletal muscles, cardiomyocytes, and endothelial cells [8]. The normal plasma level of 5–30 micrograms/ml [9]. There is a similarity between Adiponectin and Insulin in their effect on the liver and muscles concerning glucose metabolism, as shown in Figure 1. CRP is a 206-amino acid [10]. C-reactive protein (CRP) estimation is considered a marker for systemic inflammation [11]This study aims to estimate the serum levels of Adiponectin in relation to insulin, high-sensitivity C-reactive protein (hs-CRP), fasting serum glucose, and HOMA-IR in patients with T2DM compared with apparently healthy controls.
Methods
Study Design
A case-controlled study was conducted at The National Center for Diabetes, College of Medicine, Al-Mustansiriya University, Baghdad, Iraq. The patients with diabetes were selected from the outpatient clinic under the supervision of an endocrinologist from patients attending The National Center for Diabetes, Medicine College, Al Mutansryia University, Baghdad, Iraq. The selection criteria of patients listed in a questionnaire included having T2DM for at least 1 year, aged 18 years or older, and fasting over last night, while the exclusion criteria were malignant, endocrinopathy, renal, and chronic liver diseases. Eighty- four subjects included in the present study were categorized into two groups: Group-1 diabetic patients, including forty-five patients with diabetes (17 males and 28 females) aged between (25 and 44) years; Group-2 control subjects, including thirty-nine subjects (19 males & 20 females) aged between (30-65) years were chosen from the general population to be apparently healthy. A venous blood specimen (7ml) was withdrawn from each subject after an overnight fasting. The blood samples were placed into a gel tube (no anticoagulant) to permit clotting before centrifugation for 10 minutes. The obtained serum was stored as aliquots and was kept frozen at -20 °C until their assay for insulin, hs- CRP, and adiponectin by specific ELISA kits, besides measuring fasting serum glucose (FSG) in an automated Kenza 240 TX Biochemical autoanalyzer device. Weight and height were measured for eighty-four subjects Table 1.
| Analyte | Supplier |
|---|---|
| Glucose | BIOLABO Diagnostic / France |
| hs C-Reactive Protein | Demeditec Diagnostics / Germany |
| Insulin | Demeditec Diagnostics / Germany |
| Adiponectin | Shanghai Yehua Biological Technology Co., Ltd / China |
Statistical analysis
The results were expressed as (mean± standard deviation (SD) of mean). The Shapiro-Wilk test was conducted on all parameters to explore the normality of the data. The normally distributed variables were managed by t-test to compare the two studied groups. Pearson’s correlation coefficient (r) was run to find out the statistically significant correlations between measured parameters. A P-value less than 0.05 was accepted as a significant difference. The analyses were conducted using the Statistical Package for Social Science (SPSS), version 25. HOMA-IR was calculated based on the following equation: HOMA-IR =fasting serum glucose(mg/ml) × fasting serum insulin (U/ml)/405 [12].
Results
This study compared two groups: 45 patients with T2DM and 39 healthy controls. The T2DM patients were primarily middle-aged, with a mean age of 52.1 years (SD = 10.375), while the control group was younger, averaging 33.3 years (SD = 5.488), indicating a statistically significant age difference (p < 0.0001) Table 2. The analysis of body metrics showed that patients with T2DM had a higher mean weight of 83.088 kg (SD = 11.925) compared to 77.384 kg (SD = 14.401) in controls, with marginal statistical significance (p = 0.0502). However, the average height was comparable between groups—1.669 meters (SD = 0.095) for diabetics and 1.675 meters (SD = 0.089) for controls, which did not differ significantly (p = 0.7387) Table 2.
The biochemical profile revealed that FSG, hs-CRP, and HOMA-IR levels were significantly higher in the diabetic group (p < 0.05), while levels of fasting insulin and adiponectin were significantly lower compared to controls. Specifically, adiponectin levels were notably lower in T2DM patients at 14.848 µg/ml (SD = 7.790) versus 30.887 µg/ml (SD = 9.780) in controls (p < 0.0001) Table 2.
In addition, significant negative correlations were identified between adiponectin levels and both weight (r = -0.683, p = 0.001) and height (r = -0.740, p = 0.001) in the control group, underscoring the inverse relationship between adiponectin and body measurements in a healthy population Table 3.
| Parameter | ControlMean ± SD (n=39) | DMMean ± SD (n=45) | P-value |
|---|---|---|---|
| Age (year) | 33.333 ± 5.488 | 52.111 ± 10.375 | < 0.0001* |
| Gender (M/F) | 19/20 | 17/28 | NA |
| Weight (kg) | 77.384 ± 14.401 | 83.088 ± 11.925 | 0.0502 |
| Height (m) | 1.675 ± 0.089 | 1.669 ± 0.095 | 0.7387 |
| Disease duration (year) | NA | 6.42 ± 4.801 | NA |
| Adiponectin (µg/ml) | 30.887 ± 9.780 | 14.848 ± 7.790 | < 0.0001* |
| hs-CRP (µg/ml) | 5.492 ± 2.905 | 17.937 ± 5.979 | < 0.0001* |
| Insulin (µIU/ml) | 13.502 ± 6.165 | 8.411 ± 1.161 | < 0.0001* |
| FSG (mg/ml) | 90.0 ± 19.351 | 176.555 ± 38.927 | < 0.0001* |
| HOMA-IR | 2.991 ± 1.532 | 3.671 ± 0.955 | 0.0154** |
*= t-test (student test) significant at a level of p <0.05
**= t-test (student test) significant at a level of p <0.01
SD, Standard deviation; hs-CRP, high-sensitivity C-reactive protein; FSG, fasting serum glucose; HOMA-IR, Homeostatic Model Assessment-Insulin Resistance; M, Male; F, Female; NA, Not applicable.
| Variable | Pearson Correlation | Significance (Sig. 2-tailed) |
|---|---|---|
| Weight | -0.683** | 0.001 |
| Height | -0.740** | 0.001 |
**Correlation is significant at the 0.01 level (2-tailed).
Discussion
The significantly (P<0.05) higher FSG, hs-CRP, and HOMA-IR levels in patients with diabetes compared to the controls Table 2 may be explained by the hyperglycemia during type 2 diabetes participation in the inflammation process, which agrees with Wu et al. [13]This inflammation could lead to two effects: insulin resistance, as was found in Asimakidou et al. [14], and the significant (P<0.05) lowered adiponectin level, as agreed with El-Araby et al. [15]. The significantly (P<0.05) lowered level of insulin secretion in patients with diabetes could result from prolonged time exposure to the disease, which promotes hypo-insulinemia and hyperglycemia as -cells will be exhausted with time, agreeing with (Faraj et al.;2020) [16]Besides, people with diabetes age more than controls, as aging can cause a gradual loss of -cell mass, which agrees with Nasteska et al. [17].
The significant (P<0.05) higher adiponectin level with concurrent significant (P<0.05) higher insulin level in controls as compared to people with diabetes may come from the effect of adiponectin in increasing insulin sensitivity, which agrees with Wu et al. [18]. The significant (P<0.05) low levels of each of FSG, HOMA-IR, and hs-CRP in controls as compared to diabetics might be due to the anti-inflammatory effect of adiponectin, agreeing with Shimizu et al. [19]. It regulates glucose metabolism as adiponectin enhances glucose uptake in adipose and muscle tissues, as with Guo L et al [20]. The significant (P<0.05) negative correlation between adiponectin and weight with the concurrent significant (p<0.05) lower weight value in controls compared to diabetics could be a result of adiponectin’s influence in enhancing fatty acid oxidation [21], the same was found in Lara-Guzmán et al.[22]. The significant (P<0.05) negative correlation between adiponectin and height was also found by Norton et al., and they explained it on a genetic base [24] while disagreeing with Barnabé et al. [23]. The limited sample size of 84 individuals may restrict the findings’ generalizability to the larger Iraqi population. The sample may not entirely reflect the variety of the entire country. As a result, the findings may not accurately reflect the country’s overall image. Future studies should use bigger, nationally representative samples to improve the external validity of the findings.
Conclusions
Adiponectin can ameliorate diabetes mellitus, insulin resistance, and overweight risks as it can decrease the levels of glucose, hs-CRP, and HOMA-IR and enhance insulin sensitization and fatty acid oxidation, suggesting using adiponectin in the improvement of the risks of these cases. Therefore, a merit investigation is requested to pave the way for this finding.
Conflicts of Interest
The authors declare no competing interests that could have influenced the objectivity or outcome of this research.
Funding Source
This research received no specific grant from any funding agency in the public, commercial, or not-for-profit sectors.
Acknowledgments
The author would like to thank all employees in the National Center of Diabetes Treatment & Research, doctors, clinical chemistry laboratory staff, and diabetic patients for their ongoing assistance throughout data collection and all the people who helped to achieve this work.
Institutional Review Board (IRB)
The IRB of the College of Pharmacy at the University of Baghdad, Baghdad, Iraq, approved this study protocol, designated as number 839, on October 25, 2020.
Large Language Model
No generative artificial intelligence or large language model tools were used in the preparation of this manuscript.
Authors Contribution
HFJ and SHA were responsible for the study design, data collection, analysis, and manuscript writing; MSJ contributed to the critical revision of the manuscript for important intellectual content. All authors read and approved of the final manuscript.
Data Availability
The data supporting the findings of this study are available from the corresponding author upon reasonable request.
References
- Migdalis I. N.. Chronic Complications of Diabetes: Prevalence, Prevention, and Management. J Clin Med. 2024;13(23). doi:10.3390/jcm13237001 PMID: 39685460 PMCID: PMC11642689
- Seiglie J. A., Marcus M. E., Ebert C., Prodromidis N., Geldsetzer P., Theilmann M., Agoudavi K., Andall-Brereton G., Aryal K. K., Bicaba B. W., Bovet P., Brian G., Dorobantu M., Gathecha G., Gurung M. S., Guwatudde D., Msaidie M., Houehanou C., Houinato D., Jorgensen J. M. A., Kagaruki G. B., Karki K. B., Labadarios D., Martins J. S., Mayige M. T., Wong-McClure R., Mwangi J. K., Mwalim O., Norov B., Quesnel-Crooks S., Silver B. K., Sturua L., Tsabedze L., Wesseh C. S., Stokes A., Atun R., Davies J. I., Vollmer S., Barnighausen T. W., Jaacks L. M., Meigs J. B., Wexler D. J., Manne-Goehler J.. Diabetes Prevalence and Its Relationship With Education, Wealth, and BMI in 29 Low- and Middle-Income Countries. Diabetes Care. 2020;43(4):767-775. doi:10.2337/dc19-1782 PMID: 32051243 PMCID: PMC7085810
- Matalqah Sina M, Al-Tawalbeh Deniz M. Medicinal plants potential against diabetes mellitus. diabetes. 2025;9(10):11.
- Wang Y., Yang S., Guan Q., Chen J., Zhang X., Zhang Y., Yuan Y., Su Z.. Effects of Genetic Variants of Nuclear Receptor Y on the Risk of Type 2 Diabetes Mellitus. J Diabetes Res. 2019;2019:4902301. doi:10.1155/2019/4902301 PMID: 31205951 PMCID: PMC6530108
- Faris Raheem Mohanad, H. Ali Shatha, G. Shareef Laith. Impact of serum levels of vitamin D on lipid profiles, glycemic indices, and insulin resistance in obese type 2 diabetes patients: An observational study. F1000Research. 2022;11. doi:10.12688/f1000research.125191.1
- Namazi N., Moghaddam S. S., Esmaeili S., Peimani M., Tehrani Y. S., Bandarian F., Shobeiri P., Nasli-Esfahani E., Malekpour M. R., Rezaei N., Rezaei N., Arjmand B., Larijani B., Farzadfar F.. Burden of type 2 diabetes mellitus and its risk factors in North Africa and the Middle East, 1990-2019: findings from the Global Burden of Disease study 2019. BMC Public Health. 2024;24(1):98. doi:10.1186/s12889-023-16540-8 PMID: 38183083 PMCID: PMC10768242
- Pi Daming, Wang Junli, Zhao Mengjuan, Liu Mingyu, Zhang Yingxin, Qin Chaobin, Yang Liping, Yan Xiao, Nie Guoxing. Adiponectin and adiponectin receptors in common carp (Cyprinus carpio): Tissue distribution and their expressions in response to high-carbohydrate and high-lipid diets. Aquaculture Reports. 2022;27. doi:10.1016/j.aqrep.2022.101341
- Polak-Szczybylo E., Tabarkiewicz J.. The Influence of Body Composition, Lifestyle, and Dietary Components on Adiponectin and Resistin Levels and AR Index in Obese Individuals. Int J Mol Sci. 2025;26(1). doi:10.3390/ijms26010393 PMID: 39796247 PMCID: PMC11720087
- Akhtar Y., Nawaz S., Khan M. S., Habib S. H., Malik M. H., Fatima S.. Relationship Of Serum Adiponectin Levels With Glycaemic Status In Pregnant Women. J Ayub Med Coll Abbottabad. 2022;34(2):235-238. doi:10.55519/JAMC-02-9491 PMID: 35576278
- Chen To-Wen, Wang Chih-Hung, Kuo Feng-Chih, Lee Mel S., Lee Gwo-Bin. A dual-aptamer sandwich assay by detection of C-reactive protein in synovial fluid on an integrated microfluidic system for diagnosis of periprosthetic joint infection. Sensors and Actuators B: Chemical. 2025;424. doi:10.1016/j.snb.2024.136932
- Romero-Ferreiro V., Garcia-Fernandez L., Biscaia J. M., Romero C., Gonzalez-Soltero R., De la Fuente M., Alvarez-Mon M. A., Wynn R., Rodriguez-Jimenez R.. Effect of probiotics on C-reactive protein levels in schizophrenia: Evidence from a systematic review and meta-analysis. Complement Ther Med. 2025;89:103126. doi:10.1016/j.ctim.2025.103126 PMID: 39798817
- Biernacka-Bartnik A., Kocelak P., Owczarek A. J., Choreza P. S., Markuszewski L., Madej P., Puzianowska-Kuznicka M., Chudek J., Olszanecka-Glinianowicz M.. The cut-off value for HOMA-IR discriminating the insulin resistance based on the SHBG level in women with polycystic ovary syndrome. Front Med (Lausanne). 2023;10:1100547. doi:10.3389/fmed.2023.1100547 PMID: 36968815 PMCID: PMC10037532
- Wu M., Hao Y., Wu X., Zhu M., Chen X., Qi J., Yu Z., Xu H.. SirT7-mediated transcription of fascin in hyperglycemic glomerular endothelial cells contributes to EndMT in diabetic nephropathy. Acta Biochim Biophys Sin (Shanghai). 2024;56(4):586-596. doi:10.3724/abbs.2024002 PMID: 38449390 PMCID: PMC11090846
- Asimakidou E., Saipuljumri E. N., Lo C. H., Zeng J.. Role of metabolic dysfunction and inflammation along the liver-brain axis in animal models with obesity-induced neurodegeneration. Neural Regen Res. 2025;20(4):1069-1076. doi:10.4103/NRR.NRR-D-23-01770 PMID: 38989938 PMCID: PMC11438328
- El-Araby R. E., Tu Q., Xie Y., Aboushousha T., Li Z., Xu X., Zhu Z. X., Dong L. Q., Chen J.. Adiponectin mRNA Conjugated with Lipid Nanoparticles Specifically Targets the Pathogenesis of Type 2 Diabetes. Aging Dis. 2024;16(2):1059-1079. doi:10.14336/AD.2024.0162 PMID: 38916734 PMCID: PMC11964417
- Faraj M.. LDL, LDL receptors, and PCSK9 as modulators of the risk for type 2 diabetes: a focus on white adipose tissue. J Biomed Res. 2020;34(4):251-259. doi:10.7555/JBR.34.20190124 PMID: 32701068 PMCID: PMC7386410
- Nasteska D., Fine N. H. F., Ashford F. B., Cuozzo F., Viloria K., Smith G., Dahir A., Dawson P. W. J., Lai Y. C., Bastidas-Ponce A., Bakhti M., Rutter G. A., Fiancette R., Nano R., Piemonti L., Lickert H., Zhou Q., Akerman I., Hodson D. J.. PDX1(LOW) MAFA(LOW) beta-cells contribute to islet function and insulin release. Nat Commun. 2021;12(1):674. doi:10.1038/s41467-020-20632-z PMID: 33514698 PMCID: PMC7846747
- Wu W., Chen G., Zhang X., Wu H., Wang Y. E., Li X., Liang Y., Liu D.. The effect of long-term exposure to moderate high altitude on adipokines and insulin sensitivity. Cytokine. 2025;185:156823. doi:10.1016/j.cyto.2024.156823 PMID: 39626424
- Shimizu R., Suzuki H., Amitani M., Amitani H.. The Effects of Yoga on Key Adipocytokines in Obesity: A Narrative Review of Leptin and Adiponectin. Cureus. 2025;17(1):e76792. doi:10.7759/cureus.76792 PMID: 39897330 PMCID: PMC11786781
- Guo L., Jin K., Sun Q., Zhang C., Chen X., Geng Z.. Adiponectin regulates proliferation and differentiation of chicken skeletal muscle satellite cells via ERK1/2 and p38 signaling pathways. Poult Sci. 2025;104(2):104813. doi:10.1016/j.psj.2025.104813 PMID: 39823838 PMCID: PMC11786077
- Hafiane A.. Adiponectin-mediated regulation of the adiponectin cascade in cardiovascular disease: Updates. Biochem Biophys Res Commun. 2024;694:149406. doi:10.1016/j.bbrc.2023.149406 PMID: 38134479
- Lara-Guzman O. J., Arango-Gonzalez A. M., Alvarez-Quintero R., Escobar J. S., Munoz-Durango K., Sierra J. A.. Circulating hs-CRP, IL-18, Chemerin, Leptin, and Adiponectin Levels Reflect Cardiometabolic Dysfunction in Adults with Excess Weight. Int J Mol Sci. 2025;26(3). doi:10.3390/ijms26031176 PMID: 39940942 PMCID: PMC11818792
- Barnabe M. A., Elliott J., Harris P. A., Menzies-Gow N. J.. Relationships between total adiponectin concentrations and obesity in native-breed ponies in England. Equine Vet J. 2024;56(2):264-272. doi:10.1111/evj.14013 PMID: 37800870
- Baldelli S., Aiello G., Mansilla Di Martino E., Campaci D., Muthanna F. M. S., Lombardo M.. The Role of Adipose Tissue and Nutrition in the Regulation of Adiponectin. Nutrients. 2024;16(15). doi:10.3390/nu16152436 PMID: 39125318 PMCID: PMC11313710
References
1. Migdalis IN. Chronic Complications of Diabetes: Prevalence, Prevention, and Management. J Clin Med. 2024;13(23). [PMID: 39685460, PMCID: PMC11642689, https://doi.org/10.3390/jcm13237001].
2. Seiglie JA, Marcus ME, Ebert C, Prodromidis N, Geldsetzer P, Theilmann M, Agoudavi K, Andall-Brereton G, Aryal KK, Bicaba BW, Bovet P, Brian G, Dorobantu M, Gathecha G, Gurung MS, Guwatudde D, Msaidie M, Houehanou C, Houinato D, Jorgensen JMA, Kagaruki GB, Karki KB, Labadarios D, Martins JS, Mayige MT, Wong-McClure R, Mwangi JK, Mwalim O, Norov B, Quesnel-Crooks S, Silver BK, Sturua L, Tsabedze L, Wesseh CS, Stokes A, Atun R, Davies JI, Vollmer S, Barnighausen TW, Jaacks LM, Meigs JB, Wexler DJ, Manne-Goehler J. Diabetes Prevalence and Its Relationship With Education, Wealth, and BMI in 29 Low- and Middle-Income Countries. Diabetes Care. 2020;43(4):767-75. [PMID: 32051243, PMCID: PMC7085810, https://doi.org/10.2337/dc19-1782].
3. Matalqah SM, Al-Tawalbeh DM. Medicinal plants potential against diabetes mellitus. diabetes. 2025;9(10):11.
4. Wang Y, Yang S, Guan Q, Chen J, Zhang X, Zhang Y, Yuan Y, Su Z. Effects of Genetic Variants of Nuclear Receptor Y on the Risk of Type 2 Diabetes Mellitus. J Diabetes Res. 2019;2019:4902301. [PMID: 31205951, PMCID: PMC6530108, https://doi.org/10.1155/2019/4902301].
5. Faris Raheem M, H. Ali S, G. Shareef L. Impact of serum levels of vitamin D on lipid profiles, glycemic indices, and insulin resistance in obese type 2 diabetes patients: An observational study. F1000Research. 2022;11. [https://doi.org/10.12688/f1000research.125191.1].
6. Namazi N, Moghaddam SS, Esmaeili S, Peimani M, Tehrani YS, Bandarian F, Shobeiri P, Nasli-Esfahani E, Malekpour MR, Rezaei N, Rezaei N, Arjmand B, Larijani B, Farzadfar F. Burden of type 2 diabetes mellitus and its risk factors in North Africa and the Middle East, 1990-2019: findings from the Global Burden of Disease study 2019. BMC Public Health. 2024;24(1):98. [PMID: 38183083, PMCID: PMC10768242, https://doi.org/10.1186/s12889-023-16540-8].
7. Pi D, Wang J, Zhao M, Liu M, Zhang Y, Qin C, Yang L, Yan X, Nie G. Adiponectin and adiponectin receptors in common carp (Cyprinus carpio): Tissue distribution and their expressions in response to high-carbohydrate and high-lipid diets. Aquaculture Reports. 2022;27. [https://doi.org/10.1016/j.aqrep.2022.101341].
8. Polak-Szczybylo E, Tabarkiewicz J. The Influence of Body Composition, Lifestyle, and Dietary Components on Adiponectin and Resistin Levels and AR Index in Obese Individuals. Int J Mol Sci. 2025;26(1). [PMID: 39796247, PMCID: PMC11720087, https://doi.org/10.3390/ijms26010393].
9. Akhtar Y, Nawaz S, Khan MS, Habib SH, Malik MH, Fatima S. Relationship Of Serum Adiponectin Levels With Glycaemic Status In Pregnant Women. J Ayub Med Coll Abbottabad. 2022;34(2):235-8. [PMID: 35576278, https://doi.org/10.55519/JAMC-02-9491].
10. Chen TW, Wang CH, Kuo FC, Lee MS, Lee GB. A dual-aptamer sandwich assay by detection of C-reactive protein in synovial fluid on an integrated microfluidic system for diagnosis of periprosthetic joint infection. Sensors and Actuators B: Chemical. 2025;424. [https://doi.org/10.1016/j.snb.2024.136932].
11. Romero-Ferreiro V, Garcia-Fernandez L, Biscaia JM, Romero C, Gonzalez-Soltero R, De la Fuente M, Alvarez-Mon MA, Wynn R, Rodriguez-Jimenez R. Effect of probiotics on C-reactive protein levels in schizophrenia: Evidence from a systematic review and meta-analysis. Complement Ther Med. 2025;89:103126. [PMID: 39798817, https://doi.org/10.1016/j.ctim.2025.103126].
12. Baldelli S, Aiello G, Mansilla Di Martino E, Campaci D, Muthanna FMS, Lombardo M. The Role of Adipose Tissue and Nutrition in the Regulation of Adiponectin. Nutrients. 2024;16(15). [PMID: 39125318, PMCID: PMC11313710, https://doi.org/10.3390/nu16152436].
13. Guo L, Jin K, Sun Q, Zhang C, Chen X, Geng Z. Adiponectin regulates proliferation and differentiation of chicken skeletal muscle satellite cells via ERK1/2 and p38 signaling pathways. Poult Sci. 2025;104(2):104813. [PMID: 39823838, PMCID: PMC11786077, https://doi.org/10.1016/j.psj.2025.104813].
14. Biernacka-Bartnik A, Kocelak P, Owczarek AJ, Choreza PS, Markuszewski L, Madej P, Puzianowska-Kuznicka M, Chudek J, Olszanecka-Glinianowicz M. The cut-off value for HOMA-IR discriminating the insulin resistance based on the SHBG level in women with polycystic ovary syndrome. Front Med (Lausanne). 2023;10:1100547. [PMID: 36968815, PMCID: PMC10037532, https://doi.org/10.3389/fmed.2023.1100547].
15. Wu M, Hao Y, Wu X, Zhu M, Chen X, Qi J, Yu Z, Xu H. SirT7-mediated transcription of fascin in hyperglycemic glomerular endothelial cells contributes to EndMT in diabetic nephropathy. Acta Biochim Biophys Sin (Shanghai). 2024;56(4):586-96. [PMID: 38449390, PMCID: PMC11090846, https://doi.org/10.3724/abbs.2024002].
16. Asimakidou E, Saipuljumri EN, Lo CH, Zeng J. Role of metabolic dysfunction and inflammation along the liver-brain axis in animal models with obesity-induced neurodegeneration. Neural Regen Res. 2025;20(4):1069-76. [PMID: 38989938, PMCID: PMC11438328, https://doi.org/10.4103/NRR.NRR-D-23-01770].
17. El-Araby RE, Tu Q, Xie Y, Aboushousha T, Li Z, Xu X, Zhu ZX, Dong LQ, Chen J. Adiponectin mRNA Conjugated with Lipid Nanoparticles Specifically Targets the Pathogenesis of Type 2 Diabetes. Aging Dis. 2024;16(2):1059-79. [PMID: 38916734, PMCID: PMC11964417, https://doi.org/10.14336/AD.2024.0162].
18. Faraj M. LDL, LDL receptors, and PCSK9 as modulators of the risk for type 2 diabetes: a focus on white adipose tissue. J Biomed Res. 2020;34(4):251-9. [PMID: 32701068, PMCID: PMC7386410, https://doi.org/10.7555/JBR.34.20190124].
19. Nasteska D, Fine NHF, Ashford FB, Cuozzo F, Viloria K, Smith G, Dahir A, Dawson PWJ, Lai YC, Bastidas-Ponce A, Bakhti M, Rutter GA, Fiancette R, Nano R, Piemonti L, Lickert H, Zhou Q, Akerman I, Hodson DJ. PDX1(LOW) MAFA(LOW) beta-cells contribute to islet function and insulin release. Nat Commun. 2021;12(1):674. [PMID: 33514698, PMCID: PMC7846747, https://doi.org/10.1038/s41467-020-20632-z].
20. Wu W, Chen G, Zhang X, Wu H, Wang YE, Li X, Liang Y, Liu D. The effect of long-term exposure to moderate high altitude on adipokines and insulin sensitivity. Cytokine. 2025;185:156823. [PMID: 39626424, https://doi.org/10.1016/j.cyto.2024.156823].
21. Shimizu R, Suzuki H, Amitani M, Amitani H. The Effects of Yoga on Key Adipocytokines in Obesity: A Narrative Review of Leptin and Adiponectin. Cureus. 2025;17(1):e76792. [PMID: 39897330, PMCID: PMC11786781, https://doi.org/10.7759/cureus.76792].
22. Hafiane A. Adiponectin-mediated regulation of the adiponectin cascade in cardiovascular disease: Updates. Biochem Biophys Res Commun. 2024;694:149406. [PMID: 38134479, https://doi.org/10.1016/j.bbrc.2023.149406].
23. Lara-Guzman OJ, Arango-Gonzalez AM, Alvarez-Quintero R, Escobar JS, Munoz-Durango K, Sierra JA. Circulating hs-CRP, IL-18, Chemerin, Leptin, and Adiponectin Levels Reflect Cardiometabolic Dysfunction in Adults with Excess Weight. Int J Mol Sci. 2025;26(3). [PMID: 39940942, PMCID: PMC11818792, https://doi.org/10.3390/ijms26031176].
24. Barnabe MA, Elliott J, Harris PA, Menzies-Gow NJ. Relationships between total adiponectin concentrations and obesity in native-breed ponies in England. Equine Vet J. 2024;56(2):264-72. [PMID: 37800870, https://doi.org/10.1111/evj.14013].
Data Availability Statement
The data supporting this study's findings are available upon reasonable request from the corresponding author.
License
Copyright (c) 2025 Hind F Jawad, Shatha H Ali, Mustafa S Jawad

This work is licensed under a Creative Commons Attribution 4.0 International License.
Copyright and Licensing
All articles published in ASIDE Internal Medicine are open access and freely available online immediately upon publication, without embargo.
This journal applies the terms of the Creative Commons Attribution 4.0 International License (CC BY 4.0). Under this license, anyone may copy, redistribute, remix, transform, and build upon the material for any purpose, even commercially, provided that proper credit is given to the original author(s), a link to the license is provided, and any changes made are indicated.
-
License link: https://creativecommons.org/licenses/by/4.0/
-
Machine-readable license metadata is embedded in each article and its DOI record.
Copyright Holder
Copyright in all articles remains with the author(s). ASIDE Internal Medicine is published and owned by the American Society for Inclusion, Diversity, and Equity in Healthcare (ASIDE). By submitting a manuscript, authors agree to grant the publisher a non-exclusive license to publish, distribute, and archive the work under the terms of the CC BY 4.0 license.
Third-party Material
Any material (e.g., images, figures, or tables) not covered by CC BY 4.0 will be clearly indicated in the article. Users must obtain permission directly from the copyright holder for reuse of such third-party material.
Author Rights and Self-Archiving
Authors are permitted to deposit all versions of their work (preprint, author’s accepted manuscript, and version of record) in institutional or subject repositories of their choice immediately upon publication, without embargo, provided that the DOI and license information are included.

Published
Issue
Section
Categories
How to Cite
Article history
- Received
- 15 Mar 2025
- Received in revised form
- 18 Mar 2025
- Accepted
- 18 Mar 2025
- Published
- 28 Mar 2025
