
Mycophenolate Mofetil for the Treatment of Resistant Inflammatory Bowel Disease: A Systematic Review and Meta-Analysis
DOI:
https://doi.org/10.71079/ASIDE.GI.03132515Abstract
Background: This systematic review evaluates the efficacy and safety of Mycophenolate Mofetil (MMF) for managing treatment‐resistant Inflammatory Bowel Disease (IBD), emphasizing remission rates and adverse effects.
Methods: Observational and controlled trials assessing MMF’s impact on IBD were included, excluding non-English and pediatric studies. Comprehensive searches were conducted in Embase, Medline/PubMed, Scopus, and Web of Science through October 2023. The risk of bias was evaluated using the NIH quality assessment tool, and results were synthesized using a random-effects meta-analysis model.
Results: Twelve studies comprising 446 participants (333 with Crohn’s disease and 113 with ulcerative colitis) were analyzed. The meta-analysis revealed remission rates of 62.2% at 8 weeks and 52.8% at 6 months. Adverse effects occurred in 26.1% of patients, with nausea and vomiting being the most common. Treatment discontinuation due to failure and intolerance was observed in 29.7% and 20% of cases, respectively.
Discussion: The findings suggest that MMF effectively induces remission in IBD patients unresponsive to conventional therapies, although a notable proportion experienced adverse events or treatment failure. Careful patient selection and monitoring are essential.
Conclusion: MMF presents a promising alternative for managing resistant IBD, but its adverse effect profile warrants cautious application. Further research is needed to optimize dosing strategies and assess long-term outcomes in this challenging patient population. These results underscore the potential of MMF as an effective therapeutic option while emphasizing the importance of individualized treatment plans and rigorous clinical monitoring. Future studies should focus on long-term safety and dosing. Additional robust research is required.
Keywords:
Mycoohenolate Mofetil, Inflammatory bowel disease , Crohn's disease, Ulcerative colitis, systematic review, Meta-analysisFull Text
Introduction
Inflammatory bowel disease (IBD) is categorized into two subtypes: Crohn’s disease (CD) and ulcerative colitis (UC). The causes of IBD are unknown; however, the mechanism involves hyperactive immune-mediated inflammation. Some studies have shown a genetic aspect associated with the genetic influence on the microbiome’s composition, as well as common susceptible gene loci found in IBD patients influencing its pathogenesis [1]. IBD is suspected through clinical symptoms and lab findings, however, the gold standard for the diagnosis is endoscopy/colonoscopy with a biopsy of the affected area showing specific histological features [2] In Crohn’s disease, the inflammation extends through all layers of the intestinal tissue and can affect any part of the intestinal tract, from mouth to anus. “Skipped lesions” are often seen, which is important when obtaining a tissue biopsy and determining the extent of the disease. In UC, inflammation is limited to the mucosal layer of the colon; commonly originating in the rectum and extending up to involve the entire colon continuously [3]. Complications unique to severe CD involve fistula formation, abscess formation, and strictures. A major complication unique to UC is toxic megacolon, which, if not treated immediately, can result in colon rupture and can lead to sepsis and death [4]. Inflammatory bowel disease (IBD) is widely accepted as one of the important risk factors leading to colorectal cancer (CRC). Patients with IBD are at a significantly increased risk of CRC, primarily due to the pro-neoplastic effects of chronic intestinal inflammation. The risk of CRC in IBD is influenced by factors such as disease duration, extent, and severity, the presence of inflammatory pseudopolyps, coexistent primary sclerosing cholangitis, and a family history of CRC [5].
Mycophenolate Mofetil (MMF) is a 2-morpholinoethyl ester, a prodrug that gets converted to mycophenolic acid (MPA). MPA is a non-competitive and reversible inhibitor of inosine monophosphate dehydrogenase, an enzyme involved in the purine biosynthesis pathway. Its effect on the de novo synthesis of purines allows it to play a role as an immunosuppressant [6]In earlier years, MMF was only FDA-approved for use in the prophylaxis of organ transplant rejection. Given its mechanism of action, MMF has since been used to treat a plethora of inflammatory/autoimmune conditions. Its first “off-label” use was for psoriasis. [7]. Many trials have then been done showing its efficacy and tolerability, and therefore it has become well-suited as a monotherapy or in combination with corticosteroids. MMF is also found to be effective in patients unresponsive or contraindicated to other immunomodulating agents, as well as in cases of steroid-sparing treatment. Overall, MMF is very well tolerated, with the most common side effects being gastrointestinal, diarrhea, nausea, and vomiting [8]. With the many variations in the presentation of Inflammatory bowel disease, as well as the variation in medication response and side effects, it’s important to consider all the possibilities to present to patients as a treatment plan. Mycophenolate mofetil is one immunomodulator that isn’t commonly used; however, given its mechanism of action, it may be a good option for certain individuals suffering from IBD. In this systematic review and meta-analysis, we aimed to study the efficacy and safety of MMF in managing resistant IBD, focusing on remission rates at eight weeks and six months, which is defined as the absence or significant reduction of symptoms associated with the disease.
Methods
This systematic review was conducted in accordance with the Preferred Reporting Items for Systematic Reviews and Meta-analysis (PRISMA) guidelines [9,10].
Search strategy
A broad search was done using the following databases: Embase, Medline/ PubMed, Scopus, and Web of Science. The search was conducted using Boolean search strategies and the following keywords from the MeSH database were used: (“Ulcerative colitis” OR “Crohn’s disease” OR “Crohn’s disease” OR “UC” OR “CD” OR “IBD” OR “Inflammatory bowel disease” OR “Colitis, Ulcerative” OR "Crohn Disease" OR "Inflammatory Bowel Diseases") AND (“Mycophenolate” OR “mycophenolate mofetil” OR “MMF” OR “Mycophenolic acid” OR “Sodium mycophenolate” OR “Cellcept” OR "Mycophenolic Acid"). A preliminary database search was done from inception till October 2023.
Two independent co-authors utilized the Covidence website to screen and remove duplicate studies, with a third reviewer resolving any disagreements.
Eligibility criteria
Articles included were prospective and retrospective observational case-control, cohort studies, as well as randomized controlled clinical trials. Articles excluded were narrative reviews, systematic reviews, case reports, abstracts, and case studies conducted on animals and pediatrics. Letters and articles in languages other than English, as well as studies that did not meet the required National Institute of Health (NIH) quality assessment score.
Data extraction:
Two co-authors extracted data into an Excel sheet and validated it with a third co-author.
Outcomes:
The outcomes of this study are defined as follows: First, remission rates at eight weeks and six months are assessed, where remission is identified as either the absence or a significant reduction of symptoms commonly associated with the disease. These symptoms include abdominal pain, diarrhea, rectal bleeding, fatigue, and weight loss. Secondly, steroid-free remission is measured, characterized by a marked clinical improvement—specifically, a reduction of three or more points on the Harvey-Bradshaw Index for Crohn’s disease and two or more points on the Mayo Partial Score for UC from baseline. This improvement must also coincide with a decrease in steroid dosage or a complete cessation. Finally, the study examines the overall incidence of adverse effects to evaluate the safety profile of the treatment and its potential as an alternative therapeutic option. These defined outcomes aim to comprehensively understand the treatment’s efficacy and safety.
Quality assessment:
Two co-authors performed quality appraisal using the NIH quality assessment tool, and articles scoring at least three points below the maximum score for the type of article were included in the final review.
Statistical analysis:
Pooled proportions of event rates and corresponding 95% confidence intervals (CIs) were calculated using a proportion meta-analysis with the random-effects model for remission rate (at eight weeks, six months, and steroid-free remission) and safety outcomes including discontinuation rate due to treatment failure or medication intolerance and overall adverse events (including nausea/vomiting, diarrhea, infections, and deranged liver function) for individuals subjected to MMF for IBD. A random effects model was applied to accommodate variations in study sizes. Heterogeneity was evaluated using I2 statistics, where values falling within <30%, 30% to 60%, 61% to 75%, and >75% were categorized as low, moderate, substantial, and considerable heterogeneity, respectively. Between-study sources of heterogeneity were examined through predefined subgroup analyses, and a P value for differences between subgroups of < .05 was considered statistically significant. Comprehensive Meta-Analysis software (version 2, Biostat, Englewood, NJ) was utilized for all analyses.
Results
Search results and patient characteristics
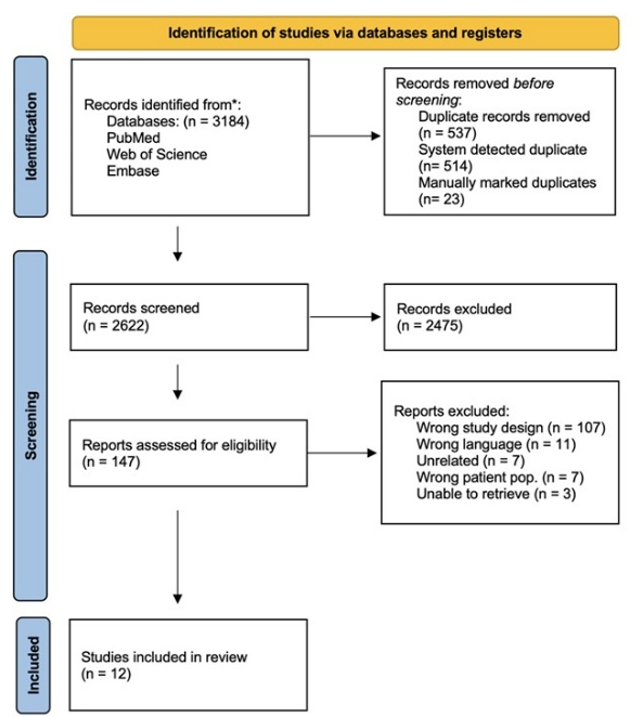
The initial search retrieved 3184 studies, 2622 of which underwent title and abstract screening, and 147 full texts were assessed for inclusion. A total of twelve studies were found to be eligible and have been pooled in this meta-analysis. The total number of IBD patients included in the study was 446 patients. 333 (74.6%) patients had CD, 107 (23.9%) patients had UC, 5 (1.1%) patients had UC/unspecified colitis, and 1 patient had unspecified colitis. The average age of participants was 38.4 years (range 25-42), and males made up 38.7% of the studied population. The mean duration of MMF therapy was 11.4 months. The rest of the baseline characteristics and summaries of the studies are demonstrated in Table 1.
Meta-analysis results
Remission at 8 weeks
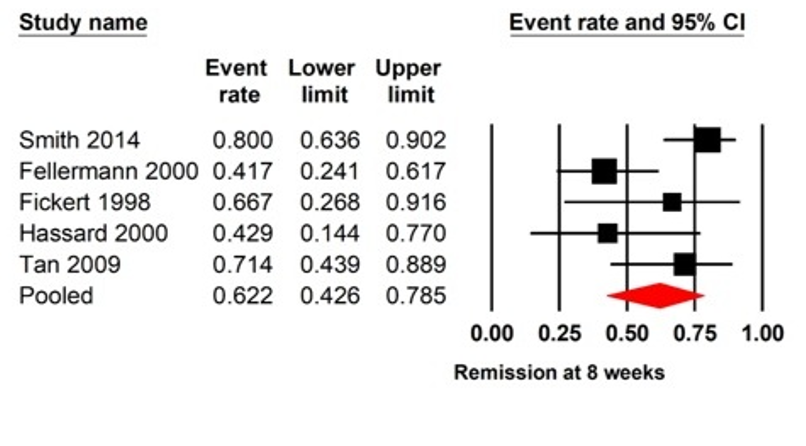
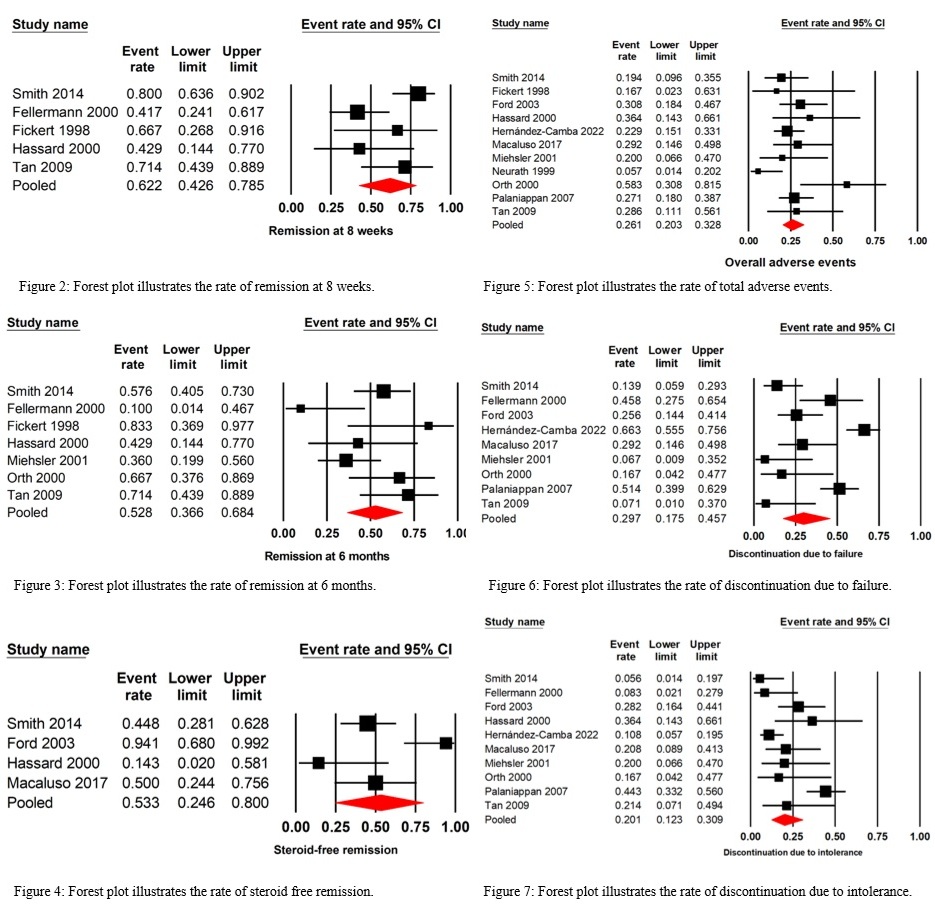
The forest plot illustrates remission rates at eight weeks and 95% CI. The area of the black square is proportional to the specific study weight of the overall meta‐analysis. The center of the red diamond displays the pool of the overall rate of remission at eight weeks, and its width shows the pooled 95% CI. Five studies were pooled with an overall rate of 62.2% with a 95% CI from 0.426 to 0.785 Figure 2.
Remission at 6 months
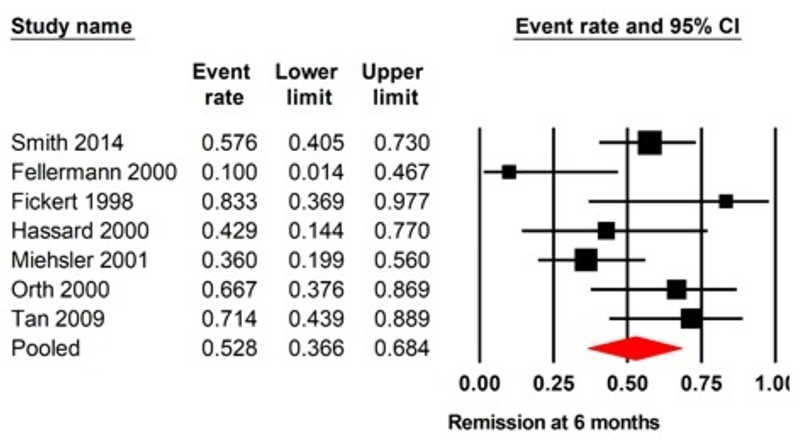
Regarding six-month remission rates, seven studies were pooled with an overall rate of 52.8% with a 95% CI from 0.366 to 0.684 Figure 3.
Steroid-free remissions
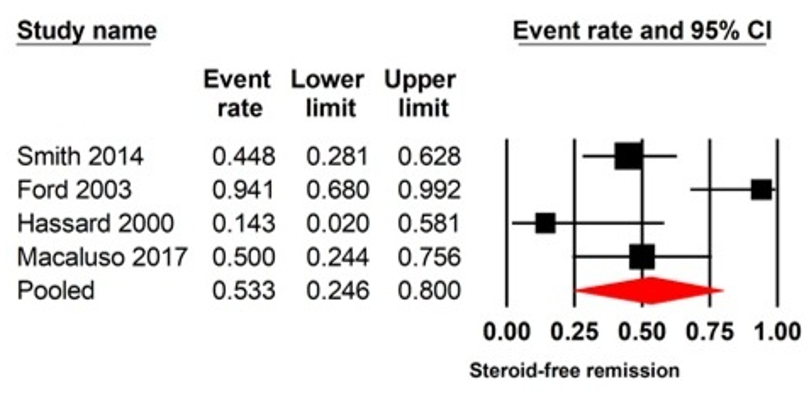
For steroid-free remission, 4 studies were pooled. The pooled steroid-free remission rate was 53.3% with a 95% CI from 0.246 to 0.80 Figure 4.
Overall Incidence of Adverse Effects
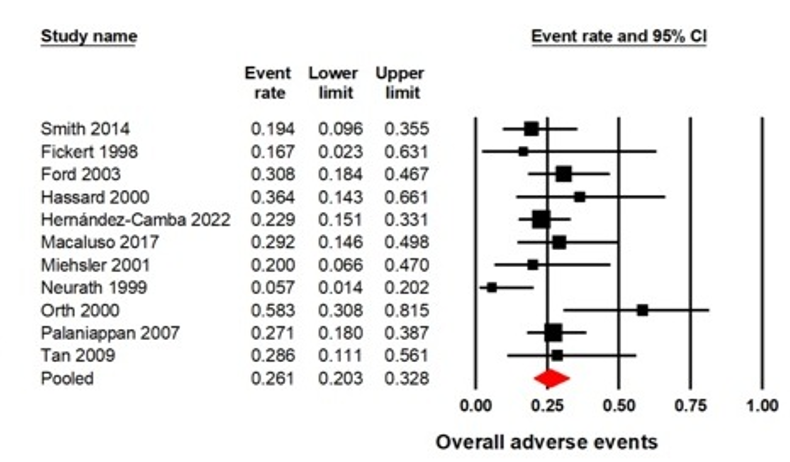
Twelve studies have been pooled in this analysis. The rate of total incidence of side effects pooled from this analysis is (26.1%) with a 95% CI from 0.203 to 0.328 Figure 5. Subgroup analysis reported different side effects: Nausea and Vomiting were the most frequently reported side effects where data from eight studies were pooled with an overall rate of 21.2% (8.5%-43.9%), 95% CI. The pooled rate of arthralgia incidence was 15.5% (7.9%-27.9%) with 95% CI. The pooled diarrhea incidence rate was 13.6% (7.6%-23%) with 95% CI. The pooled incidence of skin rash was 12.6% (5.2%-27.5%) with 95% CI. The pooled infection incidence rate was 12.6% (5%-28%) with 95% CI. The pooled incidence of deranged liver function was 7.5% (2.8%-18.7) with 95% CI. (Supplementary table).
Discontinuation rate due to failure
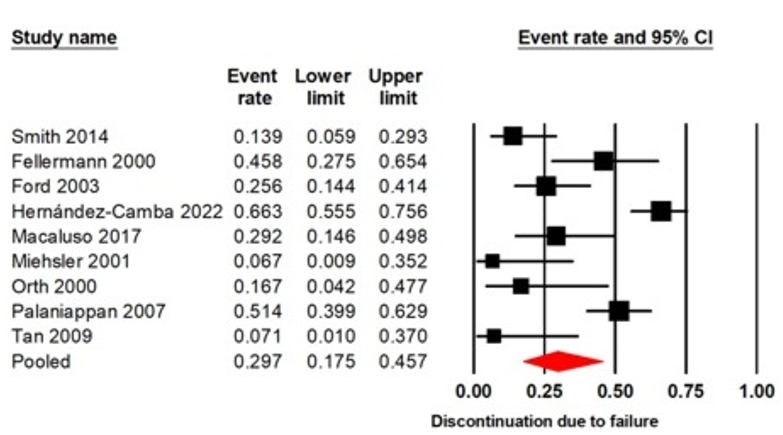
Failure to induce remission was the most common cause of drug discontinuation. The pooled rate was 29.7% with a 95% CI from 0.175 to 0.457 Figure 6.
Discontinuation due to intolerance
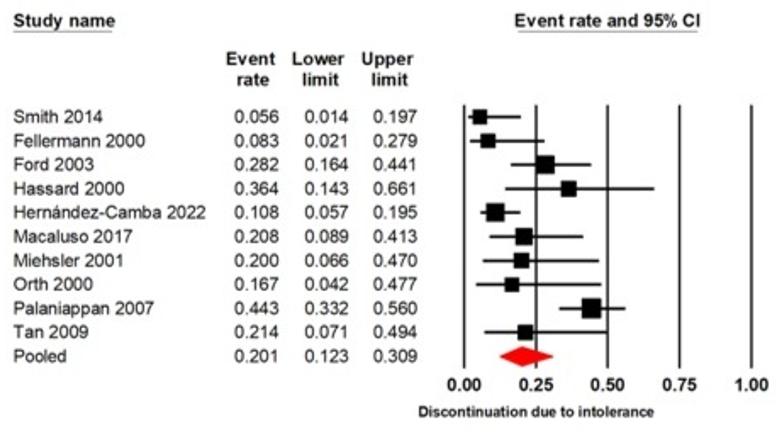
The pooled rate of drug discontinuation due to intolerance was 20% with a 95% CI from 0.123 to 0.309 Figure 7.
Discussion
Our study encompassed a systematic search that ultimately yielded twelve eligible studies involving 446 patients with IBD, predominantly with Crohn’s disease (74.6%) and ulcerative colitis (23.9%). Patient demographics revealed an average age of 38.4 years, with males comprising 38.7% of the cohort. The meta-analysis unveiled promising outcomes: remission rates at 8 weeks (62.2%), 6 months (52.8%), and steroid-free remission (53.3%). Additionally, the pooled incidence of side effects was 26.1%, with nausea/vomiting being the most prevalent (21.2%). Discontinuation rates due to failure (29.7%) and intolerance (20%) were notable, underscoring the importance of adverse event management and treatment efficacy in IBD therapy.
As we continue to learn the multifactorial risk factors contributing to IBD, we must also investigate the right medications to manage this disease. Since each patient presents with IBD in a unique way, their medication responsiveness is just as unique. To better explore and understand the effectiveness and indications of Mycophenolate Mofetil in the treatment of inflammatory bowel disease, we included 12 high-quality articles. In these articles, there appears to be an effective treatment therapy with the use of MFF for IBD.
Aminosalicylates (5-ASA), whether administered orally or topically, are efficacious in both initiating and sustaining remission in cases of moderate UC. These medications sometimes give rise to adverse symptoms such as nausea, fever, and rash. Glucocorticoids are the preferred first treatment for moderate to severe UC to induce remission. However, they are not recommended for long-term maintenance due to their major adverse effects on several organs, such as Cushing’s syndrome (e.g., insulin resistance, high blood pressure, cataracts, avascular necrosis). The process of gradually reducing their dosage should be implemented while simultaneously introducing maintenance treatment [11,12].
Immunomodulators, such as azathioprine (AZA) and its byproduct mercaptopurine, are glucocorticoid-sparing agents that may be introduced. The most common side effect is leukopenia and therefore all patients are required to have routine blood work. Biologics, including anti-TNF agents and monoclonal antibodies, have been proven to induce and maintain remission in moderate to severe UC. Risk factors of these agents include reactivation of latent infections such as TB and hepatitis B, and therefore, all patients must be worked up and treated for these infections before starting medication. Lastly, hospitalized patients can be started on cyclosporin, a calcineurin-inhibiting agent, when nonresponsive to IV glucocorticoids, with the most common side effects including hyperuricemia, hypertension, and gingival hyperplasia [13]. Treatment for CD varies from that of UC because of its intestinal tract involvement 5-ASA was only shown to be effective in mild CD with colon involvement. Glucocorticoids are effective in inducing remission in moderate to severe CD; however, just like in UC, they should not be used for maintenance therapy. Immunomodulators are also effective in CD as a glucocorticoid-sparing treatment; however, they have not been shown to induce remission. Methotrexate was found to be effective in maintaining.
remission and alleviating corticosteroid dependency; however, it puts patients at risk of interstitial pneumonitis and can cause hepatotoxicity. Biologics are recommended for moderate to severe CD, and are mostly effective as a combination therapy versus monotherapy [13].
Overall, our analysis studies have shown that MMF has been used particularly in patients who are steroid-dependent and are refractory or intolerant to more conventional therapies. A significant portion of patients are refractory to conventional therapies, making alternative management a hot topic. Studies were primarily conducted on IBD patients who were unresponsive, intolerant, or contraindicated for azathioprine. Patients often discontinue the drug due to unresponsiveness, resulting in disease relapse, or the event of undesired adverse effects such as pancreatitis, infections, and hepatitis. In a cross-sectional study by Lee et al., they discuss the intolerance of AZA as a predictor of a poor prognosis, indicating that patients with a more aggressive disease course [14]. Hassard et al. correlated resistance to AZA as a predictor of resistance to MMF, and resistance to AZA categorized patients as having severe IBD. Those unresponsive to AZA and MFF perhaps have an IBD that is resistant to the effects of purine synthesis inhibitors [15]Some studies have shown that patients have a deficiency in thiopurine methyltransferase (TPMT), the enzyme that metabolizes azathioprine. This reduction in the drugs’ metabolism increases the risk of bone marrow suppression, making AZA a poor option. [16].
| Author and Year | Study Type | Country | No. of Pt | UC | CD | Main Inclusion Criteria | Intervention | Previous TTT |
|---|---|---|---|---|---|---|---|---|
| Smith 2014 [17] | Retrospective | UK | 36 | 12 | 19 | All patients who had received MMF for IBD. | 500 mg–2 g/day (median 1 g), titrated to 2 g/day if tolerated. | 9 Corticosteroid, 33 AZA, 7 6-MP, 2 MTX, 3 infliximab |
| Neurath 1999 [18] | RCT | Germany | 70 | NA | 70 | Chronic active CD for 1 year with 3 acute flares in the past 3 years. | MMF 15 mg/kg + 50 mg vs AZA 2.5 mg/kg + 50 mg prednisolone. | NA |
| Hassard 2000 [15] | CT | USA | 11 | NA | 11 | CD patients needing IM therapy after failure/intolerance to AZA/6-MP/MTX. | 1–3 g/day in two divided doses. | 8 Corticosteroid, 11 AZA, 3 MTX, 3 Cyclosporin |
| Palaniappan 2007 [19] | Retrospective | UK | 70 | 19 | 51 | CD patients receiving MMF for IBD from 2000–2005. | 1.5 g/day (range 1–2 g/day). | 67 AZA, 7 MTX, 5 Cyclosporin, 4 Infliximab |
| Fellermann 2000 [20] | Prospective (Uncontrolled) | Germany | 24 | 13 | 11 | Active disease for past 2 months despite 10 mg prednisone. | Prednisone 60 mg + MMF 1 g/day; titrated to 2 g/day in 2 weeks; tapered prednisone. | NA |
| Ford 2003 [16] | Retrospective | UK | 39 | 7 | 32 | Patients receiving MMF for IBD treatment. | MMF 1.5 g/day (range 1–2 g/day). | 38 Corticosteroid, 37 AZA, 3 6-MP, 5 MTX, 3 Cyclosporin, 5 Infliximab |
| Fickert 1998 [21] | CT | Austria | 6 | NA | 6 | CD patients intolerant to AZA. | MMF 2 g/day. | 5 Corticosteroid, 3 AZA |
| Macaluso 2017 [22] | Prospective | Italy | 24 | 11 | 13 | Moderate-to-severe IBD with multiple failures or intolerance to IM/biologics. | 1000 mg/day for 15 days, titrated to 1500 mg/day (range 1000–2000 mg/day). | NA |
| Miehsler 2001 [23] | Retrospective | Austria | 45 | NA | 45 | Chronic active CD with MMF after AZA intolerance. | MMF 25–35 mg/kg. | 15 AZA, Corticosteroid |
| Hernández-Camba 2022 [24] | Retrospective | Spain | 83 | 17 | 66 | IBD patients 18 years who had received MMF. | MMF 1269.8 ± 741 mg/day. | NA |
| Orth 2000 [25] | RCT | Germany | 24 | 24 | NA | UC patients 18 years, active disease with 3 relapses since diagnosis. | MMF 20 mg/kg + prednisolone vs AZA 2 mg/kg + prednisolone. | NA |
| Tan 2009 [26] | CT | Australia | 14 | 5 | 9 | CD, UC, or IBD unclassified. | MMF 500–2000 mg twice daily. | 10 Corticosteroid, 13 AZA, 13 6-MP, 7 MTX, 8 Infliximab |
UC, Ulcerative Colitis; CD, Crohn’s Disease; MMF, Mycophenolate Mofetil; AZA, Azathioprine; 6-MP, 6-Mercaptopurine; MTX, Methotrexate; RCT, Randomized Controlled Trial; CT, Clinical Trial; TTT, treatment; NA, Not Available
The most undesirable reported adverse event with AZA is AZA-induced pancreatitis. In Fickert et al., 40% of the patients entered in the study after AZA-induced pancreatitis. Another patient was unable to start AZA because of prior mesalamine severe drug-induced pancreatitis, making AZA a poor option for them [21].
Miehsler et al compared two study groups and reported pancreatitis in 13% of patients, with another 10% showing elevated lipase in the group on AZA therapy. AZA-induced leukopenia occurred in 13% of the patients’ studies in Miehsler et al., whereas no patients on MMF were shown to have leukopenia. Additionally, Miehsler et al. reported the development of monoclonal gammopathy as a result of AZA. Not all side effects resolution was discussed; however, Fickert et al. report that all adverse reactions induced by AZA in the patient’s studies had disappeared after the discontinuation of the drug [21,23].
Our results, pooled from this meta-analysis, concluded that remission rates vary across periods. The overall remission rate was 62.2% at 8 weeks (95% CI: 42.6%-78.5%); it was marginally lower at 52.8% at 6 months (95% CI: 36.6%-68.4%). The pooled rate for steroid-free remission was 53.3% (95% CI: 24.6%-80%). The results of this study emphasize the significance of taking into account the duration and course of treatment when evaluating remission rates in individuals diagnosed with UC. Ford et al. report successful control of IBD with MMF in 41% of the studied patients with an average of 18 months of therapy. All of these patients were on steroids at the time of initiating MMF; however, they were no longer on steroids at the time of review. This allows us to consider MMF as a bridge therapy to remission in refractory patients. Miehsler et al. reported a significant reduction in the cumulative intake of prednisone within the first 6 months of MMF use, compared to no reduction in the prednisone intake in those on AZA. This alone can help guide treatment options, as chronic steroid use is associated with very severe long-term side effects. If tapering and cessation of steroids can be achieved quickly with MMF, it may be more favorable to avoid long-term risks associated with prolonged steroid use. This earlier onset of the therapeutic effect of MMF is also seen in transplant survival studies comparing MMF and AZA, and the reduction of rejection episodes [23].
In a study by Hernandez-Camba et al., clinical efficacy was seen in 71% of patients in whom MMF was added to their biologic regimen. This concomitant use of combined therapy can allow clinicians to consider adding MMF to a patient’s developing secondary non-response to anti-TNF alpha monotherapy. Furthermore, Fellermann et al. involved patients who were started on combined therapy of prednisone and MMF in the first block, followed by a decrease in prednisone and an increase in MMF in the second block. This helps us see the effects of dual therapy of prednisone for induction of remission, along with MMF as a bridge to monotherapy with just MMF. The study, however, reported decreased success as the steroids were tapered, indicating perhaps too early taper. Following this, those patients received a steroid pulse, and eventually, about 42% of patients reached remission and maintained remission after the steroid taper [20]. This may reflect the delayed onset of drug onset, leading us to consider the length of therapy required to reach drug efficacy.
When introducing a drug for medical management, it is important to understand the possibility and likelihood of adverse events. Our analysis of overall adverse effects in twelve pooled studies reveals an incidence rate of 26.1% (95% CI: 20.3%-32.8%). Subgroup analysis further delineates specific adverse events, with nausea and vomiting being the most frequently reported side effects, with an overall rate of 21.2% (95% CI: 8.5%-43.9%). Arthralgia follows, with a pooled rate of 15.5% (95% CI: 7.9%-27.9%), while diarrhea and skin rash show rates of 13.6% (95% CI: 7.6%-23%) and 12.6% (95% CI: 5.2%-27.5%), respectively. Additionally, the incidence of infection and deranged liver function were reported at 12.6% (95% CI: 5%-28%) and 7.5% (95% CI: 2.8%-18.7%), respectively. These findings underscore the need for careful monitoring and management of adverse effects in UC treatment to optimize patient care and outcomes. In addition to the specific adverse effects reported, the rate of medication discontinuation due to intolerance is a critical aspect of treatment evaluation. The pooled rate of drug discontinuation attributable to intolerance was found to be 20% (95% CI: 12.3%-30.9%) in the context of the aforementioned adverse events. This highlights the significant impact of side effects on treatment adherence and underscores the importance of balancing efficacy with tolerability in UC management strategies. Efforts to minimize adverse events and improve patient tolerability are essential to reduce the likelihood of treatment discontinuation and optimize long-term therapeutic outcomes.
In contrast, thiopurines are associated with specific risks, such as leukopenia, pancreatitis, and hepatotoxicity, while biologics carry risks of infections and immunogenicity leading to loss of response [27,28]. However, without direct comparative studies, it remains challenging to definitively evaluate MMF’s safety profile relative to these therapies.
Clinical implications: Based on the comprehensive analysis of various treatment options and their associated adverse effects, MMF emerges as a promising alternative for patients who cannot tolerate other conventional steroid-sparing agents, such as azathioprine, or other medications for IBD. The study findings demonstrate MMF’s efficacy in inducing and maintaining remission, particularly in patients who are steroid-dependent or refractory to other therapies. Notably, MMF shows a favorable adverse effect profile compared to azathioprine, with lower rates of adverse events such as leukopenia and pancreatitis, which are common concerns with azathioprine therapy. Additionally, MMF may offer quicker tapering of steroid use, reducing the risk of long-term steroid-related complications. Furthermore, MMF can be combined with biological agents for patients experiencing secondary non-response, potentially enhancing treatment outcomes. Although MMF is not without its side effects, careful monitoring and management can help mitigate adverse events and optimize therapeutic benefits. Therefore, MMF represents a valuable treatment option for patients with IBD who have failed or cannot tolerate other medications, offering a potential pathway to achieve and maintain remission while minimizing the risk of treatment-related complications.
Limitations: This is a single-arm analysis with a lack of a control group, which makes it challenging to establish a causal relationship between the intervention and outcomes. Without a comparator, it’s difficult to determine whether observed effects are solely attributable to the intervention or influenced by other factors. Another limitation of this study is its focus on patients with steroid dependence and refractoriness or intolerance to conventional therapies, primarily azathioprine, within the IBD population as those patients do not fully represent the broader spectrum of patients with IBD who may respond differently to treatments or have different underlying conditions.
Recommendation: Existing studies have focused on MMF in refractory or steroid-dependent IBD patients, leaving a gap in evidence for its use in early disease management. To date, randomized controlled trials (RCTs) specifically evaluating MMF as a first-line therapy in newly diagnosed IBD patients are lacking. This absence of robust data limits our understanding of MMF’s safety, efficacy, and positioning in the early treatment algorithm for IBD. Consequently, new RCTs testing the efficacy and safety of MMF in newly diagnosed IBP patients are warranted.
Conclusions
In conclusion, our study shed light on the potential of MMF as a treatment option for IBD. Despite limitations, including a lack of a control group, our findings suggest that MMF holds promise, particularly for individuals who are steroid-dependent or refractory to conventional steroid-sparing therapies. MMF demonstrates efficacy in inducing and maintaining remission, with a favorable adverse effect profile compared to some traditional treatments like azathioprine. However, further research, particularly prospective randomized controlled trials comparing MMF to standard treatments, is needed to better understand its role in IBD management.
Conflicts of Interest
None
Funding Source
None
Acknowledgments
None
Institutional Review Board (IRB)
None
Large Language Model
None
Authors Contribution
H.A., A.A., A.A., A.S., A.I., D.M., M.A., O.A., I.M., A.Y.A., M.N., and M.B. contributed equally to the conception, study design, data acquisition, statistical analysis, and interpretation of the findings in this research. All authors actively participated in drafting the manuscript and critically revising it for intellectual content. They have provided final approval for the version to be published and affirm their accountability for all aspects of the work, ensuring that any concerns regarding accuracy or integrity are thoroughly investigated and resolved.
Data Availability
All data generated or analyzed during this study are included in this published article. The data are publicly available and have been cited appropriately within the document’s text.
References
- Zhang Y. Z., Li Y. Y.. Inflammatory bowel disease: pathogenesis. World J Gastroenterol. 2014;20(1):91-9. doi:10.3748/wjg.v20.i1.91 PMID: 24415861 PMCID: PMC3886036
- Moazzami B., Moazzami K., Rezaei N.. Early onset inflammatory bowel disease: manifestations, genetics and diagnosis. Turk J Pediatr. 2019;61(5):637-647. doi:10.24953/turkjped.2019.05.001 PMID: 32104994
- Rodrigues B. L., Mazzaro M. C., Nagasako C. K., Ayrizono M. L. S., Fagundes J. J., Leal R. F.. Assessment of disease activity in inflammatory bowel diseases: Non-invasive biomarkers and endoscopic scores. World J Gastrointest Endosc. 2020;12(12):504-520. doi:10.4253/wjge.v12.i12.504 PMID: 33362904 PMCID: PMC7739141
- Rothfuss K. S., Stange E. F., Herrlinger K. R.. Extraintestinal manifestations and complications in inflammatory bowel diseases. World J Gastroenterol. 2006;12(30):4819-31. doi:10.3748/wjg.v12.i30.4819 PMID: 16937463 PMCID: PMC4087615
- Kim E. R., Chang D. K.. Colorectal cancer in inflammatory bowel disease: the risk, pathogenesis, prevention and diagnosis. World J Gastroenterol. 2014;20(29):9872-81. doi:10.3748/wjg.v20.i29.9872 PMID: 25110418 PMCID: PMC4123369
- Chakrabarti K., Frame D., Al Abbas M., McCune W. J.. The use of mycophenolate mofetil area under the curve. Curr Opin Rheumatol. 2021;33(3):221-232. doi:10.1097/BOR.0000000000000799 PMID: 33741807
- Orvis A. K., Wesson S. K., Breza T. S., Jr., Church A. A., Mitchell C. L., Watkins S. W.. Mycophenolate mofetil in dermatology. J Am Acad Dermatol. 2009;60(2):183-99; quiz 200-2. doi:10.1016/j.jaad.2008.08.049 PMID: 19150270
- Surjushe A., Saple D. G.. Mycophenolate mofetil. Indian J Dermatol Venereol Leprol. 2008;74(2):180-4. doi:10.4103/0378-6323.39725 PMID: 18388396
- Cumpston M., Li T., Page M. J., Chandler J., Welch V. A., Higgins J. P., Thomas J.. Updated guidance for trusted systematic reviews: a new edition of the Cochrane Handbook for Systematic Reviews of Interventions. Cochrane Database Syst Rev. 2019;10(10):ED000142. doi:10.1002/14651858.ED000142 PMID: 31643080 PMCID: PMC10284251
- Moher D., Liberati A., Tetzlaff J., Altman D. G., PRISMA Group. Preferred reporting items for systematic reviews and meta-analyses: the PRISMA statement. Int J Surg. 2010;8(5):336-41. doi:10.1016/j.ijsu.2010.02.007 PMID: 20171303
- Bruscoli S., Febo M., Riccardi C., Migliorati G.. Glucocorticoid Therapy in Inflammatory Bowel Disease: Mechanisms and Clinical Practice. Front Immunol. 2021;12:691480. doi:10.3389/fimmu.2021.691480 PMID: 34149734 PMCID: PMC8209469
- Murray A., Nguyen T. M., Parker C. E., Feagan B. G., MacDonald J. K.. Oral 5-aminosalicylic acid for induction of remission in ulcerative colitis. Cochrane Database Syst Rev. 2020;8(8):CD000543. doi:10.1002/14651858.CD000543.pub5 PMID: 32786164 PMCID: PMC8189994
- Jeong D. Y., Kim S., Son M. J., Son C. Y., Kim J. Y., Kronbichler A., Lee K. H., Shin J. I.. Induction and maintenance treatment of inflammatory bowel disease: A comprehensive review. Autoimmun Rev. 2019;18(5):439-454. doi:10.1016/j.autrev.2019.03.002 PMID: 30844556
- Lee L. Y. W., Gardezi A. S., Santharam V., Boyd J., Lanzon-Miller S.. Effect of azathioprine intolerance on outcomes of inflammatory bowel disease: a cross-sectional study. Frontline Gastroenterol. 2014;5(1):40-43. doi:10.1136/flgastro-2013-100348 PMID: 28839749 PMCID: PMC5369706
- Hassard P. V., Vasiliauskas E. A., Kam L. Y., Targan S. R., Abreu M. T.. Efficacy of mycophenolate mofetil in patients failing 6-mercaptopurine or azathioprine therapy for Crohn's disease. Inflamm Bowel Dis. 2000;6(1):16-20. doi:10.1097/00054725-200002000-00003 PMID: 10701145
- Ford A. C., Towler R. J., Moayyedi P., Chalmers D. M., Axon A. T.. Mycophenolate mofetil in refractory inflammatory bowel disease. Aliment Pharmacol Ther. 2003;17(11):1365-9. doi:10.1046/j.1365-2036.2003.01581.x PMID: 12786630
- Smith M. R., Cooper S. C.. Mycophenolate mofetil therapy in the management of inflammatory bowel disease--a retrospective case series and review. J Crohns Colitis. 2014;8(8):890-7. doi:10.1016/j.crohns.2014.01.014 PMID: 24507162
- Neurath M. F., Wanitschke R., Peters M., Krummenauer F., Meyer zum Buschenfelde K. H., Schlaak J. F.. Randomised trial of mycophenolate mofetil versus azathioprine for treatment of chronic active Crohn's disease. Gut. 1999;44(5):625-8. doi:10.1136/gut.44.5.625 PMID: 10205197 PMCID: PMC1727513
- Palaniappan S., Ford A. C., Greer D., Everett S. M., Chalmers D. M., Axon A. T., Hamlin P. J.. Mycophenolate mofetil therapy for refractory inflammatory bowel disease. Inflamm Bowel Dis. 2007;13(12):1488-92. doi:10.1002/ibd.20258 PMID: 17924566
- Fellermann K., Steffen M., Stein J., Raedler A., Hamling J., Ludwig D., Loeschke K., Stange E. F.. Mycophenolate mofetil: lack of efficacy in chronic active inflammatory bowel disease. Aliment Pharmacol Ther. 2000;14(2):171-6. doi:10.1046/j.1365-2036.2000.00695.x PMID: 10651657
- Fickert P., Hinterleitner T. A., Wenzl H. H., Aichbichler B. W., Petritsch W.. Mycophenolate mofetil in patients with Crohn's disease. Am J Gastroenterol. 1998;93(12):2529-32. doi:10.1111/j.1572-0241.1998.00606.x PMID: 9860419
- Macaluso F. S., Maida M., Renna S., Orlando E., Affronti M., Sapienza C., Dimarco M., Orlando R., Rizzuto G., Cottone M., Orlando A.. Mycophenolate mofetil is a valid option in patients with inflammatory bowel disease resistant to TNF-alpha inhibitors and conventional immunosuppressants. Dig Liver Dis. 2017;49(2):157-162. doi:10.1016/j.dld.2016.10.001 PMID: 27876682
- Miehsler W., Reinisch W., Moser G., Gangl A., Vogelsang H.. Is mycophenolate mofetil an effective alternative in azathioprine-intolerant patients with chronic active Crohn's disease?. Am J Gastroenterol. 2001;96(3):782-7. doi:10.1111/j.1572-0241.2001.03622.x PMID: 11280551
- Hernandez-Camba A., Arranz L., Vera I., Carpio D., Calafat M., Lucendo A. J., Taxonera C., Marin S., Garcia M. J., Marin G. S., Rodriguez E. S., Carbajo A. Y., De Castro M. L., Iborra M., Martin-Cardona A., Rodriguez-Lago I., Busquets D., Bertoletti F., Ausin M. S., Tardillo C., Malaves J. H., Bujanda L., Castano A., Domenech E., Ramos L., GETECCU group. Real-world use of mycophenolate mofetil in inflammatory bowel disease: Results from the ENEIDA registry. Dig Liver Dis. 2022;54(5):635-641. doi:10.1016/j.dld.2021.10.002 PMID: 34862115
- Orth T., Peters M., Schlaak J. F., Krummenauer F., Wanitschke R., Mayet W. J., Galle P. R., Neurath M. F.. Mycophenolate mofetil versus azathioprine in patients with chronic active ulcerative colitis: a 12-month pilot study. Am J Gastroenterol. 2000;95(5):1201-7. doi:10.1111/j.1572-0241.2000.02010.x PMID: 10811328
- Tan T., Lawrance I. C.. Use of mycophenolate mofetil in inflammatory bowel disease. World J Gastroenterol. 2009;15(13):1594-9. doi:10.3748/wjg.15.1594 PMID: 19340901 PMCID: PMC2669943
- Lim S. Z., Chua E. W.. Revisiting the Role of Thiopurines in Inflammatory Bowel Disease Through Pharmacogenomics and Use of Novel Methods for Therapeutic Drug Monitoring. Front Pharmacol. 2018;9:1107. doi:10.3389/fphar.2018.01107 PMID: 30349479 PMCID: PMC6186994
- Velikova T., Sekulovski M., Peshevska-Sekulovska M.. Immunogenicity and Loss of Effectiveness of Biologic Therapy for Inflammatory Bowel Disease Patients Due to Anti-Drug Antibody Development. Antibodies (Basel). 2024;13(1). doi:10.3390/antib13010016 PMID: 38534206 PMCID: PMC10967499
References
1. Zhang YZ, Li YY. Inflammatory bowel disease: pathogenesis. World J Gastroenterol. 2014;20(1):91-9. [PMID: 24415861, PMCID: PMC3886036, https://doi.org/10.3748/wjg.v20.i1.91].
2. Moazzami B, Moazzami K, Rezaei N. Early onset inflammatory bowel disease: manifestations, genetics and diagnosis. Turk J Pediatr. 2019;61(5):637-47. [PMID: 32104994, https://doi.org/10.24953/turkjped.2019.05.001].
3. Rodrigues BL, Mazzaro MC, Nagasako CK, Ayrizono MLS, Fagundes JJ, Leal RF. Assessment of disease activity in inflammatory bowel diseases: Non-invasive biomarkers and endoscopic scores. World J Gastrointest Endosc. 2020;12(12):504-20. [PMID: 33362904, PMCID: PMC7739141, https://doi.org/10.4253/wjge.v12.i12.504].
4. Rothfuss KS, Stange EF, Herrlinger KR. Extraintestinal manifestations and complications in inflammatory bowel diseases. World J Gastroenterol. 2006;12(30):4819-31. [PMID: 16937463, PMCID: PMC4087615, https://doi.org/10.3748/wjg.v12.i30.4819].
5. Kim ER, Chang DK. Colorectal cancer in inflammatory bowel disease: the risk, pathogenesis, prevention and diagnosis. World J Gastroenterol. 2014;20(29):9872-81. [PMID: 25110418, PMCID: PMC4123369, https://doi.org/10.3748/wjg.v20.i29.9872].
6. Chakrabarti K, Frame D, Al Abbas M, McCune WJ. The use of mycophenolate mofetil area under the curve. Curr Opin Rheumatol. 2021;33(3):221-32. [PMID: 33741807, https://doi.org/10.1097/BOR.0000000000000799].
7. Orvis AK, Wesson SK, Breza J T S, Church AA, Mitchell CL, Watkins SW. Mycophenolate mofetil in dermatology. J Am Acad Dermatol. 2009;60(2):183-99; quiz 200-2. [PMID: 19150270, https://doi.org/10.1016/j.jaad.2008.08.049].
8. Surjushe A, Saple DG. Mycophenolate mofetil. Indian J Dermatol Venereol Leprol. 2008;74(2):180-4. [PMID: 18388396, https://doi.org/10.4103/0378-6323.39725].
9. Cumpston M, Li T, Page MJ, Chandler J, Welch VA, Higgins JP, Thomas J. Updated guidance for trusted systematic reviews: a new edition of the Cochrane Handbook for Systematic Reviews of Interventions. Cochrane Database Syst Rev. 2019;10(10):ED000142. [PMID: 31643080, PMCID: PMC10284251, https://doi.org/10.1002/14651858.ED000142].
10. Moher D, Liberati A, Tetzlaff J, Altman DG, Group P. Preferred reporting items for systematic reviews and meta-analyses: the PRISMA statement. Int J Surg. 2010;8(5):336-41. [PMID: 20171303, https://doi.org/10.1016/j.ijsu.2010.02.007].
11. Bruscoli S, Febo M, Riccardi C, Migliorati G. Glucocorticoid Therapy in Inflammatory Bowel Disease: Mechanisms and Clinical Practice. Front Immunol. 2021;12:691480. [PMID: 34149734, PMCID: PMC8209469, https://doi.org/10.3389/fimmu.2021.691480].
12. Murray A, Nguyen TM, Parker CE, Feagan BG, MacDonald JK. Oral 5-aminosalicylic acid for induction of remission in ulcerative colitis. Cochrane Database Syst Rev. 2020;8(8):CD000543. [PMID: 32786164, PMCID: PMC8189994, https://doi.org/10.1002/14651858.CD000543.pub5].
13. Jeong DY, Kim S, Son MJ, Son CY, Kim JY, Kronbichler A, Lee KH, Shin JI. Induction and maintenance treatment of inflammatory bowel disease: A comprehensive review. Autoimmun Rev. 2019;18(5):439-54. [PMID: 30844556, https://doi.org/10.1016/j.autrev.2019.03.002].
14. Lee LYW, Gardezi AS, Santharam V, Boyd J, Lanzon-Miller S. Effect of azathioprine intolerance on outcomes of inflammatory bowel disease: a cross-sectional study. Frontline Gastroenterol. 2014;5(1):40-3. [PMID: 28839749, PMCID: PMC5369706, https://doi.org/10.1136/flgastro-2013-100348].
15. Hassard PV, Vasiliauskas EA, Kam LY, Targan SR, Abreu MT. Efficacy of mycophenolate mofetil in patients failing 6-mercaptopurine or azathioprine therapy for Crohn's disease. Inflamm Bowel Dis. 2000;6(1):16-20. [PMID: 10701145, https://doi.org/10.1097/00054725-200002000-00003].
16. Ford AC, Towler RJ, Moayyedi P, Chalmers DM, Axon AT. Mycophenolate mofetil in refractory inflammatory bowel disease. Aliment Pharmacol Ther. 2003;17(11):1365-9. [PMID: 12786630, https://doi.org/10.1046/j.1365-2036.2003.01581.x].
17. Smith MR, Cooper SC. Mycophenolate mofetil therapy in the management of inflammatory bowel disease–a retrospective case series and review. J Crohns Colitis. 2014;8(8):890-7. [PMID: 24507162, https://doi.org/10.1016/j.crohns.2014.01.014].
18. Neurath MF, Wanitschke R, Peters M, Krummenauer F, Meyer zum Buschenfelde KH, Schlaak JF. Randomised trial of mycophenolate mofetil versus azathioprine for treatment of chronic active Crohn's disease. Gut. 1999;44(5):625-8. [PMID: 10205197, PMCID: PMC1727513, https://doi.org/10.1136/gut.44.5.625].
19. Palaniappan S, Ford AC, Greer D, Everett SM, Chalmers DM, Axon AT, Hamlin PJ. Mycophenolate mofetil therapy for refractory inflammatory bowel disease. Inflamm Bowel Dis. 2007;13(12):1488-92. [PMID: 17924566, https://doi.org/10.1002/ibd.20258].
20. Fellermann K, Steffen M, Stein J, Raedler A, Hamling J, Ludwig D, Loeschke K, Stange EF. Mycophenolate mofetil: lack of efficacy in chronic active inflammatory bowel disease. Aliment Pharmacol Ther. 2000;14(2):171-6. [PMID: 10651657, https://doi.org/10.1046/j.1365-2036.2000.00695.x].
21. Fickert P, Hinterleitner TA, Wenzl HH, Aichbichler BW, Petritsch W. Mycophenolate mofetil in patients with Crohn's disease. Am J Gastroenterol. 1998;93(12):2529-32. [PMID: 9860419, https://doi.org/10.1111/j.1572-0241.1998.00606.x].
22. Macaluso FS, Maida M, Renna S, Orlando E, Affronti M, Sapienza C, Dimarco M, Orlando R, Rizzuto G, Cottone M, Orlando A. Mycophenolate mofetil is a valid option in patients with inflammatory bowel disease resistant to TNF-alpha inhibitors and conventional immunosuppressants. Dig Liver Dis. 2017;49(2):157-62. [PMID: 27876682, https://doi.org/10.1016/j.dld.2016.10.001].
23. Miehsler W, Reinisch W, Moser G, Gangl A, Vogelsang H. Is mycophenolate mofetil an effective alternative in azathioprine-intolerant patients with chronic active Crohn's disease? Am J Gastroenterol. 2001;96(3):782-7. [PMID: 11280551, https://doi.org/10.1111/j.1572-0241.2001.03622.x].
24. Hernandez-Camba A, Arranz L, Vera I, Carpio D, Calafat M, Lucendo AJ, Taxonera C, Marin S, Garcia MJ, Marin GS, Rodriguez ES, Carbajo AY, De Castro ML, Iborra M, Martin-Cardona A, Rodriguez-Lago I, Busquets D, Bertoletti F, Ausin MS, Tardillo C, Malaves JH, Bujanda L, Castano A, Domenech E, Ramos L, GETECCU group. Real-world use of mycophenolate mofetil in inflammatory bowel disease: Results from the ENEIDA registry. Dig Liver Dis. 2022;54(5):635-41. [PMID: 34862115, https://doi.org/10.1016/j.dld.2021.10.002].
25. Orth T, Peters M, Schlaak JF, Krummenauer F, Wanitschke R, Mayet WJ, Galle PR, Neurath MF. Mycophenolate mofetil versus azathioprine in patients with chronic active ulcerative colitis: a 12-month pilot study. Am J Gastroenterol. 2000;95(5):1201-7. [PMID: 10811328, https://doi.org/10.1111/j.1572-0241.2000.02010.x].
26. Tan T, Lawrance IC. Use of mycophenolate mofetil in inflammatory bowel disease. World J Gastroenterol. 2009;15(13):1594-9. [PMID: 19340901, PMCID: PMC2669943, https://doi.org/10.3748/wjg.15.1594].
27. Lim SZ, Chua EW. Revisiting the Role of Thiopurines in Inflammatory Bowel Disease Through Pharmacogenomics and Use of Novel Methods for Therapeutic Drug Monitoring. Front Pharmacol. 2018;9:1107. [PMID: 30349479, PMCID: PMC6186994, https://doi.org/10.3389/fphar.2018.01107].
28. Velikova T, Sekulovski M, Peshevska-Sekulovska M. Immunogenicity and Loss of Effectiveness of Biologic Therapy for Inflammatory Bowel Disease Patients Due to Anti-Drug Antibody Development. Antibodies (Basel). 2024;13(1). [PMID: 38534206, PMCID: PMC10967499, https://doi.org/10.3390/antib13010016].
Data Availability Statement
The data that support the findings of this study are derived from previously conducted studies and public databases. The datasets analyzed during the current study are available online.
License
Copyright (c) 2025 Natalie Balassiano, Jasmine Tidwell , Omar Abdelhalim, Mohammed Abusuliman, Mahmoud Nassar, Azizullah Beran, Ivan Cancarevic, Hazem Abosheaishaa

This work is licensed under a Creative Commons Attribution 4.0 International License.
Copyright and Licensing
All articles published in ASIDE Gastroenterology are open access and freely available online immediately upon publication, without embargo.
This journal applies the terms of the Creative Commons Attribution 4.0 International License (CC BY 4.0). Under this license, anyone may copy, redistribute, remix, transform, and build upon the material for any purpose, even commercially, provided that proper credit is given to the original author(s), a link to the license is provided, and any changes made are indicated.
-
License link: https://creativecommons.org/licenses/by/4.0/
-
Machine-readable license metadata is embedded in each article and its DOI record.
Copyright Holder
Copyright in all articles remains with the author(s). ASIDE Gastroenterology is published and owned by PubPorta Publishing LLC. By submitting a manuscript, authors agree to grant the publisher a non-exclusive license to publish, distribute, archive, and identify itself as the original publisher of the work under the terms of the CC BY 4.0 license.
Academic oversight and scholarly guidance are provided by the American Society for Inclusion, Diversity, and Equity in Healthcare (ASIDE). Copyright and licensing arrangements are administered by the publisher.
Third-party Material
Any material (e.g., images, figures, or tables) not covered by CC BY 4.0 will be clearly indicated in the article. Users must obtain permission directly from the copyright holder for reuse of such third-party material.
Author Rights and Self-Archiving
Authors are permitted to deposit all versions of their work (preprint, author’s accepted manuscript, and version of record) in institutional or subject repositories of their choice immediately upon publication, without embargo, provided that the DOI and license information are included.
Published
Issue
Section
How to Cite
Article history
- Received
- 19 Dec 2024
- Received in revised form
- 29 Dec 2024
- Accepted
- 22 Jan 2025
- Published
- 13 Mar 2025
