
Esophageal Stenting and Endoscopic Vacuum Therapy for Esophageal Defects: A Systematic Review and Meta-Analysis
DOI:
https://doi.org/10.71079/ASIDE.IM.07262576Abstract
Background: Spontaneous esophageal perforation, particularly Boerhaave syndrome, is a life-threatening condition associated with high morbidity and mortality. Traditional surgical management is increasingly being supplemented by minimally invasive approaches, including esophageal stenting and endoscopic vacuum therapy (EVT). However, the optimal treatment strategy remains debated due to variations in reported outcomes and the lack of randomized controlled trials. This systematic review and meta-analysis aim to evaluate the efficacy and safety of esophageal stenting and EVT in managing esophageal defects by specifically assessing sealing rates, failure rates, and mortality.
Methods: A comprehensive literature search was conducted in PubMed, Scopus, and the Cochrane Library up to March 24, 2025. Only observational studies and case series were included. The primary outcomes were the pooled sealing rate, failure rate, and mortality for esophageal stenting, and the closure rate for EVT. Data were analyzed using a random-effects model, and heterogeneity was assessed using the I² statistic.
Results: Fourteen studies on esophageal stenting demonstrated a pooled sealing rate of 86.1% (95% CI: 80.2–92.0%) with a failure rate of 14.9% (95% CI: 8.5–21.3%). Mortality associated with stenting was 7.4% (95% CI: 3.5–11.4%). EVT studies reported a closure rate ranging from 80% to 94%.
Conclusion: Both esophageal stenting and EVT show high efficacy in sealing esophageal defects. Although EVT exhibits promising closure rates, further comparative studies are needed to establish definitive treatment guidelines.
Keywords:
Esophageal Stenting, Endoscopic Vacuum Therapy, Esophageal Defects, Meta-analysis, Observational StudiesFull Text
Introduction
Spontaneous esophageal perforation—commonly known as Boerhaave syndrome or barogenic rupture—is an infrequent yet life-threatening condition. It arises from a sudden surge in pressure within the distal esophagus while the upper esophageal sphincter remains closed, a scenario frequently precipitated by forceful vomiting or esophageal spasms. Although Mackler’s triad of vomiting, chest pain, and subcutaneous emphysema is considered characteristic, nearly one-third of cases exhibit atypical clinical features that can delay diagnosis [1]. The rupture is most often localized to the left side of the lower intrathoracic esophagus [2]. And without prompt recognition and intervention, mortality rates can range from 15% to 42% [3]. Conventional treatment strategies involve emergency surgical procedures—such as primary repair, T-tube insertion, or esophageal resection and diversion—with early surgery correlating with improved outcomes [4,5,6,7].
Esophageal leaks, perforations, and Boerhaave syndrome continue to pose significant clinical challenges given their high morbidity and mortality. While invasive surgical methods have traditionally been the mainstay of treatment, there has been a notable shift over the past two decades towards minimally invasive techniques. Approaches such as esophageal stenting and endoscopic vacuum therapy (EVT) have emerged as promising alternatives, offering the benefits of re-establishing gastrointestinal continuity, facilitating the drainage of infected areas, and optimizing resuscitative efforts. These interventions may reduce the duration and invasiveness of traditional surgeries, thereby enhancing patient recovery. In fact, a comprehensive review that analyzed 66 studies on the use of esophageal stents for anastomotic leaks and benign perforations reported a technical success rate of 96% and a clinical success rate of 87% [8,6].
Esophageal stenting, in particular, provides a less invasive option with the potential for rapid defect closure and lower procedural morbidity, while EVT has attracted attention for its effectiveness in promoting tissue healing and controlling sepsis in complex esophageal defects [9,1]. Despite their increasing utilization, the optimal treatment strategy remains debatable due to the variability in reported outcomes and the current lack of randomized controlled trials (RCTs).
The existing evidence is primarily derived from observational studies and case series, which are subject to inherent biases and confounding factors. Although recent reviews have contributed valuable insights into endoscopic stenting, they have generally not included EVT in their analyses [6]. More recent pivotal studies by Wannhoff et al. [10] and Anundsen et al. [11] have begun to integrate EVT data, offering further perspective on managing Boerhaave syndrome. This structured review is designed to systematically evaluate and synthesize the current literature, addressing the variability in clinical outcomes and establishing a robust foundation for decision-making in this high-risk patient population.
While a recent meta-analysis by Vohra et al. (2025) [12] provided important insights into the efficacy of EVT in esophageal luminal defects, our review differs significantly in scope and focus. We expand upon this foundation by directly comparing EVT and esophageal stenting, integrating recent studies, and analyzing additional outcomes, including mortality and failure rates. This broader comparative approach aims to inform treatment selection in a wider range of clinical contexts, including Boerhaave syndrome.
The primary objective of this systematic review and meta-analysis is to assess the sealing efficacy, failure rates, and mortality associated with esophageal stenting and EVT in patients with esophageal leaks, perforations, and particularly Boerhaave syndrome. Specifically, we aim to: (1) quantify the pooled sealing rate, failure rate, and mortality rate associated with esophageal stenting from various observational studies; (2) evaluate the efficacy of EVT in achieving defect closure while exploring the sources of heterogeneity and potential publication bias in the existing literature; and (3) compare the clinical outcomes of esophageal stenting and EVT to inform clinical practice and pinpoint priorities for future research.
Methods
Study Design and Literature Search
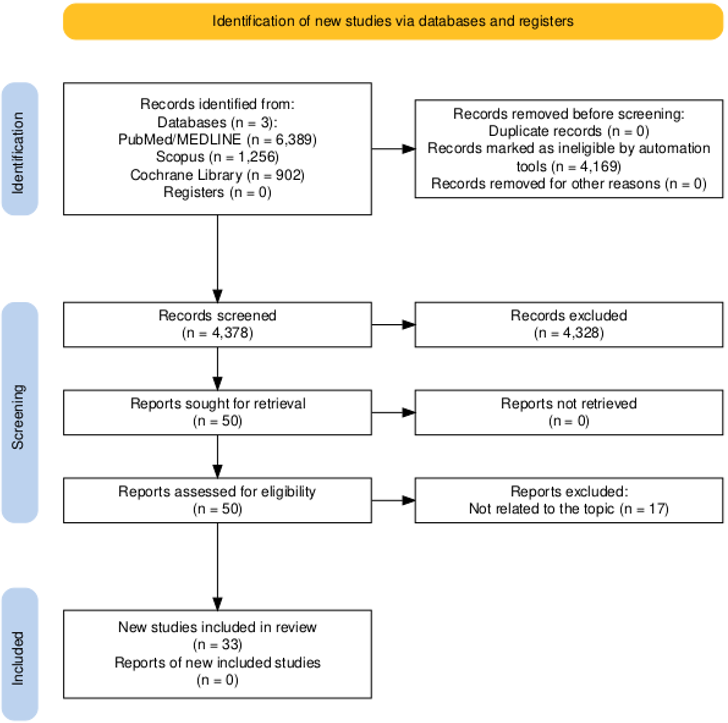
We performed a systematic review and meta-analysis to evaluate the efficacy and safety of esophageal stenting and EVT for various esophageal conditions, including anastomotic leaks, iatrogenic perforations, and Boerhaave syndrome. In light of the absence of randomized controlled trials (RCTs) in this field, our analysis was restricted to observational studies and case series. This review was conducted following the PRISMA 2020 guidelines (see flowchart in Figure 1), registered in PROSPERO, and the methodological quality was further ensured by adherence to the A Measurement Tool to Assess Systematic Reviews 2 (AMSTAR2) criteria [13]. A comprehensive literature search was carried out across PubMed/MEDLINE, Scopus, and the Cochrane Library from their inception until the 22nd of March 2025, using a combination of keywords and Medical Subject Headings (MeSH) including “esophageal stenting,” “endoscopic vacuum therapy,” “esophageal leak,” and “esophageal perforation.” No language restrictions were applied, and additional studies were identified through manual screening of reference lists. A detailed search strategy is available from Supplementary File S1. A PRISMA checklist is also added as a supplement. This systematic review was first registered with the International Prospective Register of Systematic Reviews (PROSPERO) on March 16, 2025, under the registration number CRD420251012734 (accessible at: https://www.crd.york.ac.uk/PROSPERO/view/CRD420251012734).
Eligibility Criteria and Study Selection
Studies were eligible for inclusion if they reported on the use of esophageal stents or EVT in patients with esophageal conditions. Although our inclusion criteria did not exclude randomized controlled trials (RCTs), our search identified no eligible RCTs that met the criteria for evaluating esophageal stenting or EVT in this context. As a result, the analysis was necessarily based on observational studies and case series. For stenting studies, outcomes of interest included sealing rates, failure rates, and mortality. EVT studies were required to report sealing success, treatment duration, and sponge change frequency. Two independent reviewers screened titles, abstracts, and full texts to determine eligibility, resolving any discrepancies through consensus. Study quality and risk of bias were assessed using the MINORS (Methodological Index for Non-Randomized Studies) scale [14] (available in Table 1 and Table 3). A separate table detailing the MINORS score for each study is available in Supplementary file S1.
Data Extraction and Outcome Measures
Data were independently extracted by two reviewers using a standardized extraction form. For esophageal stenting studies, the extracted variables included publication year, study design, MINORS score, stent types used, patient numbers, incidence of delayed presentation/treatment (>24 hours), sepsis incidence, and procedural details (e.g., concomitant drainage, additional drainage, endoscopic reinterventions, final sealing, failure, surgical conversion, and mortality). For EVT studies, we collected information on study design, country, conditions treated, MINORS score, number of patients, closure rate, mean treatment duration, and average sponge changes.
The primary outcomes for esophageal stenting included the sealing rate, defined as the proportion of patients achieving successful closure of the esophageal defect; the failure rate, defined as the proportion of cases in which stent therapy was unsuccessful and required surgical intervention; and the mortality rate, representing the proportion of patients who died in association with the esophageal condition or its treatment. For EVT, the primary outcome was the sealing rate, which indicated the successful closure of the esophageal defect following treatment.
Statistical Analysis
Meta-analyses were conducted using OpenMeta Analyst software [15] under a random-effects model to account for inter-study variability. Pooled proportions were calculated using the Freeman-Tukey double arcsine transformation to stabilize variance. Heterogeneity was assessed with the statistic, , and Cochran’s Q test. Publication bias was evaluated using the Eggers test, and sensitivity analyses were performed where significant bias was detected to test the robustness of our findings. A two-tailed p-value of less than 0.05 was considered statistically significant.
Results
Our systematic search did not identify any eligible RCTs evaluating esophageal stenting or endoscopic vacuum therapy EVT. Consequently, all included studies were either observational studies or case series. In our study, the summary of studies on esophageal stenting is tabulated in Table 1. Table 2 tabulates the procedural interventions and additional outcomes. Table 3 summarizes the studies on endoscopic vacuum therapy for esophageal conditions. A total of 15 studies, comprising 413 patients, were included in the analysis of EVT sealing outcomes.
| Author et al | Design | MINORS Score | Stent Types | Patients | Delayed Presentation/Treatment (>24h) | Sepsis Incidence |
|---|---|---|---|---|---|---|
| Wannhoff 2025 [10] | Retrospective | 10 | – | 57 | – | – |
| Anundsen 2024 [11] | Retrospective | 10 | WallFlex, EndoFlex, Hanaro | 17 | 6/17 (35%) | – |
| Chiu 2023 [16] | Retrospective | 10 | Wallflex | 5 | 5/5 (100%) | 3/5 (60%) |
| Hauge 2018 [17] | Retrospective | 8 | Ultraflex, Wallflex, SX-ELLA, Niti-S, Polyflex | 15 | 9/15 (60%) | – |
| Aloreidi 2018 [18] | Retrospective | 9 | Wallflex | 6 | 4/6 (67%) | 6/6 (100%) |
| Huh 2018 [19] | Retrospective | 10 | Hanarostent, Choo stent | 4 | – | – |
| Glatz 2016 [20] | Prospective | 11 | Ultraflex, Leufen | 16 | 4/16 (25%) | 6/16 (38%) |
| Wu 2016 [21] | Retrospective | 10 | Nanjing | 19 | 16/19 (84%) | 5/19 (26%) |
| Gubler 2014 [22] | Retrospective | 10 | Niti S, Rusch, Ultraflex, Hanarostent | 7 | – | – |
| Persson 2014 [23] | Retrospective | 10 | CSEMS | 23 | – | – |
| Schweigert 2013 [24] | Retrospective Comparative | 14 | Polyflex, Ultraflex | 13 | – | 9/13 (69%) |
| Darrien 2013 [25] | Retrospective | 10 | Ultraflex, Polyflex | 5 | 2/5 (40%) | 5/5 (100%) |
| Koivukangas 2012 [26] | Retrospective | 9 | Hanarostent, Nanjing | 14 | 7/14 (50%) | 7/14 (50%) |
| Freeman 2009 [27] | Prospective Observational | 12 | Polyflex | 19 | – | 3/19 (16%) |
| Salminen 2009 [28] | Retrospective | 8 | Hanarostent | 3 | 3/3 (100%) | – |
| Kim 2008 [29] | Retrospective | 9 | Montgomery Salivary Bypass Stent | 4 | 4/4 (100%) | 4/4 (100%) |
| Fischer 2006 [30] | Retrospective | 8 | Ultraflex | 5 | 1/5 (20%) | 4/5 (80%) |
| Prichard 2006 [31] | Retrospective | 7 | CSEMS | 5 | 5/5 (100%) | – |
| Siersema 2003 [32] | Retrospective | 10 | Flamingo, Ultraflex | 5 | 4/5 (80%) | – |
| Chung 2001 [33] | Retrospective | 8 | Song, Niti S | 3 | 3/3 (100%) | – |
| Year, Author et al. | Concomitant Drainage | Additional Drainage | Endoscopic Reinterventions | Final Sealing | Failure | Surgical Conversion | Mortality |
|---|---|---|---|---|---|---|---|
| Anundsen 2024 [11] | 15/17 (88%) | 14/17 (82%) | 8/17 (47%) | 16/17 (94%) | 1/17 (6%) | 0 (0) | 1/17 (6%) |
| Chiu 2023 [16] | 5/5 (100%) | 1/5 (20%) | 0 (0) | 5/5 (100%) | 0 (0) | 0 (0) | 0 (0) |
| Hauge 2018 [17] | 14/15 (93%) | 4/15 (27%) | 5/15 (33%) | 13/15 (87%) | 2/15 (13%) | 0 (0) | 2/15 (13%) |
| Aloreidi 2018 [18] | 6/6 (100%) | 0 (0) | 3/6 (50%) | – | 0 (0) | 0 (0) | 0 (0) |
| Huh 2018 [19] | – | – | – | 4/4 (100%) | – | – | – |
| Glatz 2016 [20] | 15/16 (94%) | 11/16 (69%) | 5/16 (31%) | 11/16 (69%) | 6/16 (38%) | 4/16 (25%) | 2/16 (13%) |
| Wu 2016 [21] | 19/19 (100%) | – | 0 (0) | 16/19 (84%) | 1/19 (5%) | 0 (0) | 1/19 (5%) |
| Gubler 2014 [22] | – | – | – | 5/7 (71%) | – | – | – |
| Persson 2014 [23] | – | – | – | – | 3/23 (13%) | – | – |
| Schweigert 2013 [24] | 13/13 (100%) | 11/13 (85%) | – | – | 2/13 (15%) | 0 (0) | 2/13 (15%) |
| Darrien 2013 [25] | 5/5 (100%) | 4/5 (80%) | 4/5 (80%) | 2/5 (40%) | 1/5 (20%) | 0 (0) | 1/5 (20%) |
| Author et al. | Study Type | Country | Conditions Assessed (n) | MINORS Score | Number of Patients | Closure Rate (%) | Mean Duration of EVT (days) | Average Sponge Changes |
|---|---|---|---|---|---|---|---|---|
| Wedemeyer 2008 [34] | Case series | Germany | AL (2) | 10 | 2 | 100.0 | 15.0 | 4.0 |
| Loske 2011 [35] | Case series | Germany | AL (8); IP (3); BS (1); O (1) | 10 | 14 | 92.9 | 12.0 | 4.0 |
| Brangewitz 2013 [36] | Retrospective | Germany | AL (32) | 8 | 32 | 84.4 | 23.0 | 7.0 |
| Schneiwind 2013 [37] | Retrospective | Germany | AL (17) | 10 | 17 | Not available | 57.0 | Not available |
| Bludau 2013 [38] | Retrospective | Germany | AL (8); IP (3); BS (2); O (1) | 9 | 14 | 86 | 12.1 | 3.9 |
| Kuehn 2016 [39] | Retrospective | Germany | AL (11); IP (8) | 10 | 21 | 90 | 15.0 | 5.0 |
| Laukoetter 2017 [40] | Prospective | Germany | AL (39); IP (9); BS (4) | 10 | 52 | 94 | 22.0 | 6.0 |
| Bludau 2018 [41] | Retrospective | Germany | BS (6); IP (12); AL (59) | 14 | 77 | 77 | 11.0 | 2.75 |
| Alakkari 2019 [42] | Case series | UK | AL (1); BS (1) | 10 | 2 | 100 | 6.0 | 8.5 |
| Mastoridis 2022 [43] | Prospective | UK | AL (3); BS (3) | 8 | 7 | 85 | 13.0 | 3.0 |
| Richter 2022 [44] | Observational | Germany | AL (69); IP (9); BS (7); O (17) | 9 | 102 | 91 | 27.5 | 7.55 |
| Luttikhold 2023 [45] | Retrospective | Sweden | IP (16); BS (9); TP (2) | 7 | 27 | 89 | 12.0 | 1.0 |
| Wannhoff 2024 [10] | Retrospective | Germany | BS | 10 | 57 | 80 | – | – |
AL – Anastomotic leak; IP – Iatrogenic perforation; BS – Boerhaave syndrome; O – Other; TP – Traumatic perforation; EVT – Endoscopic vacuum therapy.
Further analysis is presented below under the subheadings for each analysis.
Forest Plot for Sealing Rate with Esophageal Stent Therapy
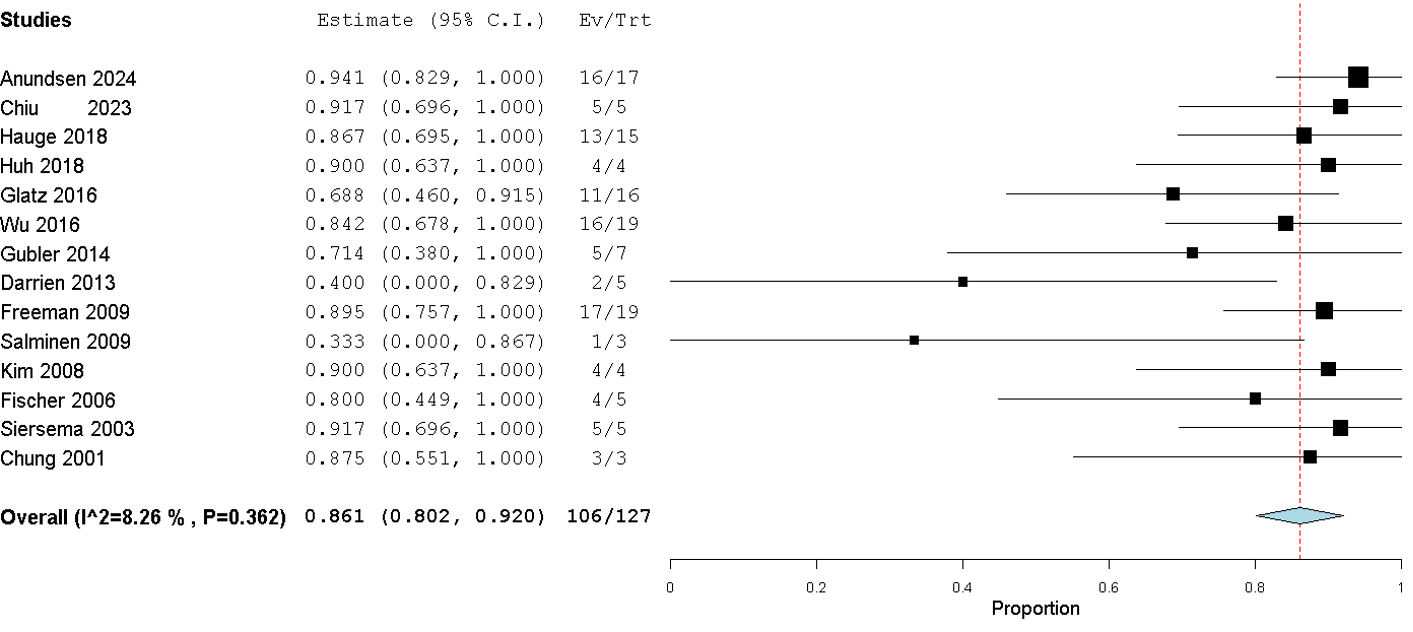
Fourteen studies[11,16,33,25,30,27,20,22,17,19,29,28,32,21] were pooled to assess the sealing success of esophageal stenting. In total, 106 successful sealing events were observed among 127 patients, yielding a pooled sealing rate of 86.1% (95% CI: 80.2%–92.0%) under a random-effects model. Heterogeneity was minimal (I² = 8.26%, p = 0.362). An Eggers test for publication bias produced a non-significant result (p = 0.42), suggesting no evidence of small-study effects as shown in Figure 2.
Forest plot failure of stent therapy
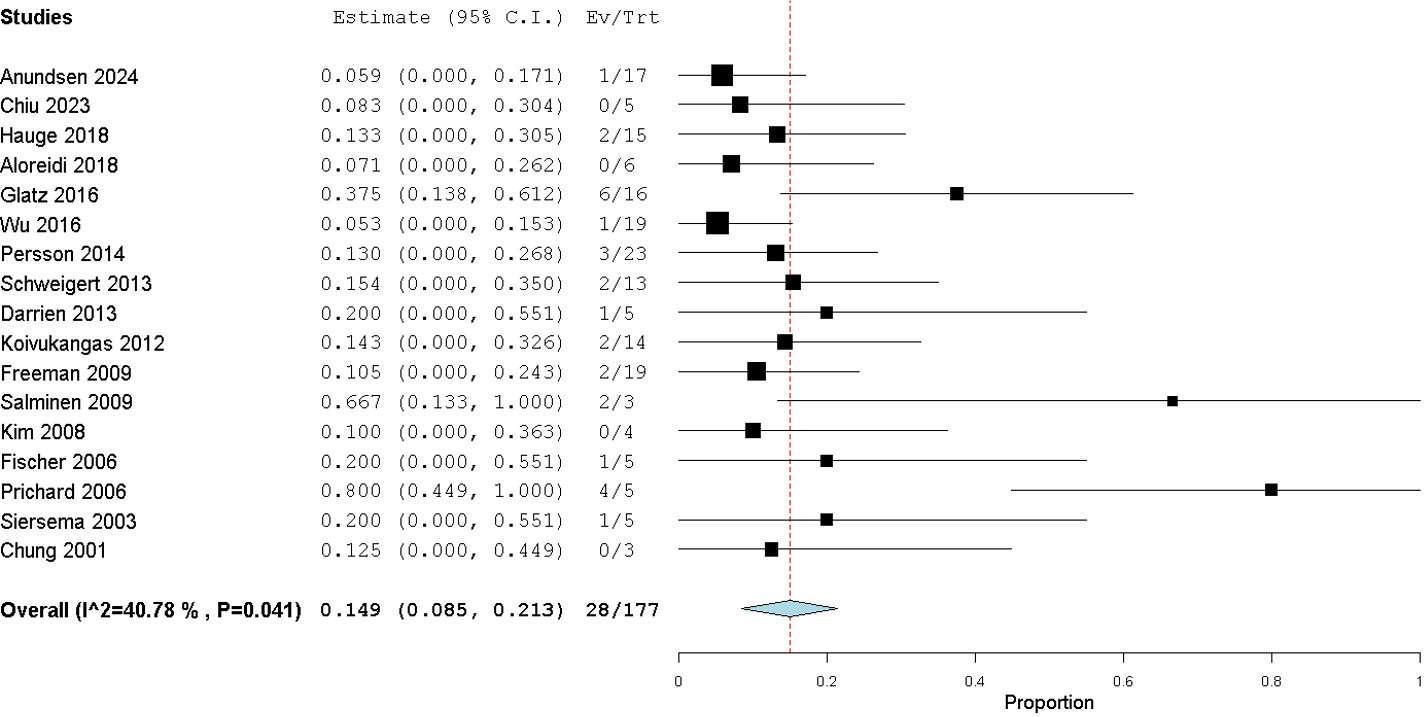
Seventeen studies[18,11,16,33,25,30,27,20,17,29,26,23,31,28,24,32,21] contributed data regarding stent therapy failure, with 28 failures recorded in 177 patients. The overall failure rate was 14.9% (95% CI: 8.5%–21.3%). Moderate heterogeneity was detected (I² = 40.78%, p = 0.041). The Eggers test did not indicate significant publication bias (p = 0.37) as shown in Figure 3.
Forest plot Mortality with esophageal stenting
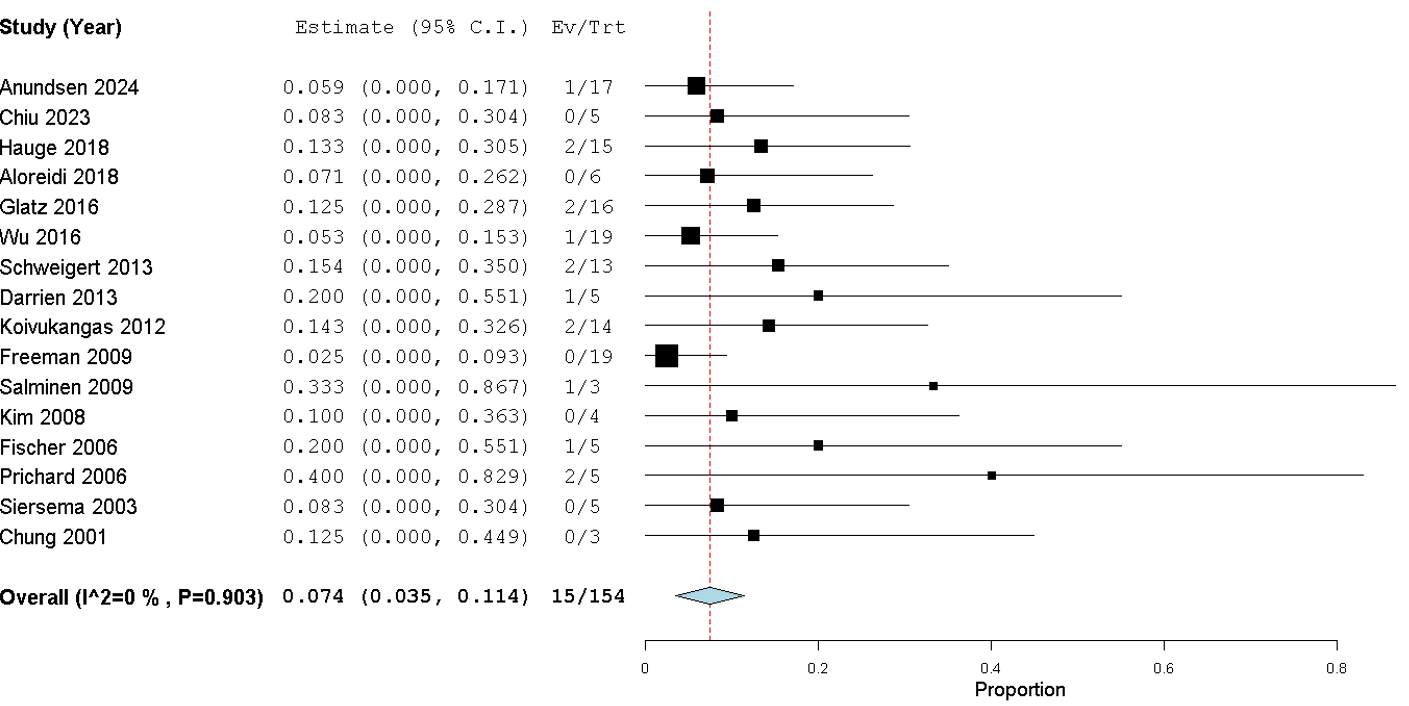
Data from the same set of studies [18,11,16,33,25,30,27,20,17,29,26,23,31,28,24,32,21] were used to evaluate mortality, with 15 deaths occurring among 154 patients. The pooled mortality rate was 7.4% (95% CI: 3.5%–11.4%), and no heterogeneity was observed (I² = 0%, p = 0.903). Egger’s test results (p = 0.56) further supported the absence of publication bias in this analysis, as shown in Figure 4.
Forest plot sealing rate with endoscopic vacuum therapy
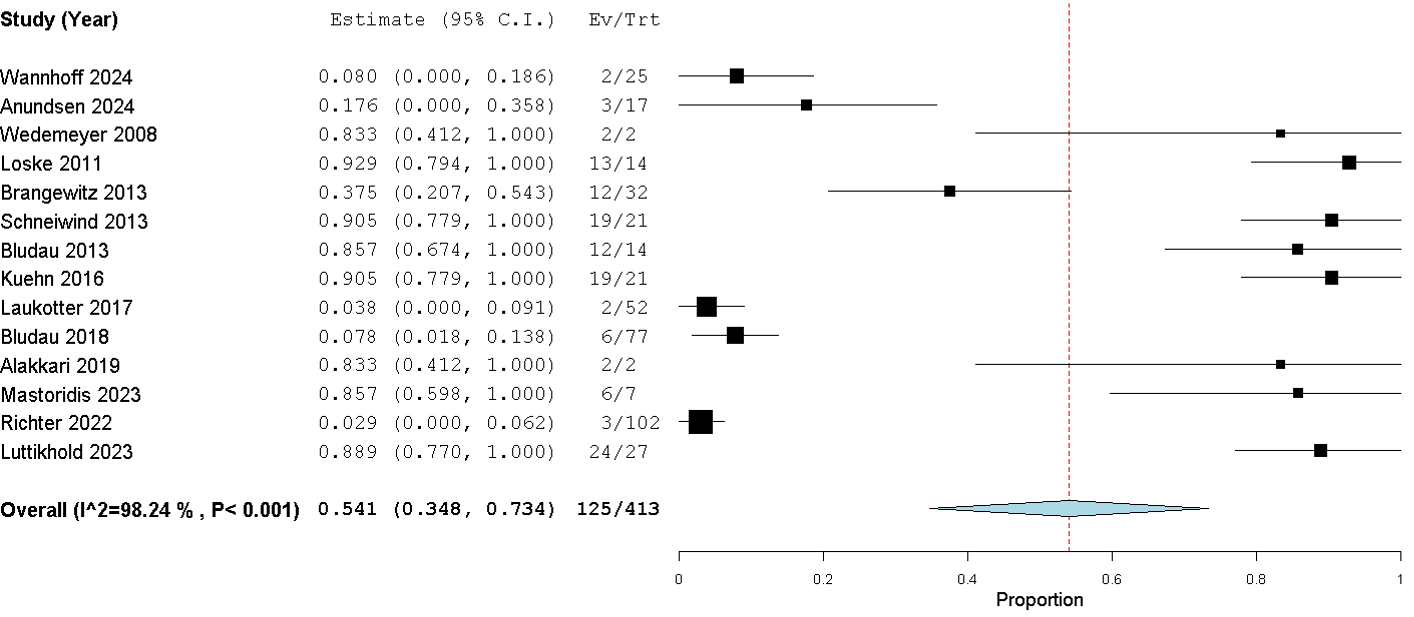
Fifteen studies [42,11,41,38,36,39,40,35,45,43,44,37,10,34] were analyzed for EVT sealing outcomes. Overall, 125 events were observed among 413 patients, resulting in a pooled sealing rate of 54.1% (95% CI: 34.8%–73.4%) using a binary random-effects model. Substantial heterogeneity was present (I² = 98.24%, p < 0.001). Moreover, the Eggers test for this analysis was significant (p = 0.01), indicating potential publication bias and small-study effects as shown in Figure 5.
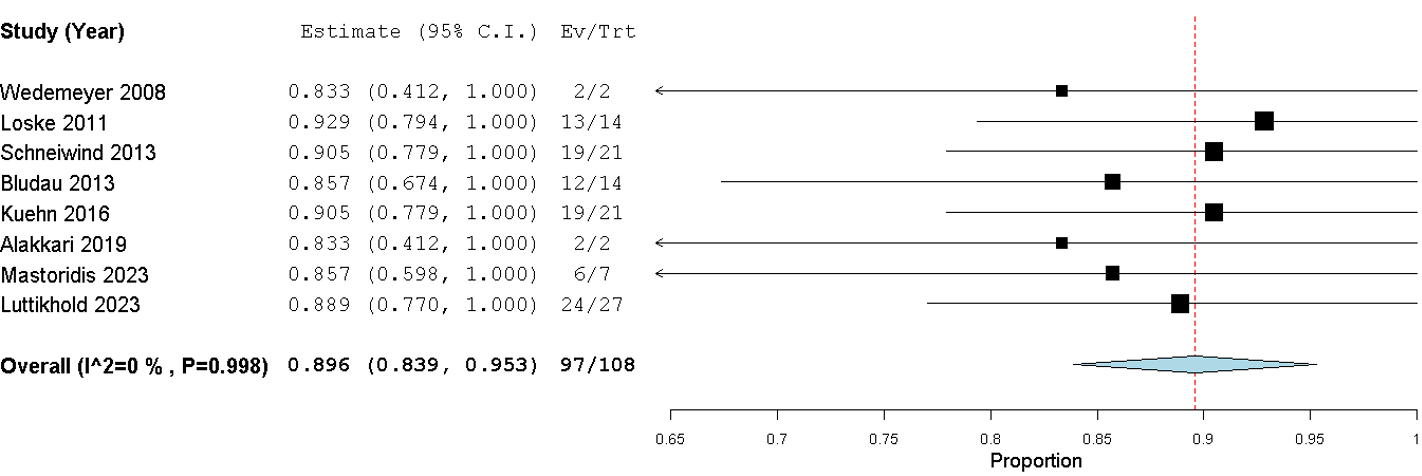
The sensitivity analysis shows a substantial change after removing some influential studies [11,41,36,40,44,10], the pooled sealing rate for EVT is now 89.6% (95% CI: 83.9–95.3%), with no heterogeneity (I² = 0%, p = 0.998). This suggests that those studies were major contributors to the significant publication bias and overall heterogeneity in the initial analysis, as shown in Figure 6. The large variability in reported outcomes likely reflects differences in patient selection, EVT protocols, and the quality of study design.
Discussion
Our study sought to deepen our understanding of the role of minimally invasive therapies, specifically esophageal stenting and EVT, in the treatment of complex esophageal defects. When we pooled data from 14 observational studies, esophageal stenting emerged with a notably high sealing success rate of 86.1% (95% CI: 80.2%–92.0%), a failure rate of 14.9% (95% CI: 8.5%–21.3%), and a mortality rate of 7.4% (95% CI: 3.5%–11.4%). These results are in strong agreement with earlier reports by Margaris et al. [6], who demonstrated that stents function as an effective bridge, maintaining continuity in the esophagus while allowing the defect to heal and preventing further contamination of the mediastinum and pleural space. This temporary “bridging” is especially important in the context of Boerhaave syndrome and other perforations, where the risk of sepsis is high. By avoiding the need for major surgical intervention—which is both physiologically taxing and carries inherent risks—stenting offers an appealing option for patients with multiple comorbidities or those deemed poor surgical candidates[5,6,46]. Equally significant is the role of concomitant drainage procedures; our review and other studies [5,6,46] highlight that proper drainage, when combined with stenting, is critical to controlling infection and facilitating recovery.
Our findings build upon those of Vohra et al. [12], whose work focused exclusively on EVT outcomes. While they reported pooled closure rates across various studies, our study additionally includes mortality, failure, and procedural outcomes and compares EVT with esophageal stenting across similar patient populations to provide a more comprehensive clinical perspective.
In contrast, our initial evaluation of EVT outcomes was far more variable. Across 15 studies, the pooled sealing rate for EVT was only 54.1% (95% CI: 34.8%–73.4%), accompanied by substantial heterogeneity (I² = 98.24%, p < 0.001) and indications of publication bias (Eggers test, p = 0.01). This inconsistency likely reflects the diverse patient populations, differing defect characteristics, and the lack of standardized treatment protocols that currently characterize EVT use. The dramatic improvement in EVT sealing rates from 54.1% to 89.6% in the sensitivity analysis highlights the influence of outlier studies and inconsistent reporting. Studies, such as those by Wannhoff et al. [10] and Bludau et al. [41], while important, may have introduced heterogeneity due to their unique patient populations, the inclusion of more complex defects, or variations in treatment protocols. Once these outliers were removed, the more consistent data revealed that EVT can achieve sealing rates comparable to those of stenting when applied under standardized, well-controlled conditions. This underscores the importance of protocol harmonization and careful patient selection when evaluating EVT outcomes. Early experiences—such as those described by Wedemeyer et al. [34]and further documented by Alakkari et al. [42]—demonstrated that EVT could serve as a vital rescue treatment after conventional surgery and stenting had failed. These pioneering reports provided the initial evidence that EVT not only promotes rapid wound closure but also minimizes the duration of hospital stays by facilitating continuous drainage of contaminated collections.
What is particularly intriguing is how subsequent studies have refined our understanding of EVT. For instance, Brangewitz et al. [36] and Schneiwind et al. [37] provided evidence that EVT could achieve higher closure rates and reduce mortality compared to stenting, especially in patients with severe systemic inflammation. Laukoetter et al. [40] reported healing in over 94% of patients treated solely with EVT—a result that initially seemed at odds with the pooled average in our analysis. Recognizing the heterogeneity in EVT outcomes, we performed a sensitivity analysis that excluded several influential outlier studies. This analysis dramatically improved the pooled sealing rate to 89.6% (95% CI: 83.9%–95.3%) and completely eliminated statistical heterogeneity (I² = 0%, p = 0.998). This finding strongly suggests that when EVT is applied in a more uniform manner—perhaps through standardized protocols and careful patient selection —its efficacy may well be comparable to, if not exceed, that of stenting. For instance, Schneiwind et al. [37] reported that in systemically ill patients with similar APACHE II scores, those treated with EVT experienced markedly improved results, with a mortality rate of only 12%, as opposed to 50% for surgery and 83% for stenting (p = 0.01 and p = 0.0014, respectively). In a separate study, Laukoetter et al. [40] demonstrated that EVT alone was sufficient to heal 94.2% of 52 patients, eliminating the necessity for any further interventions.
This observed heterogeneity highlights the need to tailor EVT use based on specific clinical scenarios. For instance, EVT appears especially beneficial in patients with large, complex leaks or significant mediastinal contamination—cases where continuous drainage and active defect healing are critical. Patients with systemic sepsis or those who have failed prior stent therapy may also derive greater benefit from EVT. Conversely, individuals with small, contained perforations or limited access to experienced endoscopy teams may be better served by stenting or conservative management. Moreover, because EVT requires multiple endoscopic interventions, it may not be ideal for critically ill patients who cannot tolerate repeated procedures or for centers lacking the infrastructure for close monitoring and frequent sponge changes. These considerations underscore the importance of individualized patient selection when applying EVT in clinical practice.
Yet, no therapy is without its drawbacks. EVT, while promising, presents practical challenges: it necessitates frequent endoscopic reassessments and sponge exchanges, which can prolong hospital stays and increase costs. There are also complications to consider, such as sponge dislocation, bleeding during the exchange, and the development of strictures. Some authors have debated whether the strictures observed are a direct consequence of EVT or are related to the complex nature of the esophageal pathology itself [41,38,36,40,6]. In our view, these issues underscore the importance of further refining EVT protocols and implementing rigorous training and standardization across centers.
It is also essential to acknowledge the limitations inherent in our analysis. All the data we synthesized come from observational studies and case series, with modest methodological quality as indicated by average MINORS scores in the range of 9–10. Such study designs are susceptible to biases—selection bias, lack of blinding, and uncontrolled confounding—which means that our findings, though informative, should be interpreted with cautious optimism. The absence of randomized controlled trials in this field is a significant gap, one that future prospective studies or multicenter registries must address to provide clearer guidance for clinical practice. Additionally, it is noteworthy that a substantial proportion of EVT studies included in this analysis originate from Germany. This geographic concentration may reflect regional differences in clinical expertise, institutional familiarity with EVT, and earlier adoption of the technique. Such concentration introduces a limitation in terms of generalizability, as the outcomes and protocols observed in German centers may not fully represent practices in other countries with different healthcare infrastructures, reimbursement systems, or procedural training. As EVT continues to gain global interest, future multicenter studies involving more diverse geographic regions will be essential to validate these findings and optimize external applicability.
In practical terms, our findings support a personalized approach to managing esophageal defects. For patients with high surgical risk or extensive comorbidities, esophageal stenting appears to offer a reliable, less invasive solution with a high success rate. Meanwhile, EVT holds considerable promise as an alternative or adjunct treatment, especially in settings where stenting has failed or is contraindicated. The evolution of EVT, as illustrated by improved outcomes in sensitivity analyses, suggests that uniform protocols and better patient selection can substantially enhance its effectiveness. Ultimately, both therapies are important tools in the endoscopist’s arsenal, and the choice between them should be guided by individual patient factors, available expertise, and institutional resources.
Several limitations must be acknowledged in interpreting the results of this meta-analysis. First, the absence of RCTs significantly limits the strength of the evidence. All included studies were observational in nature, either retrospective cohorts or case series, which are inherently prone to selection bias, unmeasured confounding, and lack of standardized outcome definitions. Second, substantial heterogeneity was observed in the analysis of EVT, which reflects variability in patient selection, treatment protocols, and institutional expertise. Although sensitivity analysis helped mitigate this issue, the initial inconsistency underscores the need for standardization across centers. Third, most EVT studies originated from Germany, potentially limiting the generalizability of findings to other regions where practice patterns, resources, and clinical thresholds may differ. Additionally, the relatively small sample sizes in many included studies, as well as the lack of uniform reporting on adverse events and long-term follow-up, further constrain our ability to draw definitive conclusions about comparative efficacy and safety. Finally, despite comprehensive database searches, the possibility of publication bias cannot be fully excluded.
In conclusion, our meta-analysis reinforces the notion that both esophageal stenting and EVT are viable, minimally invasive options for treating esophageal leaks and perforations. While stenting shows consistently high sealing rates and low mortality, EVT demonstrates significant potential when applied under standardized conditions. Future research should focus on conducting high-quality prospective studies and cost-effectiveness analyses to refine treatment protocols and establish clearer criteria for patient selection, thereby improving outcomes for this challenging and high-risk patient population.
Conclusion
Both esophageal stenting and EVT are effective, minimally invasive strategies for managing esophageal defects, with stenting showing consistently high sealing rates and low mortality, while EVT exhibits promising efficacy, especially when standardized protocols are applied. Despite the inherent limitations of observational data, these findings underscore the importance of individualized treatment approaches that incorporate adjunctive drainage and supportive care to optimize outcomes.
Key finding
Both esophageal stenting and EVT show high efficacy in sealing esophageal defects. Although EVT exhibits promising closure rates, further comparative studies are needed to establish definitive treatment guidelines.
From the authors' abstract.
中文摘要
食管支架置入与内镜负压治疗在食管缺损中的应用:系统综述与荟萃分析
背景:自发性食管穿孔,尤其是布尔哈夫综合征,是一种危及生命的疾病,伴随高发病率和死亡率。传统外科治疗正逐步被微创方法补充,包括食管支架置入和内镜负压治疗(EVT)。然而,由于报告结果的差异以及缺乏随机对照试验,最佳治疗策略仍存在争议。本系统综述与荟萃分析旨在评估食管支架置入和EVT在管理食管缺损中的疗效与安全性,特别关注密封率、失败率和死亡率。
方法:对 PubMed、Scopus 和 Cochrane Library 进行全面文献检索,截止至 2025 年 3 月 24 日。仅纳入观察性研究和病例系列。主要结局为食管支架置入的合并密封率、失败率和死亡率,以及EVT 的闭合率。采用随机效应模型进行数据分析,并使用 I² 统计量评估异质性。
结果:十四项食管支架置入研究显示,合并密封率为 86.1%(95% CI: 80.2–92.0%),失败率为 14.9%(95% CI: 8.5–21.3%)。与支架置入相关的死亡率为 7.4%(95% CI: 3.5–11.4%)。EVT 研究的闭合率范围为 80% 至 94%。
结论:食管支架置入和EVT均显示出高效的食管缺损密封效果。尽管EVT 的闭合率令人鼓舞,但仍需进一步的比较研究以确立明确的治疗指南。
本中文摘要为机器辅助翻译,仅供参考;以英文摘要为准。 Machine-assisted Chinese translation of the English abstract; the English abstract is the version of record.
References
1. Han D, Huang Z, Xiang J, Li H, Hang J. The Role of Operation in the Treatment of Boerhaave's Syndrome. BioMed research international. 2018: 8483401 [PMID: 30050944, https://doi.org/10.1155/2018/8483401]
2. Mackler SA. Spontaneous rupture of the esophagus; an experimental and clinical study. Surgery, gynecology & obstetrics. 1952: 345 [PMID: 14950670,
3. Biancari F, Tauriainen T, Ylikotila T, Kokkonen M, Rintala J, Makarainen-Uhlback E, Koivukangas V, Saarnio J. Outcome of stent grafting for esophageal perforations: single-center experience. Surgical endoscopy. 2017: 3696 [PMID: 28078464, https://doi.org/10.1007/s00464-016-5408-6]
4. Allaway MGR, Morris PD, JL BS, Richardson AJ, Johnston ES, Hollands MJ. Management of Boerhaave syndrome in Australasia: a retrospective case series and systematic review of the Australasian literature. ANZ journal of surgery. 2021: 1376 [PMID: 33319446, https://doi.org/10.1111/ans.16501]
5. Axtell AL, Gaissert HA, Morse CR, Premkumar A, Schumacher L, Muniappan A, Ott H, Allan JS, Lanuti M, Mathisen DJ, Wright CD. Management and outcomes of esophageal perforation. Diseases of the esophagus : official journal of the International Society for Diseases of the Esophagus. 2022: [PMID: 34212186, https://doi.org/10.1093/dote/doab039]
6. Margaris I, Triantafyllou T, Sidiropoulos TA, Sideris G, Theodorou D, Arkadopoulos N, Michalopoulos NV. Efficacy of esophageal stents as a primary therapeutic option in spontaneous esophageal perforations: a systematic review and meta-analysis of observational studies. Annals of gastroenterology. 2024: 156 [PMID: 38481783, https://doi.org/10.20524/aog.2024.0857]
7. Zimmermann M, Hoffmann M, Jungbluth T, Bruch HP, Keck T, Schloericke E. Predictors of Morbidity and Mortality in Esophageal Perforation: Retrospective Study of 80 Patients. Scandinavian journal of surgery : SJS : official organ for the Finnish Surgical Society and the Scandinavian Surgical Society. 2017: 126 [PMID: 27334795, https://doi.org/10.1177/1457496916654097]
8. Kamarajah SK, Bundred J, Spence G, Kennedy A, Dasari BVM, Griffiths EA. Critical Appraisal of the Impact of Oesophageal Stents in the Management of Oesophageal Anastomotic Leaks and Benign Oesophageal Perforations: An Updated Systematic Review. World journal of surgery. 2020: 1173 [PMID: 31686158, https://doi.org/10.1007/s00268-019-05259-6]
9. de Schipper JP, Pull ter Gunne AF, Oostvogel HJ, van Laarhoven CJ. Spontaneous rupture of the oesophagus: Boerhaave's syndrome in 2008. Literature review and treatment algorithm. Digestive surgery. 2009: 1 [PMID: 19145081, https://doi.org/10.1159/000191283]
10. Wannhoff A, Kouladouros K, Koschny R, Walter B, Zoll Z, Buringer K, Blank S, Schempf U, Caca K, Wichmann D. Endoscopic vacuum therapy for the treatment of Boerhaave syndrome: a multicenter analysis. Gastrointestinal endoscopy. 2025: 365 [PMID: 39218268, https://doi.org/10.1016/j.gie.2024.08.037]
11. Anundsen TK, Forland DT, Johannessen HO, Johnson E. Outcome after stent and endoscopic vacuum therapy-based treatment for postemetic esophageal rupture. Scandinavian journal of gastroenterology. 2024: 1 [PMID: 37592384, https://doi.org/10.1080/00365521.2023.2248537]
12. Vohra I, Gopakumar H, Sharma NR, Puli SR. Efficacy of endoscopic vacuum therapy in esophageal luminal defects: a systematic review and meta-analysis. Clinical endoscopy. 2025: 53 [PMID: 39385519, https://doi.org/10.5946/ce.2023.282]
13. Shea BJ, Reeves BC, Wells G, Thuku M, Hamel C, Moran J, Moher D, Tugwell P, Welch V, Kristjansson E, Henry DA. AMSTAR 2: a critical appraisal tool for systematic reviews that include randomised or non-randomised studies of healthcare interventions, or both. BMJ (Clinical research ed). 2017: j4008 [PMID: 28935701, https://doi.org/10.1136/bmj.j4008]
14. Slim K, Nini E, Forestier D, Kwiatkowski F, Panis Y, Chipponi J. Methodological index for non-randomized studies (minors): development and validation of a new instrument. ANZ journal of surgery. 2003: 712 [PMID: 12956787, https://doi.org/10.1046/j.1445-2197.2003.02748.x]
15. Wallace BC, Dahabreh IJ, Trikalinos TA, Lau J, Trow P, Schmid CH. Closing the Gap between Methodologists and End-Users:Ras a Computational Back-End. Journal of Statistical Software. 2012: 1 https://doi.org/10.18637/jss.v049.i05]
16. Chiu CH, Leow OQY, Wang YC, Chen WH, Fang HY, Chao YK, Lin J. Esophageal stenting with minimally-invasive surgical intervention for delayed spontaneous esophageal perforation. Journal of thoracic disease. 2023: 1228 [PMID: 37065549, https://doi.org/10.21037/jtd-22-1316]
17. Hauge T, Kleven OC, Johnson E, Hofstad B, Johannessen HO. Outcome after stenting and debridement for spontaneous esophageal rupture. Scandinavian journal of gastroenterology. 2018: 398 [PMID: 29523026, https://doi.org/10.1080/00365521.2018.1448886]
18. Aloreidi K, Patel B, Ridgway T, Yeager T, Atiq M. Non-surgical management of Boerhaave's syndrome: a case series study and review of the literature. Endoscopy international open. 2018: E92 [PMID: 29344568, https://doi.org/10.1055/s-0043-124075]
19. Huh CW, Kim JS, Choi HH, Lee JI, Ji JS, Kim BW, Choi H. Treatment of benign perforations and leaks of the esophagus: factors associated with success after stent placement. Surgical endoscopy. 2018: 3646 [PMID: 29442243, https://doi.org/10.1007/s00464-018-6096-1]
20. Glatz T, Marjanovic G, Kulemann B, Hipp J, Theodor Hopt U, Fischer A, Richter-Schrag HJ, Hoeppner J. Management and outcome of esophageal stenting for spontaneous esophageal perforations. Diseases of the esophagus : official journal of the International Society for Diseases of the Esophagus. 2017: 1 [PMID: 27790804, https://doi.org/10.1111/dote.12461]
21. Wu G, Zhao YS, Fang Y, Qi Y, Li X, Jiao D, Ren K, Han X. Treatment of spontaneous esophageal rupture with transnasal thoracic drainage and temporary esophageal stent and jejunal feeding tube placement. The journal of trauma and acute care surgery. 2017: 141 [PMID: 27805991, https://doi.org/10.1097/TA.0000000000001272]
22. Gubler C, Bauerfeind P. Self-expandable stents for benign esophageal leakages and perforations: long-term single-center experience. Scandinavian journal of gastroenterology. 2014: 23 [PMID: 24164499, https://doi.org/10.3109/00365521.2013.850735]
23. Persson S, Elbe P, Rouvelas I, Lindblad M, Kumagai K, Lundell L, Nilsson M, Tsai JA. Predictors for failure of stent treatment for benign esophageal perforations - a single center 10-year experience. World journal of gastroenterology. 2014: 10613 [PMID: 25132783, https://doi.org/10.3748/wjg.v20.i30.10613]
24. Schweigert M, Beattie R, Solymosi N, Booth K, Dubecz A, Muir A, Moskorz K, Stadlhuber RJ, Ofner D, McGuigan J, Stein HJ. Endoscopic stent insertion versus primary operative management for spontaneous rupture of the esophagus (Boerhaave syndrome): an international study comparing the outcome. The American surgeon. 2013: 634 [PMID: 23711276, https://doi.org/10.1177/000313481307900627]
25. Darrien JH, Kasem H. Minimally invasive endoscopic therapy for the management of Boerhaave's syndrome. Annals of the Royal College of Surgeons of England. 2013: 552 [PMID: 24165335, https://doi.org/10.1308/rcsann.2013.95.8.552]
26. Koivukangas V, Biancari F, Merilainen S, Ala-Kokko T, Saarnio J. Esophageal stenting for spontaneous esophageal perforation. The journal of trauma and acute care surgery. 2012: 1011 [PMID: 23026917, https://doi.org/10.1097/TA.0b013e318265d176]
27. Freeman RK, Van Woerkom JM, Vyverberg A, Ascioti AJ. Esophageal stent placement for the treatment of spontaneous esophageal perforations. The Annals of thoracic surgery. 2009: 194 [PMID: 19559223, https://doi.org/10.1016/j.athoracsur.2009.04.004]
28. Salminen P, Gullichsen R, Laine S. Use of self-expandable metal stents for the treatment of esophageal perforations and anastomotic leaks. Surgical endoscopy. 2009: 1526 [PMID: 19301070, https://doi.org/10.1007/s00464-009-0432-4]
29. Kim AW, Liptay MJ, Snow N, Donahue P, Warren WH. Utility of silicone esophageal bypass stents in the management of delayed complex esophageal disruptions. The Annals of thoracic surgery. 2008: 1962 [PMID: 18498803, https://doi.org/10.1016/j.athoracsur.2008.02.043]
30. Fischer A, Thomusch O, Benz S, von Dobschuetz E, Baier P, Hopt UT. Nonoperative treatment of 15 benign esophageal perforations with self-expandable covered metal stents. The Annals of thoracic surgery. 2006: 467 [PMID: 16427833, https://doi.org/10.1016/j.athoracsur.2005.08.047]
31. Prichard R, Butt J, Al-Sariff N, Frohlich S, Murphy S, Manning B, Ravi N, Reynolds JV. Management of spontaneous rupture of the oesophagus (Boerhaave's syndrome): single centre experience of 18 cases. Irish journal of medical science. 2006: 66 [PMID: 17312833, https://doi.org/10.1007/BF03167971]
32. Siersema PD, Homs MY, Haringsma J, Tilanus HW, Kuipers EJ. Use of large-diameter metallic stents to seal traumatic nonmalignant perforations of the esophagus. Gastrointestinal endoscopy. 2003: 356 [PMID: 14528208, https://doi.org/10.1067/s0016-5107(03)00008-7]
33. Chung MG, Kang DH, Park DK, Park JJ, Park HC, Kim JH. Successful treatment of Boerhaave's syndrome with endoscopic insertion of a self-expandable metallic stent: report of three cases and a review of the literature. Endoscopy. 2001: 894 [PMID: 11571689, https://doi.org/10.1055/s-2001-17325]
34. Wedemeyer J, Schneider A, Manns MP, Jackobs S. Endoscopic vacuum-assisted closure of upper intestinal anastomotic leaks. Gastrointestinal endoscopy. 2008: 708 [PMID: 18374029, https://doi.org/10.1016/j.gie.2007.10.064]
35. Loske G, Schorsch T, Muller C. Intraluminal and intracavitary vacuum therapy for esophageal leakage: a new endoscopic minimally invasive approach. Endoscopy. 2011: 540 [PMID: 21448855, https://doi.org/10.1055/s-0030-1256345]
36. Brangewitz M, Voigtlander T, Helfritz FA, Lankisch TO, Winkler M, Klempnauer J, Manns MP, Schneider AS, Wedemeyer J. Endoscopic closure of esophageal intrathoracic leaks: stent versus endoscopic vacuum-assisted closure, a retrospective analysis. Endoscopy. 2013: 433 [PMID: 23733727, https://doi.org/10.1055/s-0032-1326435]
37. Schniewind B, Schafmayer C, Voehrs G, Egberts J, von Schoenfels W, Rose T, Kurdow R, Arlt A, Ellrichmann M, Jurgensen C, Schreiber S, Becker T, Hampe J. Endoscopic endoluminal vacuum therapy is superior to other regimens in managing anastomotic leakage after esophagectomy: a comparative retrospective study. Surgical endoscopy. 2013: 3883 [PMID: 23708716, https://doi.org/10.1007/s00464-013-2998-0]
38. Bludau M, Holscher AH, Herbold T, Leers JM, Gutschow C, Fuchs H, Schroder W. Management of upper intestinal leaks using an endoscopic vacuum-assisted closure system (E-VAC). Surgical endoscopy. 2014: 896 [PMID: 24149851, https://doi.org/10.1007/s00464-013-3244-5]
39. Kuehn F, Schiffmann L, Janisch F, Schwandner F, Alsfasser G, Gock M, Klar E. Surgical Endoscopic Vacuum Therapy for Defects of the Upper Gastrointestinal Tract. Journal of gastrointestinal surgery : official journal of the Society for Surgery of the Alimentary Tract. 2016: 237 [PMID: 26643296, https://doi.org/10.1007/s11605-015-3044-4]
40. Laukoetter MG, Mennigen R, Neumann PA, Dhayat S, Horst G, Palmes D, Senninger N, Vowinkel T. Successful closure of defects in the upper gastrointestinal tract by endoscopic vacuum therapy (EVT): a prospective cohort study. Surgical endoscopy. 2017: 2687 [PMID: 27709328, https://doi.org/10.1007/s00464-016-5265-3]
41. Bludau M, Fuchs HF, Herbold T, Maus MKH, Alakus H, Popp F, Leers JM, Bruns CJ, Holscher AH, Schroder W, Chon SH. Results of endoscopic vacuum-assisted closure device for treatment of upper GI leaks. Surgical endoscopy. 2018: 1906 [PMID: 29218673, https://doi.org/10.1007/s00464-017-5883-4]
42. Alakkari A, Sood R, Everett SM, Rembacken BJ, Hayden J, Sarela A, Mohammed N. First UK experience of endoscopic vacuum therapy for the management of oesophageal perforations and postoperative leaks. Frontline gastroenterology. 2019: 200 [PMID: 31205665, https://doi.org/10.1136/flgastro-2018-101138]
43. Mastoridis S, Chana P, Singh M, Akbari K, Shalaby S, Maynard ND, Sgromo B. Endoscopic vacuum therapy (EVT) in the management of oesophageal perforations and post-operative leaks. Minimally invasive therapy & allied technologies : MITAT : official journal of the Society for Minimally Invasive Therapy. 2022: 380 [PMID: 32772610, https://doi.org/10.1080/13645706.2020.1801753]
44. Richter F, Hendricks A, Schniewind B, Hampe J, Heits N, von Schonfels W, Reichert B, Eberle K, Ellrichmann M, Baumann P, Egberts JH, Becker T, Schafmayer C. Eso-Sponge(R) for anastomotic leakage after oesophageal resection or perforation: outcomes from a national, prospective multicentre registry. BJS open. 2022: [PMID: 35451010, https://doi.org/10.1093/bjsopen/zrac030]
45. Luttikhold J, Pattynama LMD, Seewald S, Groth S, Morell BK, Gutschow CA, Ida S, Nilsson M, Eshuis WJ, Pouw RE. Endoscopic vacuum therapy for esophageal perforation: a multicenter retrospective cohort study. Endoscopy. 2023: 859 [PMID: 36828030, https://doi.org/10.1055/a-2042-6707]
46. Persson S, Rouvelas I, Irino T, Lundell L. Outcomes following the main treatment options in patients with a leaking esophagus: a systematic literature review. Diseases of the esophagus : official journal of the International Society for Diseases of the Esophagus. 2017: 1 [PMID: 28881894, https://doi.org/10.1093/dote/dox108]
Data Availability Statement
All the data is publicly available.
License
Copyright (c) 2025 Muhammad Saqib, Muhammad Iftikhar, Khaqan Ahmed, Humna Shahid, Shehr I Yar Khan, Muhammad Aamir Iqbal, Hassan Mumtaz

This work is licensed under a Creative Commons Attribution 4.0 International License.
Copyright and Licensing
All articles published in ASIDE Internal Medicine are open access and freely available online immediately upon publication, without embargo.
This journal applies the terms of the Creative Commons Attribution 4.0 International License (CC BY 4.0). Under this license, anyone may copy, redistribute, remix, transform, and build upon the material for any purpose, even commercially, provided that proper credit is given to the original author(s), a link to the license is provided, and any changes made are indicated.
-
License link: https://creativecommons.org/licenses/by/4.0/
-
Machine-readable license metadata is embedded in each article and its DOI record.
Copyright Holder
Copyright in all articles remains with the author(s). ASIDE Internal Medicine is published and owned by the American Society for Inclusion, Diversity, and Equity in Healthcare (ASIDE). By submitting a manuscript, authors agree to grant the publisher a non-exclusive license to publish, distribute, and archive the work under the terms of the CC BY 4.0 license.
Third-party Material
Any material (e.g., images, figures, or tables) not covered by CC BY 4.0 will be clearly indicated in the article. Users must obtain permission directly from the copyright holder for reuse of such third-party material.
Author Rights and Self-Archiving
Authors are permitted to deposit all versions of their work (preprint, author’s accepted manuscript, and version of record) in institutional or subject repositories of their choice immediately upon publication, without embargo, provided that the DOI and license information are included.

Published
Issue
Section
Categories
How to Cite
Article history
- Received
- 21 Apr 2025
- Received in revised form
- 3 Jul 2025
- Accepted
- 16 Jul 2025
- Published
- 26 Jul 2025
