
Improving Inpatient Care for Acute Chronic Obstructive Pulmonary Disease Exacerbations: A Quality Improvement Initiative
DOI:
https://doi.org/10.71079/ASIDE.IM.092025173Abstract
Background: Acute exacerbations of chronic obstructive pulmonary disease (AECOPD) account for high hospital use; guideline-concordant diagnostics, oxygen titration, and discharge planning are often under-delivered. We aim to measure baseline compliance with eight AECOPD process standards and evaluate whether EHR-embedded prompts plus staff education were associated with observed improvements.
Methods: We audited 50 consecutive adult admissions with primary AECOPD (ICD-10 J44.1 or clinician-documented diagnosis) between July and October 2024, implemented EHR prompts, an orderset, and targeted education (Nov–Dec 2024), then re-audited 50 consecutive admissions (Jan–Mar 2025) using identical methods. Primary process measures were pre-specified; analyses were descriptive with 95% Wilson confidence intervals (CIs) for proportions and two-sided Fisher exact tests for pre/post comparisons. This work was performed as a service evaluation/pilot.
Results: After implementation, six of eight process standards showed observed increases. Pulmonary rehabilitation referrals rose from 32/50 (64.0%, 95% CI 50.1–75.9%) to 43/50 (86.0%, 95% CI 73.8–93.0%), p = 0.0198. Oxygen titration improved from 40/50 (80.0%, 95% CI 66.0–88.6%) to 46/50 (92.0%, 95% CI 78.6–95.7%), p = 0.148. Other measures (ABG timing, bronchodilator and corticosteroid delivery, appropriate antibiotic use, CXR timing, smoking advice) showed observed improvements; p-values and CIs are reported in the text.
Conclusions: Embedding guideline-aligned prompts and an orderset in the EHR, together with staff education, was associated with observed improvements in several AECOPD process measures in this pilot QI project. Findings should be interpreted cautiously, given the pilot design, multiple comparisons, and limited sample size; further controlled and longitudinal evaluation is indicated.
Keywords:
COPD, Acute Exacerbation, Quality Improvement, Electronic Health Record, Pulmonary Rehabilitation, Smoking CessationFull Text
Introduction
Problem Description
Chronic obstructive pulmonary disease (COPD) is among the most common chronic illnesses encountered in internal medicine practice, responsible for high rates of morbidity, mortality, and healthcare utilization. Acute exacerbations of COPD (AECOPD) contribute disproportionately to this burden, representing up to 70% of hospital admissions among COPD patients and often resulting in prolonged hospital stays and avoidable readmissions [1,2,3,4]. Within our institution, informal staff discussions and case reviews identified inconsistencies in the inpatient management of AECOPD, particularly in the timely administration of key therapies, adherence to oxygen titration guidelines, and discharge planning.
Available Knowledge
National and international guidelines, particularly the GOLD and NICE NG115, outline best practices for AECOPD management [5,6,7,8]. These include early arterial blood gas (ABG) testing, rapid administration of short-acting bronchodilators and corticosteroids, judicious antibiotic use based on sputum characteristics and clinical findings, controlled oxygen delivery targeting SpO 88–92%, timely imaging to exclude other diagnoses, and referral to pulmonary rehabilitation. Despite this guidance, studies suggest that real-world practice often diverges from these standards due to a variety of system- and provider-level barriers. Recent reviews and audits have highlighted frequent issues with oxygen overuse, poor documentation, and under-referral to pulmonary rehab—findings consistent with our internal observations [9,10,11,12,13,14].
Rationale
Our team hypothesized that many of the observed care gaps stemmed from workflow inefficiencies and missed clinical prompts during high-pressure admissions. Given that our hospital had already adopted electronic prescribing and documentation systems, we reasoned that integrating clinical decision support tools, such as automatic prompts or checklists, into existing digital workflows could enhance compliance with evidence-based standards. In addition, educational reinforcement through departmental meetings and targeted communication was anticipated to improve clinical staff engagement and awareness.
Specific Aims
The primary aim of this quality improvement project was to assess our baseline compliance with key process standards for AECOPD management and implement low-cost, replicable interventions to address identified care gaps. We also aimed to measure the effectiveness of these interventions through a structured re-audit and generate actionable insights for future system-wide changes.
Methods
Organizational context
The project took place on a 650-bed tertiary academic hospital general medicine ward with an existing integrated EHR and in-house clinical informatics support. The clinical team included on-call respiratory specialists, ward physicians, nursing staff, physiotherapy (pulmonary rehabilitation), pharmacy, and an antimicrobial stewardship pharmacist who participated in the QI steering group.
Patient selection and case identification
We included consecutive adult patients (≥18 years) admitted to the general medicine ward with a primary diagnosis of acute exacerbation of COPD (AECOPD). Case identification relied on either clinician documentation of “COPD exacerbation” in admission or ED records or ICD-10 coding consistent with AECOPD (J44.1). Exclusion criteria were: primary diagnosis other than AECOPD, invasive mechanical ventilation instituted prior to the EHR trigger or admission for palliative care only. Some process measures had reduced denominators due to documentation availability (for example, antibiotic indication was not appraisable in 3 baseline patients, and smoking status was unavailable in 10 patients); we report the denominators for each measure in Tables 2–3 and describe the handling of incomplete documentation in the Results.
Interventions
Based on root cause analysis and staff feedback, four main interventions were introduced between November and December 2024. First, we implemented an oxygen prescription checklist embedded into the electronic prescribing system to improve documentation of target SpO₂ ranges and FiO₂. Second, we developed an automatic referral prompt for pulmonary rehabilitation that triggered at discharge for eligible patients. Third, we delivered guideline-focused education sessions to all medical and nursing staff. Finally, a pop-up reminder was added to the discharge summary module to ensure that documentation of smoking cessation advice is provided for current smokers. These interventions were co-designed with the respiratory team, clinical informatics unit, and physiotherapy department.
Acute inhaled therapy
The electronic orderset recommended a metered-dose inhaler (MDI) with a spacer as the preferred bronchodilator delivery method because of equivalent efficacy and logistical advantages (including lower aerosol generation). Nebulized bronchodilator therapy remained available and was permitted when MDI/spacer was not feasible or tolerated (for example, where patients were unable to coordinate inhalation, were highly agitated, or at the clinician’s discretion). We clarified this preference within the orderset and included a Table 1 footnote to reflect the local policy.
Antibiotic decision-making and stewardship.
The EHR prompt did not automatically prescribe antibiotics. Instead, the prompt and orderset presented guideline-based criteria to prompt clinician consideration of antibiotics (presence of increased sputum purulence, increased sputum volume, increased dyspnoea, temperature > 38°C, or radiographic consolidation). Final prescribing decisions remained at the discretion of the treating clinician. The hospital antimicrobial stewardship pharmacist subsequently reviewed all antibiotic prescriptions for the audit cohorts during the QI period, and stewardship feedback was communicated to treating teams when prescriptions appeared discordant with the indicated criteria.
Systemic corticosteroids.
The orderset included a recommended short-course systemic corticosteroid regimen consistent with contemporary guideline practice: oral prednisolone 40 mg once daily for 5 days (or an equivalent intravenous regimen when oral administration was not possible). An informational notice within the orderset prompted clinicians to review recent corticosteroid prescriptions in the record to avoid unnecessary cumulative oral corticosteroid exposure and to discourage prolonged tapers unless clinically justified.
Implementation and target selection.
Targets for each process indicator were selected by a multidisciplinary QI steering group (respiratory physicians, ward physicians, nurses, pharmacy, physiotherapy, and clinical informatics) using a pragmatic balance of ambition and feasibility informed by baseline performance. We used staged compliance thresholds (85% → 90% → 95%) to secure early, achievable wins and then progressively raise them in subsequent Plan-Do-Study-Act (PDSA) cycles. The choice of these operational targets was therefore locally informed rather than derived from a single external numerical standard; this approach followed the Model for Improvement and aimed to sustain momentum through iterative improvement.
QI framework and iterative approach.
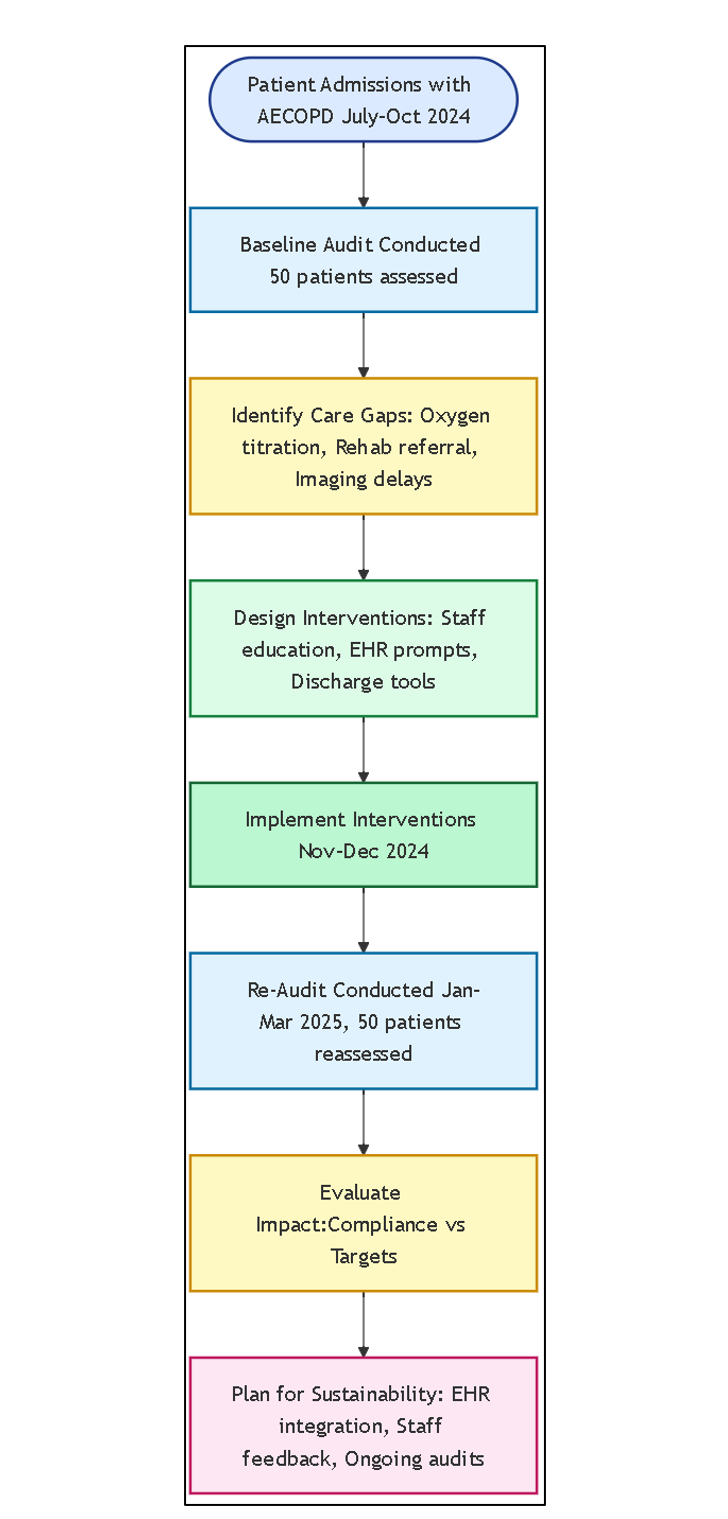
The QI project employed the Model for Improvement, utilizing rapid Plan-Do-Study-Act (PDSA) cycles. A multidisciplinary team (physicians, nurses, pharmacists, physiotherapists, and informatics specialists) met weekly during the implementation to review process measures, frontline feedback, and iterate on prompt wording, order defaults, and workflow. Figure 1 summarises the PDSA timeline.
Study of the Interventions
We employed a before-and-after audit design to assess the effectiveness of the intervention. Data were collected retrospectively for the baseline cohort (July–October 2024) and prospectively for the re-audit cohort (January–March 2025). Observed outcomes were compared to established targets to assess changes in compliance. Attribution of outcomes to interventions was supported by temporality, stability of external conditions, and qualitative feedback from clinical staff. Allocation and blinding. This was an uncontrolled before-and-after QI audit, and there was no randomization or blinding. Staff were aware of the interventions and audits (education sessions and EHR prompts), which may have influenced behaviour (see Limitations). To enhance transparency and reproducibility, a visual summary of the QI cycle is provided in Figure 1. This flowchart outlines the sequential steps of the quality improvement process, beginning with the baseline audit conducted from July to October 2024, followed by the identification of care gaps, the co-design of targeted interventions, and the implementation phase. The cycle concludes with the re-audit from January to March 2025 and subsequent planning for sustainability and scale-up. The figure illustrates how each phase informed the next, in line with the iterative principles of quality improvement methodology.
Measures
Eight process indicators were selected in accordance with international guidelines. These included: ABG within one hour of admission; nebulized bronchodilator administration within one hour; systemic corticosteroid prescription within four hours; appropriate antibiotic use based on clinical indication; oxygen therapy titrated to target saturation of 88–92% with documentation of FiO₂; chest X-ray within four hours; pulmonary rehab referral at discharge; and smoking cessation counseling for current smokers as shown in Table 1. Their guideline origins supported the validity of these measures, and data were abstracted using a structured form. Completeness and accuracy were assured through dual validation by two clinicians. Implementation fidelity and monitoring. We tracked fidelity using multiple process indicators: staff education attendance (percentage of targeted staff attending training sessions; 100% coverage reported); EHR log data confirming the display of the bedside prompt for triggered admissions; and orderset opening/acceptance rates (EHR log metric). In 88% of triggered admissions, the orderset was opened and used. These fidelity metrics are summarised in Supplementary Table S1.
| No. | Standard | Source | Target |
|---|---|---|---|
| 1 | ABG within 1 hour | NICE NG115 [7] | ≥90% |
| 2 | Nebulized bronchodilators within 1 hour | GOLD [8] | ≥90% |
| 3 | Corticosteroids within 4 hours | GOLD; NICE [5,7,8] | ≥95% |
| 4 | Antibiotics only if indicated | NICE NG115 [7] | ≥90% |
| 5 | Oxygen titration to SpO 88–92% | BTS [15] | ≥95% |
| 6 | Chest X-ray within 4 hours | NICE QS110 [5] | ≥90% |
| 7 | Pulmonary rehab referral | BTS [6] | ≥85% |
| 8 | Smoking cessation advice for smokers | USPSTF [16] | ≥90% |
NICE, National Institute of Health and Care Excellence; BTS, British Thoracic Society; GOLD, Global Initiative for Chronic Obstructive Lung Disease; USPSTF, United States Preventive Services Task Force. MDI = metered-dose inhaler. MDI with spacer was the preferred bronchodilator delivery method according to local orders; nebulized bronchodilator therapy was permitted only when MDI/spacer was contraindicated or not tolerated (e.g., inability to coordinate inhalation or severe agitation). Antibiotic decisions were made by treating physicians, guided by the order set criteria (see Methods), and were reviewed by the antimicrobial stewardship pharmacist.
Analysis
Descriptive statistics were used to summarize performance against each indicator. Pre- and post-intervention comparisons were made using percentage point differences. Confidence intervals were calculated for proportions. Given the sample size of 50 per audit cycle, we prioritized changes of more than 5% as potentially meaningful. Variations over time were examined through comparative tabulation. Analyses were primarily descriptive. For each process measure, we calculated proportions with 95% Wilson confidence intervals. For pre- and post-comparisons, we used two-sided Fisher’s exact tests, given the sample sizes and the presence of small cell counts in some measures. We did not apply multiplicity correction because these analyses were exploratory and hypothesis-generating; we therefore interpret p-values cautiously, mindful of the potential for type I error across multiple comparisons. No formal prospective sample-size calculation was performed; this activity was planned and conducted as a pilot/service evaluation to inform larger, more definitive future studies.
Ethical Considerations
The project was approved as a service evaluation and registered with the hospital’s clinical audit department (Registration# 2025-202). Formal ethics review was waived in accordance with institutional policy, as the project involved routine care data with no patient identifiers. The authors declared no conflicts of interest.
Reporting Standards
This quality improvement project is reported in accordance with the Standards for Quality Improvement Reporting Excellence (SQUIRE 2.0) guidelines [17]. The SQUIRE framework is specifically designed to guide the reporting of systematic efforts to improve healthcare quality, safety, and value in real-world clinical settings. A completed SQUIRE Checklist is provided in the supplementary materials to accompany this manuscript.
Results
Process Outcomes
At baseline (as shown in Table 2), compliance was highest for early administration of bronchodilators (92%) and initiation of corticosteroids (94%), indicating good adherence to acute pharmacotherapy. ABG sampling within one hour was achieved in 82% of patients. However, oxygen titration to SpO₂ 88–92% was documented in only 80% of cases, and only 64% of eligible patients were referred to pulmonary rehabilitation at discharge. The order set recommendation for a 5-day short course was followed in the majority of patients: 94% of treated patients received the recommended prednisolone 40 mg daily for 5 days. During the audit periods, 24 patients required noninvasive ventilation. A chest X-ray was obtained within four hours in 78% of cases. Among current smokers, documentation of cessation advice was noted in 87.5% of cases.
| Standard | Target | n/N | Compliance % (95% CI) | from Target |
|---|---|---|---|---|
| ABG within 1 hr. | ≥90% | 41/50 | 82.0% (69.0–90.6) | –8% |
| Nebulized bronchodilators <1 hr. | ≥90% | 46/50 | 92.0% (80.8–97.7) | +2% |
| Corticosteroids <4 hr. | ≥95% | 47/50 | 94.0% (83.5–98.8) | –1% |
| Appropriate antibiotics | ≥90% | 43/47 | 91.5% (79.6–97.6) | +1.5% |
| Oxygen titrated, SpO 88–92% | ≥95% | 40/50 | 80.0% (66.3–89.9) | –15% |
| Chest X-ray within 4 hr. | ≥90% | 39/50 | 78.0% (64.0–88.5) | –12% |
| Pulmonary rehab referral | ≥85% | 32/50 | 64.0% (49.2–77.1) | –21% |
| Smoking cessation advice | ≥90% | 35/40 | 87.5% (73.2–95.8) | –2.5% |
Δ, change or delta; ABG, arterial blood gas; CI, confidence interval; hr, hour; n/N, number achieving target/total number assessed; SpO₂, peripheral capillary oxygen saturation.
Following the interventions, compliance improved across all measures (shown in Table 3). The pulmonary rehab referral rate increased to 86%, meeting the target of 85% or higher. Oxygen titration documentation improved to 92%, reflecting gains but remaining just below the 95% goal. ABG and corticosteroid benchmarks were met, reaching 90% and 98%, respectively. Smoking cessation advice documentation exceeded the 90% target, rising to 95%.
| Standard | Target | Baseline % (95% CI) | Re-audit % (95% CI) | % | p value* | Target met? |
|---|---|---|---|---|---|---|
| ABG within 1 hr. | ≥90% | 82.0 (69.0–90.6) | 90.0 (78.2–96.7) | +8.0 | 0.27 | Yes |
| Nebs within 1 hr. | ≥90% | 92.0 (80.8–97.7) | 94.0 (83.5–98.8) | +2.0 | 1.00 | Yes |
| Corticosteroids within 4 hr. | ≥95% | 94.0 (83.5–98.8) | 98.0 (89.4–99.9) | +4.0 | 0.61 | Yes |
| Appropriate antibiotics | ≥90% | 91.5 (79.6–97.6) | 94.0 (83.5–98.8) | +2.5 | 1.00 | Yes |
| Oxygen titration | ≥95% | 80.0 (66.3–89.9) | 92.0 (80.8–97.7) | +12.0 | 0.11 | No |
| Chest X-ray within 4 hr. | ≥90% | 78.0 (64.0–88.5) | 88.0 (75.7–95.5) | +10.0 | 0.28 | No |
| Pulmonary rehab referral | ≥85% | 64.0 (49.2–77.1) | 86.0 (73.3–94.2) | +22.0 | 0.020 | Yes |
| Smoking cessation advice | ≥90% | 87.5 (73.2–95.8) | 95.0 (83.1–99.4) | +7.5 | 0.43 | Yes |
Δ, change or delta; ABG, arterial blood gas; CI, confidence interval; hr, hour; Nebs, nebulized bronchodilators; p value, probability value.
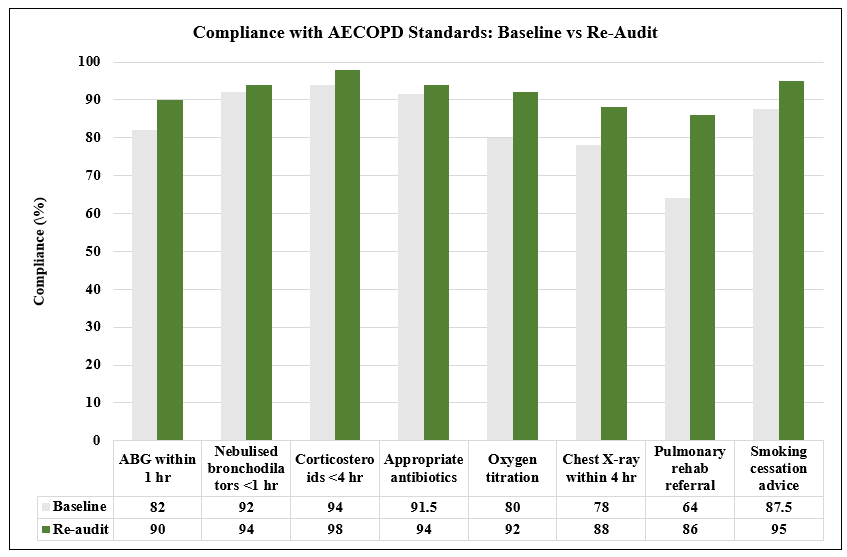
To illustrate the comparative impact of our interventions across key clinical standards, a clustered bar chart (Figure 2) was constructed showing baseline and re-audit compliance percentages for all eight audit measures. This visualization highlights notable improvements in pulmonary rehabilitation referrals, corticosteroid timing, and smoking cessation documentation, with more modest gains in oxygen titration and imaging. While most standards exceeded their target thresholds in the re-audit cycle, a few still fell short, underscoring the importance of continued iterative improvements.
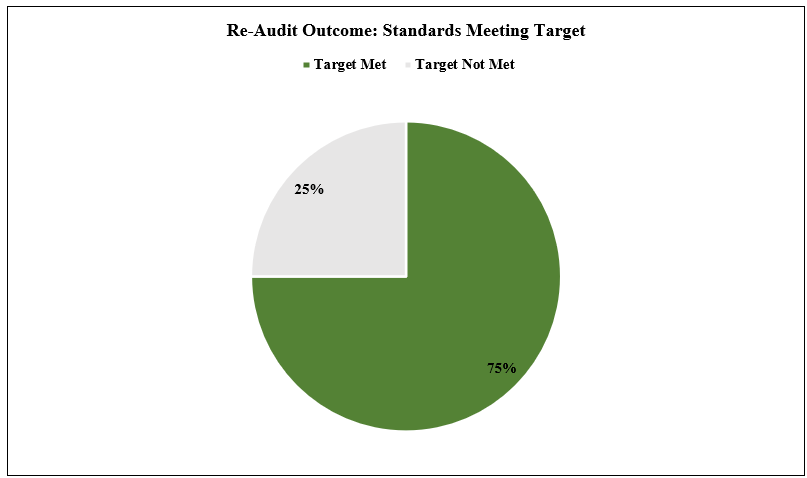
To summarize overall performance during the re-audit period, a pie chart (Figure 3) displays the proportion of care standards that met or did not meet predefined targets. Six of the eight standards achieved full compliance with benchmark criteria, demonstrating broad improvement across multiple domains of AECOPD care. The two remaining standards, oxygen titration and chest X-ray timing, showed progress but did not reach full compliance, indicating areas for further refinement.
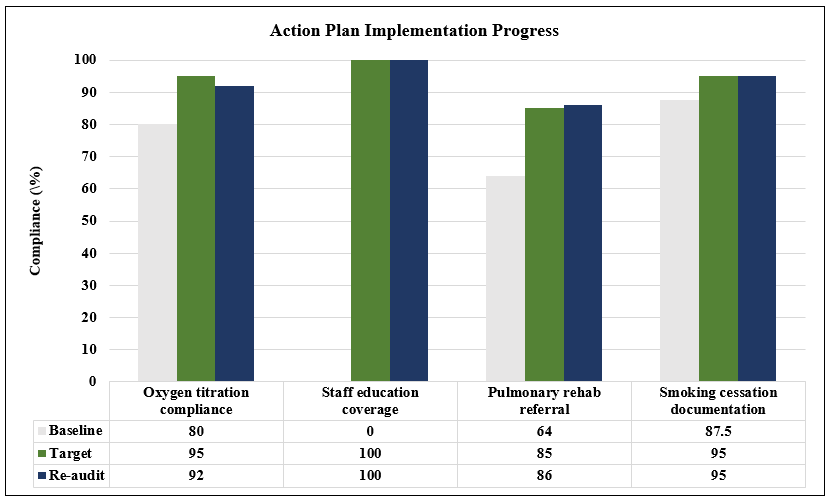
To better understand the impact of each intervention and assess progress toward predefined goals, we tracked key performance indicators aligned with our action plan. These included oxygen titration compliance, staff education coverage, pulmonary rehabilitation referral rates, and smoking cessation documentation. For each domain, we compared baseline performance with targets and re-audit results. Table 4 summarizes these metrics and highlights which objectives were fully achieved and which remained areas for continued improvement.
| Action Item | Baseline % (95% CI) | Target | Re-audit % (95% CI) | p value* | Status |
|---|---|---|---|---|---|
| Oxygen titration compliance | 80.0 (66.3–89.9) | ≥95% | 92.0 (80.8–97.7) | 0.11 | Partial |
| Staff education coverage | 0.0 (0.0–7.1) | 100% | 100.0 (92.9–100.0) | <0.001 | Achieved |
| Pulmonary rehab referral rate | 64.0 (49.2–77.1) | ≥85% | 86.0 (73.3–94.2) | 0.020 | Achieved |
| Smoking cessation documentation | 87.5 (73.2–95.8) | ≥95% | 95.0 (83.1–99.4) | 0.43 | Achieved |
CI, confidence interval; p value, probability value.
The following bar chart (Figure 4) displays the trajectory of four key intervention metrics: baseline status, predefined targets, and post-intervention compliance. Improvements in staff education, smoking cessation documentation, and pulmonary rehab referral rates all met or exceeded targets. Oxygen titration, while improved from baseline, fell slightly short of its target, highlighting an ongoing challenge in embedding oxygen therapy best practices into real-time clinical workflows.
Associations and Contextual Influences
The automated EHR prompts were consistently identified by staff as helpful in remembering care tasks during busy admissions. Feedback collected during clinical huddles confirmed that the oxygen checklist and discharge reminders resulted in improved documentation and care planning. Delays in chest X-ray performance were attributed to persistent bottlenecks in radiology transport and technician availability during peak hours. There were no unintended consequences, although two staff members noted occasional “alert fatigue” from excessive on-screen prompts.
Discussion
This quality improvement (QI) initiative demonstrated that structured, guideline-aligned interventions can meaningfully enhance the inpatient management of acute exacerbations of chronic obstructive pulmonary disease (AECOPD). By focusing on eight evidence-based process measures and implementing targeted changes across digital workflows, clinical education, and discharge planning, we were able to close care gaps within a short timeframe. The overall improvement observed in six of eight care standards underscores the feasibility and impact of low-cost, system-level interventions in improving care quality and equity for patients hospitalized with AECOPD.
One of the most striking findings was the substantial improvement in pulmonary rehabilitation (PR) referrals, which increased from 64% at baseline to 86% post-intervention, surpassing the 85% target. This success was directly attributable to the implementation of an automatic referral prompt within the electronic discharge summary. Historically, PR referrals are often neglected due to time constraints, lack of awareness, or assumptions about patient interest [18,19,20]. Our findings align with previous research showing that electronic reminders embedded within discharge workflows can significantly increase compliance with secondary prevention strategies in chronic disease care [21]. This is particularly important in COPD, where PR is strongly associated with reduced readmissions, improved exercise tolerance, and better quality of life [22,23]. Importantly, the intervention helped eliminate variability based on individual clinician practices and supported more equitable care delivery across all patients.
Improvement in oxygen titration practices was another major focus of our initiative. At baseline, only 80% of patients received oxygen titrated to a target SpO₂ of 88–92% with documented FiO₂, far below the BTS-recommended 95% threshold [15]. Following the introduction of an oxygen prescription checklist in the EHR and targeted staff education, compliance improved to 92%. Although this fell just short of our goal, the 12-percentage point gain is clinically meaningful and represents a major step toward safer oxygen prescribing. The emphasis on titrated oxygen is clinically important. Studies [24,25] indicate that titrated oxygen therapy (target SpO₂ 88–92%) reduces the risk of hypercapnic respiratory failure and associated adverse outcomes compared with liberal high-flow oxygen in patients at risk of CO₂ retention. Achieving and sustaining high compliance with oxygen targets therefore has direct safety implications for patients with AECOPD and remains a priority for future PDSA cycles [24,25]. Our intervention directly addressed the root cause, lack of FiO₂ documentation and unclear targets, by prompting prescribers at the point of care. However, achieving full compliance will likely require continued reinforcement and monitoring, particularly during handoffs and night shifts when documentation lapses may occur.
The timing of core pharmacologic interventions also improved. Administration of systemic corticosteroids within four hours of admission rose from 94% to 98%, and timely initiation of bronchodilators remained above 90% across both audit cycles. These findings indicate a strong baseline awareness of pharmacologic protocols among frontline providers, which was further supported by our educational sessions. The importance of timely corticosteroids in reducing exacerbation duration and hospitalization length has been well described, and our near-universal compliance is encouraging [26,27]. Similarly, appropriate antibiotic prescribing improved slightly, from 91.5% to 94%, reinforcing that clinicians are increasingly adopting an individualized approach based on purulent sputum and clinical infection markers, as recommended by GOLD and NICE.
Despite clear progress in several domains, two standards remained below target: chest X-ray completion within four hours (88% vs. 90% target) and oxygen titration compliance (92% vs. 95% target). The delay in chest imaging appears to be largely logistical. Informal feedback from nursing and medical staff pointed to porter availability and prioritization of other acutely unwell patients as contributing factors. Although we streamlined request pathways during the re-audit cycle, further improvements may require departmental-level coordination with radiology services. Introducing fast-track imaging protocols for medical admissions with respiratory compromise may be an effective next step.
The integration of a smoking cessation reminder into the discharge workflow proved highly successful, with documentation rates improving from 87.5% to 95%. This is consistent with prior work suggesting that digital nudges and automated prompts can reliably increase adherence to preventive counseling [28,29]. Smoking remains the most significant modifiable risk factor in COPD progression, and inpatient encounters represent a critical opportunity for intervention [30,31]. Our findings suggest that embedding such prompts into routine documentation processes minimizes omission and ensures consistency regardless of provider seniority or time constraints.
This project also contributes to the growing literature on digital quality improvement tools in internal medicine. Several studies have explored the impact of computerized decision support in chronic disease management, but relatively few have focused on acute care settings like AECOPD admissions [32,33,34,35,36,37,38,39,40]. Our experience highlights that with modest investment and stakeholder engagement, existing electronic health record platforms can be leveraged to embed real-time clinical decision support, improving both care delivery and equity. The interventions we implemented were designed to reduce variability stemming from individual clinician knowledge, shift patterns, or cognitive load—factors that disproportionately affect patients during unscheduled admissions. By standardizing care processes, we aim to reduce disparities and ensure that all patients receive evidence-based, guideline-concordant treatment.
Limitations
Several limitations warrant careful attention. First, this was a single-centre pilot before-and-after study with modest sample sizes (n = 50 per cycle); the study was not prospectively powered to detect small differences and may be at risk of type II error for some measures. Second, there was no randomization or concurrent control, so causal attribution to the interventions is limited; results may be affected by temporal confounding (seasonality, staffing patterns) or regression to the mean. Third, staff awareness of the project (Hawthorne effect) may have contributed to observed changes independent of the interventions. Fourth, although we tracked several fidelity metrics, consistent application of the interventions across all shifts could not be guaranteed; orderset open/use rates are presented in Supplementary Table S1 and remain an area for ongoing monitoring. Fifth, the re-audit was performed shortly after implementation and may not reflect long-term sustainability; longer follow-up is planned. Finally, we performed multiple exploratory comparisons and did not adjust for multiplicity; readers should interpret p-values alongside effect sizes and confidence intervals. Although our initial intervention prioritised acute in-hospital process measures, we collected data on several secondary preventive items (vaccination status, smoking cessation counselling and documented inhaler checks) and identified remaining opportunities. The orderset already includes optional fields to facilitate vaccination checks, structured inhaler technique education (nursing checklist and leaflet), smoking cessation referral and automatic pulmonary rehabilitation referral; these items are pre-specified for inclusion in subsequent PDSA cycles. Future work will evaluate uptake, barriers to completion (for example time pressures and resource constraints), and impact on patient-centred outcomes such as readmissions and functional recovery.
Despite these limitations, the sustainability of our interventions is promising. Because the core changes were embedded in digital workflows and did not require additional staffing or new infrastructure, they are likely to persist over time with minimal maintenance. The success of the pulmonary rehab auto-referral and smoking cessation documentation prompts provides a clear model for replicating this approach in other chronic disease pathways, such as heart failure or diabetes care. Additionally, the strong staff engagement we observed—reflected in positive feedback during team huddles—suggests a fertile environment for ongoing quality improvement efforts.
Our QI project demonstrates that meaningful improvements in the quality, safety, and equity of AECOPD inpatient care can be achieved through pragmatic, system-level interventions. The gains in PR referral, oxygen safety, and preventive counseling highlight the power of digital tools to close longstanding care gaps. Although this project focused on process measures, many of the improvements we observed are strongly linked to favourable patient-centred outcomes in the literature. For example, pulmonary rehabilitation referrals are associated with reduced readmissions and improved exercise capacity and quality of life, and systematic smoking cessation counselling increases long-term abstinence and reduces disease progression [9-11, 30]. We therefore anticipate that improved uptake of these processes will translate into meaningful patient benefits; as such, subsequent PDSA cycles will include prospective measurement of patient-centred outcomes (for example 30- and 90-day readmission, length of stay, validated symptom scores and patient experience metrics) to quantify clinical impact beyond process adherence. Continued work is needed to optimize imaging workflows and further enhance oxygen prescribing practices. More broadly, our approach offers a replicable template for other internal medicine services seeking to bridge the gap between evidence and practice.
Conclusions
This QI project highlights how focused, system-integrated interventions can enhance the timeliness, quality, and equity of AECOPD care. The work is likely to be sustainable given its reliance on EHR tools rather than high-resource staffing. With minimal adaptation, the approach could be extended to other respiratory or acute care pathways. Future studies should evaluate patient-centered outcomes such as readmission, recovery, and experience. Continued refinement of digital tools and expansion to additional care settings are key next steps.
Key finding
Embedding guideline-aligned prompts and an orderset in the EHR, together with staff education, was associated with observed improvements in several AECOPD process measures in this pilot QI project. Findings should be interpreted cautiously, given the pilot design, multiple comparisons, and limited sample size; further controlled and longitudinal evaluation is indicated.
From the authors' abstract.
中文摘要
改善急性慢性阻塞性肺疾病加重期住院护理:一项质量改进计划
背景:急性慢性阻塞性肺疾病加重(AECOPD)导致高住院率;符合指南的诊断、氧气滴定和出院计划往往执行不足。我们旨在测量八项AECOPD流程标准的基线合规率,并评估EHR嵌入提示加上员工教育是否与观察到的改进相关。
方法:我们在2024年7月至10月期间审计了50例连续成人主诊为AECOPD(ICD-10 J44.1或临床医生记录诊断)的住院病例,实施了EHR提示、订单集和针对性教育(2024年11–12月),随后在2025年1–3月使用相同方法重新审计50例连续入院病例。主要流程指标为预先指定;分析采用描述性统计,比例的95% Wilson置信区间(CIs)和双侧Fisher精确检验用于前后比较。本研究为服务评估/试点。
结果:实施后,八项流程标准中有六项显示观察到的提升。肺康复转诊率从32/50(64.0%,95% CI 50.1–75.9%)升至43/50(86.0%,95% CI 73.8–93.0%),p = 0.0198。氧气滴定从40/50(80.0%,95% CI 66.0–88.6%)升至46/50(92.0%,95% CI 78.6–95.7%),p = 0.148。其他指标(ABG时机、支气管舒张剂和皮质类固醇给药、适当抗生素使用、胸片时机、戒烟建议)亦显示观察到的改进;p值和CIs见正文。
结论:在EHR中嵌入符合指南的提示和订单集,并配合员工教育,关联于本试点QI项目中多项AECOPD流程指标的观察到的改进。鉴于试点设计、多重比较和样本量有限,结果应谨慎解读;建议进一步进行受控和纵向评估。
本中文摘要为机器辅助翻译,仅供参考;以英文摘要为准。 Machine-assisted Chinese translation of the English abstract; the English abstract is the version of record.
References
1. Chow L, Parulekar AD, Hanania NA. Hospital management of acute exacerbations of chronic obstructive pulmonary disease. Journal of hospital medicine. 2015: 328 [PMID: 25820201, https://doi.org/10.1002/jhm.2334]
2. Chow R, So OW, Im JHB, Chapman KR, Orchanian-Cheff A, Gershon AS, Wu R. Predictors of Readmission, for Patients with Chronic Obstructive Pulmonary Disease (COPD) - A Systematic Review. International journal of chronic obstructive pulmonary disease. 2023: 2581 [PMID: 38022828, https://doi.org/10.2147/COPD.S418295]
3. Langfeld K. World Lung Day 2019: Respiratory Groups Unite to Call for Healthy Lungs for All 2019. Available from: https://goldcopd.org/news/page/4/#:~:text=384%20million%20people%20suffer%20from,very%20young%20and%20very%20old.
4. Press VG, Au DH, Bourbeau J, Dransfield MT, Gershon AS, Krishnan JA, Mularski RA, Sciurba FC, Sullivan J, Feemster LC. Reducing Chronic Obstructive Pulmonary Disease Hospital Readmissions. An Official American Thoracic Society Workshop Report. Annals of the American Thoracic Society. 2019: 161 [PMID: 30707066, https://doi.org/10.1513/AnnalsATS.201811-755WS]
5. QS110 Pneumonia in adults: National Institute of Health and Care Excellence; [updated 19-January-2016]. Available from: https://www.nice.org.uk/guidance/qs110/chapter/quality-statement-3-chest-xray-and-diagnosis-within-4-hours-of-hospital-presentation.
6. Bolton CE, Bevan-Smith EF, Blakey JD, Crowe P, Elkin SL, Garrod R, Greening NJ, Heslop K, Hull JH, Man WD-C, Morgan MD, Proud D, Roberts CM, Sewell L, Singh SJ, Walker PP, Walmsley S, British Thoracic Society Pulmonary Rehabilitation Guideline Development Group obotBTSSoCC. British Thoracic Society guideline on pulmonary rehabilitation in adults: accredited by NICE2013: ii1 Thorax. https://doi.org/10.1136/thoraxjnl-2013-203808]
7. National Institute for Health and Care Excellence. NG115 Chronic obstructive pulmonary disease in over 16s: diagnosis and management [Internet]. National Institute for Health and Care Excellence; 2019 [updated 26-July-2019; cited 2025 2025]. Available from: https://www.nice.org.uk/guidance/ng115.
8. Kostikas K, Hillas G, Gogali A. 2025 GOLD Report: What is New and What is Noteworthy for the Practicing Clinician. COPD. 2025: 2451613 [PMID: 39912681, https://doi.org/10.1080/15412555.2025.2451613]
9. Aldhahir AM, Alghamdi SM, Alqahtani JS, Alqahtani KA, Al Rajah AM, Alkhathlan BS, Singh SJ, Mandal S, Hurst JR. Pulmonary rehabilitation for COPD: A narrative review and call for further implementation in Saudi Arabia. Annals of thoracic medicine. 2021: 299 [PMID: 34820017, https://doi.org/10.4103/atm.atm_639_20]
10. Cox NS, Oliveira CC, Lahham A, Holland AE. Pulmonary rehabilitation referral and participation are commonly influenced by environment, knowledge, and beliefs about consequences: a systematic review using the Theoretical Domains Framework. J Physiother. 2017: 84 [PMID: 28433238, https://doi.org/10.1016/j.jphys.2017.02.002]
11. Lusuardi M, Garuti G, Massobrio M, Spagnolatti L, Borciani N. The audit-intervention-reaudit cycle can improve diagnostic standards for chronic obstructive pulmonary disease (COPD). Internal and emergency medicine. 2014: 113 [PMID: 23636565, https://doi.org/10.1007/s11739-013-0952-8]
12. Man WD, Puhan MA, Harrison SL, Jordan RE, Quint JK, Singh SJ. Pulmonary rehabilitation and severe exacerbations of COPD: solution or white elephant? ERJ Open Res. 2015: 00050 [PMID: 27730157, https://doi.org/10.1183/23120541.00050-2015]
13. Price LC, Lowe D, Hosker HS, Anstey K, Pearson MG, Roberts CM, British Thoracic S, the Royal College of Physicians Clinical Effectiveness Evaluation U. UK National COPD Audit 2003: Impact of hospital resources and organisation of care on patient outcome following admission for acute COPD exacerbation. Thorax. 2006: 837 [PMID: 16449268, https://doi.org/10.1136/thx.2005.049940]
14. Suarez-Gonzalez P, Suarez-Elosegui A, Arias-Fernandez L, Perez-Regueiro I, Jimeno-Demuth FJ, Lana A. Nursing diagnoses and hospital readmission of patients with respiratory diseases: Findings from a case-control study. Nursing open. 2024: e2182 [PMID: 38783599, https://doi.org/10.1002/nop2.2182]
15. O'Driscoll BR, Howard LS, Earis J, Mak V, British Thoracic Society Emergency Oxygen Guideline G, Group BTSEOGD. BTS guideline for oxygen use in adults in healthcare and emergency settings. Thorax. 2017: ii1 [PMID: 28507176, https://doi.org/10.1136/thoraxjnl-2016-209729]
16. US Preventive Services Task Force. Interventions for Tobacco Smoking Cessation in Adults, Including Pregnant Persons: US Preventive Services Task Force Recommendation Statement. JAMA. 2021: 265 https://doi.org/10.1001/jama.2020.25019]
17. Ogrinc G, Davies L, Goodman D, Batalden P, Davidoff F, Stevens D. SQUIRE 2.0 (Standards for QUality Improvement Reporting Excellence): revised publication guidelines from a detailed consensus process2016: 986 BMJ Quality & Safety. https://doi.org/10.1136/bmjqs-2015-004411]
18. Augustine A, Bhat A, Vaishali K, Magazine R. Barriers to pulmonary rehabilitation - A narrative review and perspectives from a few stakeholders. Lung India : official organ of Indian Chest Society. 2021: 59 [PMID: 33402639, https://doi.org/10.4103/lungindia.lungindia_116_20]
19. Qi J, Cai Q, Zhang W, Gu Y. Effects of pulmonary telerehabilitation in patients with chronic obstructive pulmonary disease. Chinese medical journal. 2025: 1493 [PMID: 40413618, https://doi.org/10.1097/CM9.0000000000003650]
20. Thakor M, Singh V, Manifield J, Orme MW, Bhardwaj P, Chauhan NK, Barradell AC, Ahmed Z, Bhati Y, Matheson J, Barton A, Sharma AK, Singh SJ. Community-Based Pulmonary Rehabilitation in an Economically Deprived Area of Jodhpur, India: A Mixed-Methods Feasibility Trial. International journal of chronic obstructive pulmonary disease. 2025: 473 [PMID: 40041473, https://doi.org/10.2147/COPD.S488766]
21. Willis VC, Thomas Craig KJ, Jabbarpour Y, Scheufele EL, Arriaga YE, Ajinkya M, Rhee KB, Bazemore A. Digital Health Interventions to Enhance Prevention in Primary Care: Scoping Review. JMIR medical informatics. 2022: e33518 [PMID: 35060909, https://doi.org/10.2196/33518]
22. Press VG, Nici L. Improving Pulmonary Rehabilitation Participation: It's Time to Examine the System. Annals of the American Thoracic Society. 2024: 1655 [PMID: 39601503, https://doi.org/10.1513/AnnalsATS.202410-1003ED]
23. Rochester CL, Alison JA, Carlin B, Jenkins AR, Cox NS, Bauldoff G, Bhatt SP, Bourbeau J, Burtin C, Camp PG, Cascino TM, Dorney Koppel GA, Garvey C, Goldstein R, Harris D, Houchen-Wolloff L, Limberg T, Lindenauer PK, Moy ML, Ryerson CJ, Singh SJ, Steiner M, Tappan RS, Yohannes AM, Holland AE. Pulmonary Rehabilitation for Adults with Chronic Respiratory Disease: An Official American Thoracic Society Clinical Practice Guideline. American journal of respiratory and critical care medicine. 2023: e7 [PMID: 37581410, https://doi.org/10.1164/rccm.202306-1066ST]
24. Echevarria C, Steer J, Wason J, Bourke S. Oxygen therapy and inpatient mortality in COPD exacerbation. Emerg Med J. 2021: 170 [PMID: 33243839, https://doi.org/10.1136/emermed-2019-209257]
25. Kelly CA, Maden M. How do health-care professionals perceive oxygen therapy? A critical interpretive synthesis of the literature. Chronic respiratory disease. 2015: 11 [PMID: 25492978, https://doi.org/10.1177/1479972314562408]
26. Putcha N, Wise RA. Medication Regimens for Managing COPD Exacerbations. Respiratory care. 2018: 773 [PMID: 29794210, https://doi.org/10.4187/respcare.05912]
27. Woods JA, Wheeler JS, Finch CK, Pinner NA. Corticosteroids in the treatment of acute exacerbations of chronic obstructive pulmonary disease. International journal of chronic obstructive pulmonary disease. 2014: 421 [PMID: 24833897, https://doi.org/10.2147/COPD.S51012]
28. Nurchis MC, Di Pumpo M, Perilli A, Greco G, Damiani G. Nudging Interventions on Alcohol and Tobacco Consumption in Adults: A Scoping Review of the Literature. International journal of environmental research and public health. 2023: [PMID: 36767077, https://doi.org/10.3390/ijerph20031675]
29. Sumner J, Bundele A, Lim HW, Phan P, Motani M, Mukhopadhyay A. Developing an Artificial Intelligence-Driven Nudge Intervention to Improve Medication Adherence: A Human-Centred Design Approach. Journal of medical systems. 2023: 3 [PMID: 38063940, https://doi.org/10.1007/s10916-023-02024-0]
30. Paulin LM, Halenar MJ, Edwards KC, Lauten K, Taylor K, Brunette M, Tanski S, MacKenzie T, Stanton CA, Hatsukami D, Hyland A, Mahoney MC, Niaura R, Trinidad D, Blanco C, Compton W, Gardner LD, Kimmel HL, Cummings KM, Lauterstein D, Roh EJ, Marshall D, Sargent JD. Relationship Between Tobacco Product Use and Health-Related Quality of Life Among Individuals With COPD in Waves 1-5 (2013-2019) of the Population Assessment of Tobacco and Health Study. Chronic obstructive pulmonary diseases (Miami, Fla). 2024: 68 [PMID: 38113525, https://doi.org/10.15326/jcopdf.2023.0422]
31. Wu J, Sin DD. Improved patient outcome with smoking cessation: when is it too late? International journal of chronic obstructive pulmonary disease. 2011: 259 [PMID: 21814462, https://doi.org/10.2147/COPD.S10771]
32. Chen W, Howard K, Gorham G, O'Bryan CM, Coffey P, Balasubramanya B, Abeyaratne A, Cass A. Design, effectiveness, and economic outcomes of contemporary chronic disease clinical decision support systems: a systematic review and meta-analysis. Journal of the American Medical Informatics Association : JAMIA. 2022: 1757 [PMID: 35818299, https://doi.org/10.1093/jamia/ocac110]
33. Dijk SW, Wollny C, Barkhausen J, Jansen O, Mildenberger P, Halfmann MC, Stroeder J, Rizopoulos D, Hunink MGM, Kroencke T. Evaluation of a Clinical Decision Support System for Imaging Requests: A Cluster Randomized Clinical Trial. JAMA. 2025: 1212 [PMID: 39928308, https://doi.org/10.1001/jama.2024.27853]
34. Fujita K, Hooper P, Masnoon N, Lo S, Gnjidic D, Etherton-Beer C, Reeve E, Magin P, Bell JS, Rockwood K, O'Donnell LK, Sawan M, Baysari M, Hilmer SN. Impact of a Comprehensive Intervention Bundle Including the Drug Burden Index on Deprescribing Anticholinergic and Sedative Drugs in Older Acute Inpatients: A Non-randomised Controlled Before-and-After Pilot Study. Drugs & aging. 2023: 633 [PMID: 37160561, https://doi.org/10.1007/s40266-023-01032-6]
35. Huang S, Liang Y, Li J, Li X. Applications of Clinical Decision Support Systems in Diabetes Care: Scoping Review. Journal of medical Internet research. 2023: e51024 [PMID: 38064249, https://doi.org/10.2196/51024]
36. Roshanov PS, Misra S, Gerstein HC, Garg AX, Sebaldt RJ, Mackay JA, Weise-Kelly L, Navarro T, Wilczynski NL, Haynes RB, Team CSR. Computerized clinical decision support systems for chronic disease management: a decision-maker-researcher partnership systematic review. Implementation science : IS. 2011: 92 [PMID: 21824386, https://doi.org/10.1186/1748-5908-6-92]
37. Sommers S, Tolle H, Napier C, Hoppe J. Targeted messaging to improve the adoption of clinical decision support for prescription drug monitoring program use. Journal of the American Medical Informatics Association : JAMIA. 2023: 1711 [PMID: 37433582, https://doi.org/10.1093/jamia/ocad127]
38. Velickovski F, Ceccaroni L, Roca J, Burgos F, Galdiz JB, Marina N, Lluch-Ariet M. Clinical Decision Support Systems (CDSS) for preventive management of COPD patients. Journal of translational medicine. 2014: S9 [PMID: 25471545, https://doi.org/10.1186/1479-5876-12-S2-S9]
39. Ventura F, Sousa P, Dixe MA, Ferreira P, Martinho R, Dias SS, Morais J, Goncalves LM. A Clinical Decision Support System for Remote Monitoring of Cardiovascular Disease Patients: A Clinical Study Protocol. Frontiers in public health. 2022: 859890 [PMID: 35615041, https://doi.org/10.3389/fpubh.2022.859890]
40. Xi H, Zhang Y, Zuo R, Li W, Zhang C, Sun Y, Ji H, He Z, Chang C. Forecasting Hospitalization for Adult Asthma Patients in Emergency Departments Based on Multiple Environmental and Clinical Factors. Journal of asthma and allergy. 2025: 861 [PMID: 40469908, https://doi.org/10.2147/JAA.S512405]
Data Availability Statement
The data that support the findings of this study are available from the corresponding author upon reasonable request. De-identified patient-level data used in the audit and quality improvement analysis are retained in secure institutional repositories and may be shared with qualified researchers, subject to institutional approvals and data-sharing agreements. No individual-level patient-identifiable information is publicly available in compliance with institutional and ethical policies.
License
Copyright (c) 2025 Khaqan Ahmed, Afaq Ahmad, Muhammad Saqib, Muhammad Iftikhar, Humna Shahid

This work is licensed under a Creative Commons Attribution 4.0 International License.
Copyright and Licensing
All articles published in ASIDE Internal Medicine are open access and freely available online immediately upon publication, without embargo.
This journal applies the terms of the Creative Commons Attribution 4.0 International License (CC BY 4.0). Under this license, anyone may copy, redistribute, remix, transform, and build upon the material for any purpose, even commercially, provided that proper credit is given to the original author(s), a link to the license is provided, and any changes made are indicated.
-
License link: https://creativecommons.org/licenses/by/4.0/
-
Machine-readable license metadata is embedded in each article and its DOI record.
Copyright Holder
Copyright in all articles remains with the author(s). ASIDE Internal Medicine is published and owned by the American Society for Inclusion, Diversity, and Equity in Healthcare (ASIDE). By submitting a manuscript, authors agree to grant the publisher a non-exclusive license to publish, distribute, and archive the work under the terms of the CC BY 4.0 license.
Third-party Material
Any material (e.g., images, figures, or tables) not covered by CC BY 4.0 will be clearly indicated in the article. Users must obtain permission directly from the copyright holder for reuse of such third-party material.
Author Rights and Self-Archiving
Authors are permitted to deposit all versions of their work (preprint, author’s accepted manuscript, and version of record) in institutional or subject repositories of their choice immediately upon publication, without embargo, provided that the DOI and license information are included.

Additional Files
Published
How to Cite
Article history
- Received
- 12 Jul 2025
- Received in revised form
- 15 Aug 2025
- Accepted
- 31 Aug 2025
- Published
- 20 Sep 2025
