
Adjunctive Remotely Supervised tDCS in Multiple Sclerosis: A GRADE-Assessed Meta-Analysis of Sham-Controlled Trials on Cognitive, Fatigue, Mobility, and Quality-of-Life Outcomes
DOI:
https://doi.org/10.71079/ASIDE.IM.042526637Abstract
Background: Multiple sclerosis (MS) is an immune-mediated disorder characterized by demyelination within the central nervous system, resulting in fatigue, pain, cognitive dysfunction, and motor impairment. Remotely supervised transcranial direct current stimulation (RS‑tDCS) is a noninvasive, low-cost, home-based intervention that modulates neuronal excitability and enhances neural network function, potentially benefiting individuals with MS. This meta-analysis aimed to evaluate the efficacy of RS‑tDCS in MS.
Methods: A systematic search was conducted in PubMed, Web of Science, Scopus, and the Cochrane Library for randomized controlled trials (RCTs) evaluating RS‑tDCS in MS. The primary outcome was information‑processing speed. Statistical analyses were performed using R software (version 4.5.0) and a random‑effects model to calculate pooled standardized mean differences (SMDs) and mean differences (MDs) with 95% confidence intervals (CIs). Risk of bias was assessed using the Cochrane ROB‑2 tool.
Results: Five RCTs, most featuring co-interventions alongside RS-tDCS in both study arms and one specifically targeting MS patients with cannabis use disorder, including 291 participants, were analyzed. Active RS‑tDCS did not significantly improve information‑processing speed (SMD = 0.20; 95% CI: –0.06 to 0.45; P = 0.13, n studies: 4). No significant effects were observed for secondary outcomes.
Conclusion: Evidence from five heterogeneous RCTs, predominantly featuring co-interventions, shows no clear benefit of RS-tDCS for MS cognitive or functional outcomes (very low to low certainty). This highlights substantial uncertainty; larger standalone trials are required.
Keywords:
Multiple sclerosis, MS, Remotely supervised transcranial direct current stimulation, RS-tDCSFull Text
Introduction
Multiple sclerosis (MS) is a chronic, immune-mediated condition of the central nervous system that leads to demyelination and neurodegeneration. It is the most common chronic neurological disease among young adults, especially women, affecting nearly 3 million people worldwide and resulting in over 62,000 cases annually [1].
MS pathophysiology is complex and not yet fully understood, with various genetic predispositions and environmental triggers [2]. The main symptoms include numbness, motor dysfunction, fatigue, pain, and cognitive changes, among others. These symptoms can significantly affect daily life activities and differ in severity and duration throughout the patient’s lifetime [3].
Although several treatment options are available, there is currently no definitive cure for MS. Available medications aim to reduce relapses and symptom effects [4]. The cornerstone of MS treatment is pharmacological management, including disease-modifying therapies (DMTs) such as interferon-beta, glatiramer acetate, and newer agents like ocrelizumab and alemtuzumab [5]. Additionally, corticosteroids are used to treat acute relapses, and various symptomatic treatments help manage chronic symptoms [6].
However, these medications can be associated with adverse effects like hematological disorders, serious adverse events, withdrawals from treatment plans, high costs, and incomplete response rates, emphasizing the need for a combination of multiple strategies [7,8].
Neuromodulation is an emerging pillar of multiple sclerosis management that can be combined with pharmacological prescriptions [9]. It influences nerve activity by using physical stimuli, specifically transcranial direct current stimulation (tDCS) [10]. tDCS is a non-invasive technique that uses constant, low-current electrical stimulation applied by electrodes on the scalp; it modulates neuronal activity and enhances neural network function [11]. tDCS demonstrated promising results in reducing multiple sclerosis symptoms. Clinical meta-analyses and randomized controlled trials (RCTs) indicate that tDCS may improve fatigue, cognitive performance, pain, balance, and gait ability in MS patients [12,13].
tDCS is routinely performed in hospital settings, but recent developments have enabled remote, home-based applications in patient care combined with other interventions such as cognitive training, virtual reality, mindfulness meditation, and dexterity training. This may allow a greater number of MS patients to access this specialized care while reducing the costs and challenges associated with regular clinic-based treatments, especially for those who live far away from specialized centers or have limited mobility [14].
To date, no systematic review or meta-analysis has specifically evaluated remotely supervised, home-based transcranial direct current stimulation (tDCS) in multiple sclerosis (MS). The existing reviews either combined a variety of tDCS administration methods or multiple neurological or psychiatric [12,14,10]. Therefore, by assessing the efficacy of adjunctive remotely supervised tDCS in MS populations, we hope to methodically close this gap. However, available RS-tDCS RCTs feature heterogeneous patient subgroups (including comorbidities like cannabis use disorder), co-interventions (cognitive training, virtual reality, mindfulness meditation, and dexterity training), and mixed objectives, challenges of indirectness that this GRADE-assessed meta-analysis addresses through pooled synthesis and subgroup analyses.
Methods
Protocol and Registration
This systematic review and meta-analysis adhered to the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) guidelines [15] and the Cochrane guidelines [16]. The study protocol was prospectively registered in the International Prospective Register of Systematic Reviews (PROSPERO) database (ID: CRD420251178143).
Inclusion and Exclusion Criteria
Adults (≥18 years) diagnosed with MS were included. The intervention involved RS-tDCS, either alone or with other interventions, irrespective of stimulation parameters such as intensity and duration. The remote supervision component begins with an initial in-clinic training session that instructs participants on device operation, headset assembly, saline preparation, and includes a tolerability assessment. Then, a live video conference is conducted, during which the study technician visually verifies correct headset and electrode placement using reference images and provides a single-use unlock code only after setup approval. The devices are preprogrammed with automatic safety shutdowns in the event of poor contact and include session logging to prevent unauthorized dosage modifications. The comparator was sham tDCS. The primary outcome was information processing speed, measured by the Symbol Digit Modalities Test (SDMT). Secondary outcomes included functional mobility assessed by the Timed Up & Go test, fatigue evaluated using the PROMIS scale, and quality of life measured through the Multiple Sclerosis Quality of Life (MSQOL) questionnaire. Only randomized controlled trials (RCTs) were considered eligible. Exclusion criteria comprised non-RCTs, prospective or retrospective cohort studies, case reports, case series, conference abstracts, narrative reviews, animal studies, studies on neurodegenerative diseases other than MS, and non-English publications.
Search Strategy and Screening
A detailed search of the literature was carried out using several online databases, including PubMed, Cochrane Library, Web of Science, and Scopus from their inception to September 2025, using the following search strategy: (("transcranial direct current stimulation" OR tDCS OR "direct current stimulation" OR "neuromodulation") AND ("remote" OR "remotely supervised" OR "home-based" OR "at-home" OR telehealth OR telemedicine OR telerehabilitation OR "self-administered") AND ("multiple sclerosis" OR MS)) We removed the duplicates using EndNote software version X9 [17]. After using Rayyan software to independently screen titles and abstracts, the reviewers screened full texts for studies that seemed potentially eligible [18]. Any discrepancies were resolved through discussion or consultation with a third supervising author. The selection procedure followed specified predefined inclusion and exclusion criteria.
Data Extraction
The authors used an online Google spreadsheet to independently extract data, and a supervising author settled any disputes. Extracted data were mainly divided into four domains: (1) study characteristics, (2) characteristics of the population in the included studies, (3) risk of bias domains, and (4) study outcomes. The necessary data were reported directly in the text, so no additional extraction tool was required.
Risk of Bias Assessment and Certainty of Evidence
We assessed the risk of bias in the included studies using the Cochrane Risk of Bias 2 Tool (ROB 2) across five domains (e.g., randomization, blinding, outcome reporting) [19]. Each study was independently assessed by two reviewers, with a third reviewer resolving any disagreements.
The GRADE (Grading of Recommendations Assessment, Development and Evaluation) methodology was used to evaluate the quality of the evidence for the primary and secondary outcomes [20]. The summary of findings table was generated using GRADEpro GDT software [21]. Assessments were performed independently by two reviewers, and disagreements were resolved through discussion or by involving a third supervising reviewer. We classified the certainty of evidence as high, moderate, low, or very low, based on GRADE domains: risk of bias, inconsistency, indirectness, imprecision, and publication bias. GRADE profile Summary of Findings tables were produced and made available as supplemental data (Supplementary Table 1: GRADE assessment).
Outcome Measures
Primary Outcome
Information processing speed: reporting using SDMT. Scores were reported either as z-scores or raw scores, and higher scores are better. For consistency, scores reported on different scales were pooled as standardized mean differences (SMD) to account for variability in outcome measures. Subgroup analyses were performed according to the area of RS-tDCS stimulation and the montage-based taxonomy (symmetric bicephalic montage, unilateral anode with contralateral supraorbital reference, or bifrontal montage).
Secondary Outcomes
We synthesize the outcomes that were reported in more than one trial. The TUG test is used to measure functional mobility, and lower scores are better; Fatigue was assessed using the PROMIS Fatigue Short Form 7a in included studies, and the change from baseline to end of treatment was pooled as a raw score mean difference using the same instrument and timepoint definition across studies, and lower scores are better; and the MSQOL questionnaire is used to measure quality of life, and higher scores are better. For consistency, TUG and MSQOL results were pooled as SMD due to the variability in outcome measures, while PROMIS results were pooled as mean differences (MD).
Evidence Synthesis
We synthesized the data by first extracting and summarizing key details from each study, such as characteristics of the studies and participants, active RS-tDCS protocols (e.g., area of stimulation, montage-based taxonomy), and sham tDCS protocols. To maintain clarity, we organized the results according to stimulation parameters. The team identified and discussed any discrepancies or ambiguous methodological reporting. By grouping the findings thematically, we aimed to reveal patterns, including whether particular stimulation regions or RS-tDCS montage-based taxonomy corresponded with variations in outcomes.
All statistical analyses were performed using R software (version 4.5.0). As we expected differences in protocols across studies, we predefined the use of a DerSimonian-Laird random-effects model to calculate combined estimates and Hartung-Knapp adjustment disabled (hakn = FALSE) in R (package meta). We chose this model because it accurately captures real-world variability among patient groups, intervention procedures, and study variations. Continuous outcomes were reported as MD or SMD with 95% confidence intervals. We applied SMD when combining studies that measured the same outcome using different scales (e.g., SDMT was reported as either z-scores or raw scores), because SMD standardizes effect sizes across varying measurement methods. In contrast, MD was used when outcomes were measured on the same scale across studies. All outcomes in this analysis were continuous, and we assessed the change from baseline to the final time point, and in the case of stratified multi-group data, as Charvet 2025, we excluded the open-label design. For studies reporting multiple subgroups (e.g., low vs. high EDSS), we combined these into a single study estimate for the primary analysis. Heterogeneity was assessed using the chi-squared test and the I² statistic; we considered P values of 0.1 and I² > 50% indicative of substantial variability [22]. When significant heterogeneity was detected, we performed a sensitivity analysis to assess how individual studies influenced the overall findings [23]. SDMT was investigated in subgroup analyses based on the area of tDCS stimulation and montage-based taxonomy (symmetric bicephalic montage, unilateral anode with contralateral supraorbital reference, or bifrontal montage). To reliably detect publication bias in meta-analyses, Sterne et al. suggest assessing funnel plot asymmetry with at least ten studies [24]. Since our main analysis includes fewer than 10 studies, we cannot assess publication bias using this method.
Results
Study Selection
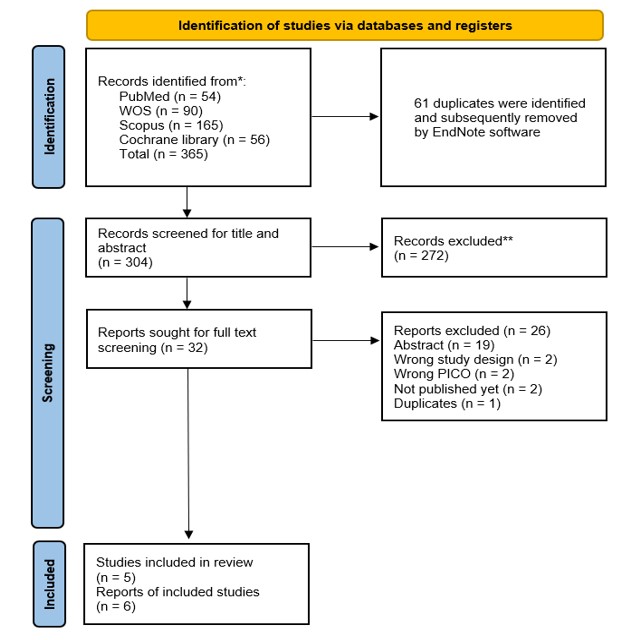
We performed a comprehensive search of relevant databases, which revealed 365 records. After removing 61 duplicate records, we screened the titles and abstracts and excluded 272 studies because they did not meet the inclusion criteria. Then we screened the full text of 32 studies, excluding 26 for reasons specified in the PRISMA flow diagram Figure 1. The final systematic review and meta-analysis included five unique RCTs (published across six reports: Charvet et al. 2018; Pilloni et al. 2024; Pilloni et al. 2025; Pagliari et al. 2025; Charvet et al. 2025 (1); Charvet et al. 2025 (2), the last two reports are the same RCT).
Study Characteristics
Five RCTs were selected for inclusion in the systematic review, involving 291 patients with MS. Four studies were conducted in the USA, and only one in Italy. And one specifically targeting MS patients with cannabis use disorder. The primary outcome was information processing speed, measured using the SDMT. Table 1 summarizes the key characteristics of the included studies. The baseline characteristics of the included patients are summarized in Table 2. Among 291 patients across five studies, the mean age was 53.06 years, with males comprising 25.9% of the patients. The mean Expanded Disability Status Scale (EDSS) was 4.55, and the mean disease duration was 13.67 years, suggesting a chronic, moderate disability.
Risk of Bias of Included Studies
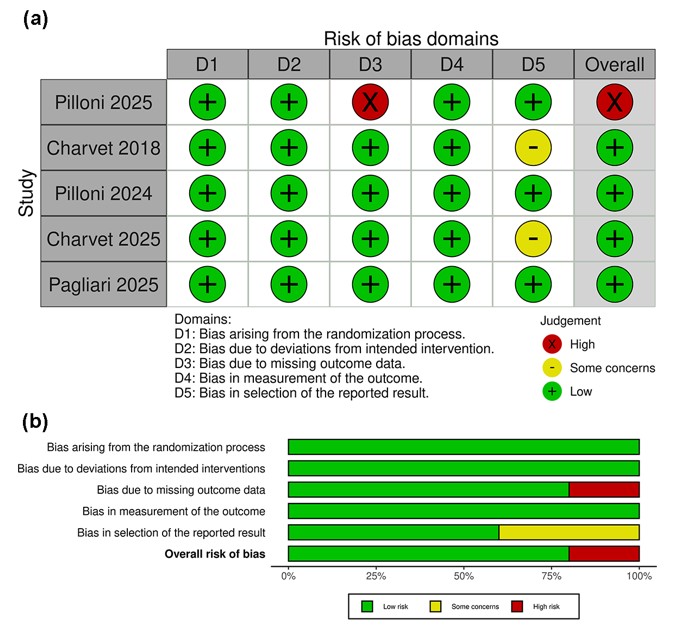
Using the ROB 2 tool across the five RCTs, four [25,26,27,28] revealed an overall low risk of bias, and only Pilloni 2025 et al. [29] showed high risk of bias due to issues with missing outcome data. Figure 2 presents both the ROB graph and summary.
Analysis of the Primary Outcome
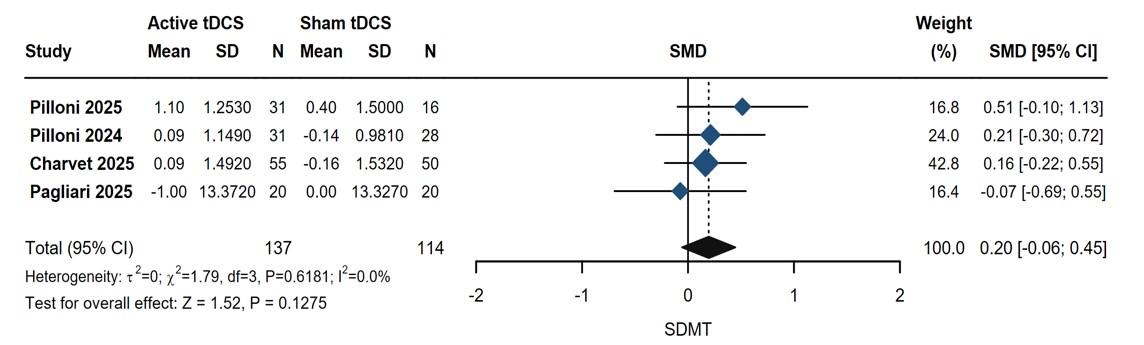
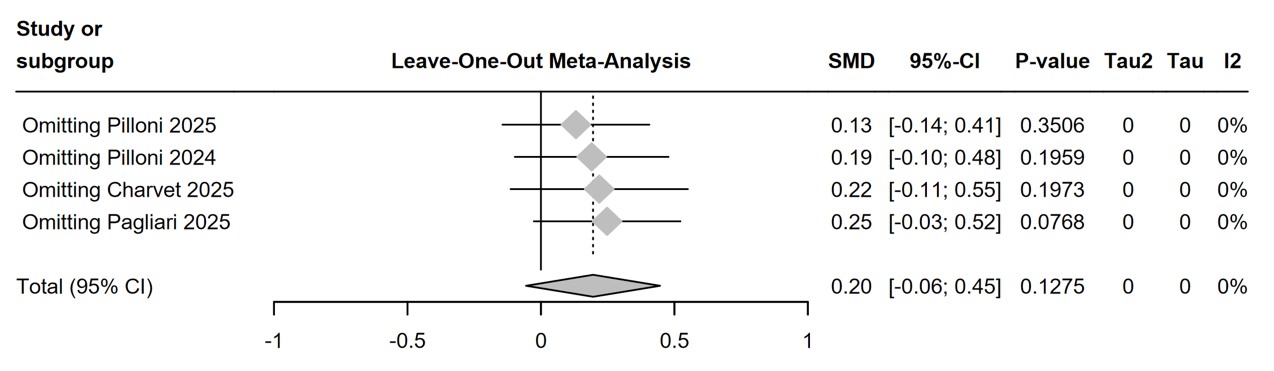
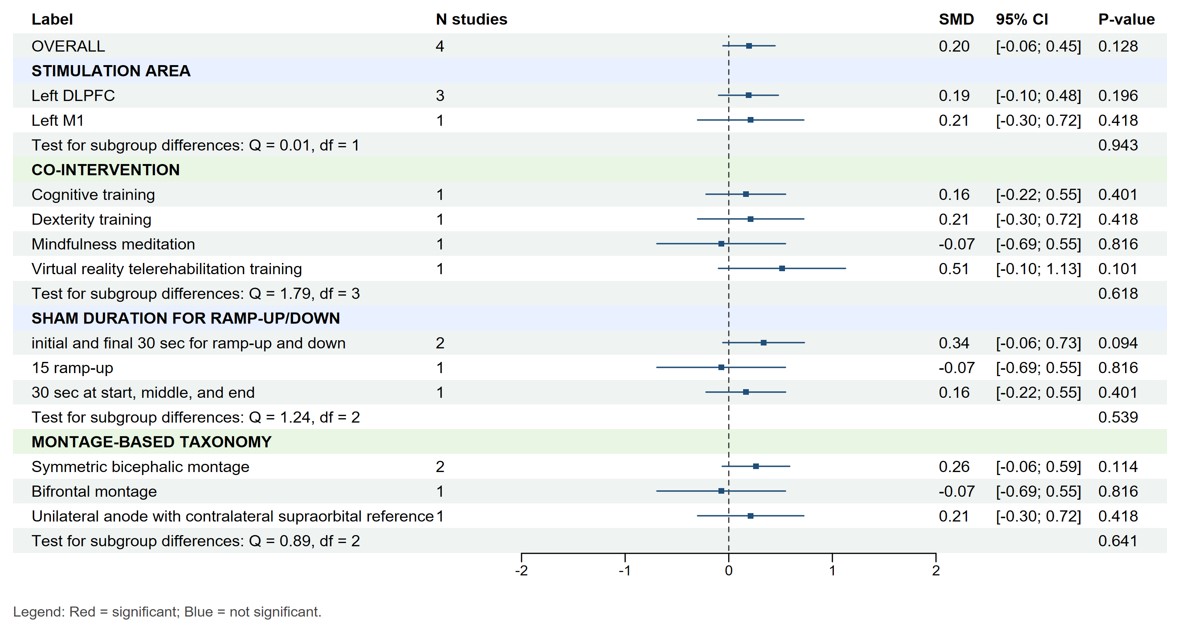
A meta-analysis with 137 patients in the active group and 114 in the sham group assessed how well RS-tDCS improved information processing speed. The meta-analysis resulted in a non-significant improvement in SDMT, with an SMD of 0.20 (95% CI: [-0.06, 0.45]; P = 0.1275, n studies: 4) and low heterogeneity (I² = 0%, P = 0.62) Figure 3. The leave-one-out sensitivity analysis yielded non-significant results in all cases Figure 4. To examine whether the difference in montage-based taxonomy (symmetric bicephalic montage, unilateral anode with contralateral supraorbital reference, or bifrontal montage) could explain the non-significant results, we conducted a subgroup analysis based on the montage-based taxonomy. The subgroup analysis also showed a non-significant improvement in all subgroups Figure 5. Subgroup analysis based on stimulation area, either dorsolateral prefrontal cortex (DLPFC) or motor cortex (M1), was conducted. Results showed a non-significant improvement in both subgroups Figure 5. Another subgroup analysis according to the co-intervention was conducted, showing a non-significant improvement in all subgroups Figure 5. According to the variation in sham protocols, we conducted a subgroup analysis according to the sham duration for ramp-up/down to explore whether this variation explains the non-significant results; the results showed a non-significant effect in all sham protocols Figure 5. Based on the GRADE approach, the certainty of evidence was rated as very low.
Analysis of Secondary Outcomes
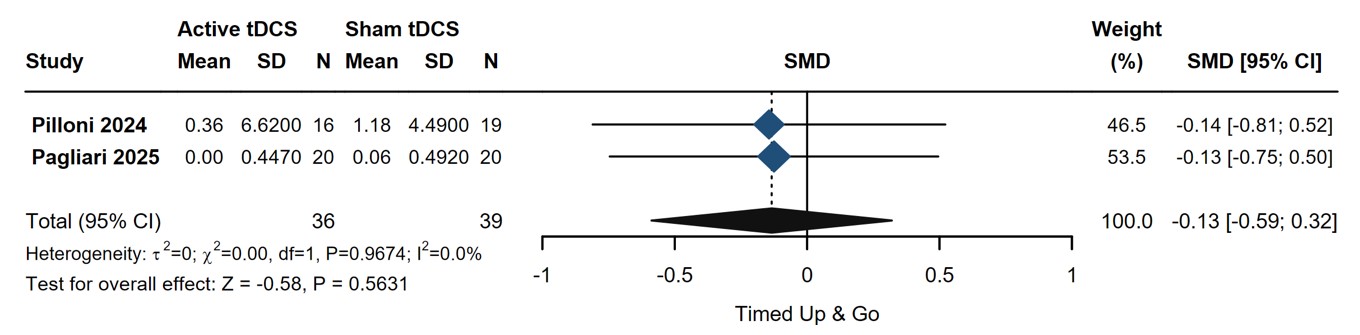
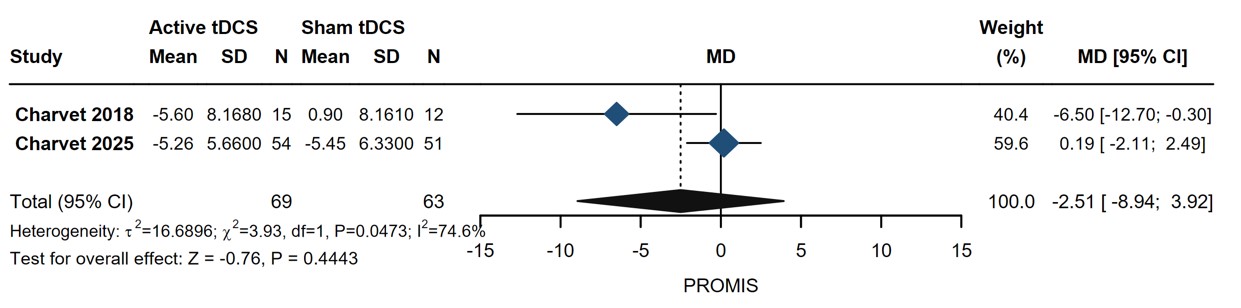
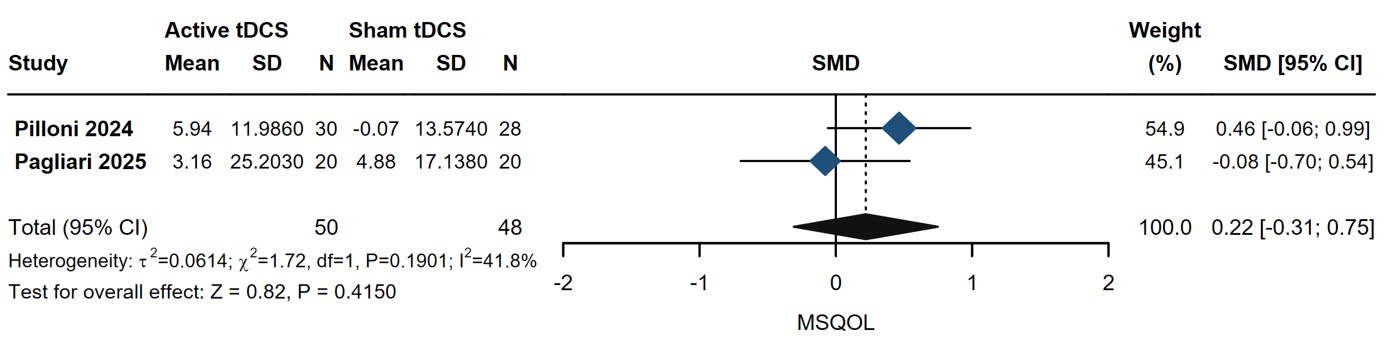
Further analysis of secondary outcomes was conducted to investigate the efficacy of RS-tDCS in functional mobility, fatigue, and quality of life using the Timed Up & Go test, PROMIS scale, and MSQOL questionnaire, respectively. The analysis showed a non-significant improvement in all outcomes with an SMD of -0.13 (95% CI: [-0.59, 0.32]; P = 0.56) Figure 6, an MD of -2.51 (95% CI: [-8.94, 3.92]; P = 0.44) Figure 7, and an SMD of 0.22 (95% CI: [-0.31, 0.75]; P = 0.42) Figure 8, respectively. High heterogeneity was observed for fatigue (I² = 75%, P = 0.05), likely due to variations in stimulation protocols across studies. The certainty of evidence was rated as low, very low, and low, respectively.
| Study ID | Country | Total N | Summary of inclusion criteria | Montage-based taxonomy | Active group protocol | Sham group protocol | Other interventions | Area of stimulation | No. of sessions | Supervision/ Fidelity/ Adherence | Outcomes and measurement tools | Summary of the study |
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Pilloni 2025 [29] | USA | 47 | The study includes adults aged 21-65 diagnosed with relapsing-remitting multiple sclerosis and mild to moderate neurological disability who have been stable on medications for at least one month. They have Cannabis Use Disorder per DSM-V, experience mild to moderate distress, and aim to reduce or stop cannabis use. | Symmetric bicephalic montage | Electrical current ramped up to 2 mA (30 seconds), remained constant (19 minutes), and ramped down (30 seconds). | 2 mA, 20 min/session, total 60 sec for ramp-up/down | Mindfulness meditation in both groups | left DLPFC | 20/4 weeks | Live technicians oversee every session with identity/setup verification; SNAPstrap DLPFC headset visually checked; device logs stimulation time/intensity; 83% completed ≥14/20 sessions. | Efficacy (DFAQ-CU), withdrawal symptoms (CWS), MS-related symptoms (SymptoMScreen), cognitive performance (SDMT) | This pilot RCT supports the feasibility and preliminary efficacy of telehealth tDCS in a medical subpopulation. |
| Charvet 2018 [25] | USA | 27 | Adults aged 18–70 with a confirmed MS diagnosis (any subtype, in remission if relapsing–remitting), physically, visually, and cognitively able to complete procedures (SDMT z ≤-3.0), EDSS ≤ 6.5 or with caregiver assistance, and at least 1 month post-steroid use or relapse | bicephalic montage | 2.0 mA stimulation (1.5 mA if they could not tolerate 2.0 mA during the tolerability test at baseline). | Ramp up to 2.0 mA and back down during the first and last minutes of the session. | - | left DLPFC | 20/4 weeks | Live video supervision of all sessions; Soterix device with single-use unlock codes and session logs; daily pain/AE ratings pre/during/post; stop if pain≥7/10; ≥8/10 sessions required for analysis; high compliance reported | FSS, PROMIS, visual analog fatigue ratings, BDI | This RCT shows statistically significant reductions in fatigue for the active group. |
| Pilloni 2024 [28] | USA | 60 | Ages 18–70 with progressive MS, EDSS ≤7.5, right-hand dominant, at least mild manual dexterity impairment (normative z-score ≤1.0 on 9-HPT). | Unilateral anode with contralateral supraorbital reference | Direct current at 2.0 mA for a duration of 20 minutes. | Ramp-up/down period of target 2.0 mA electrical current for the initial and final 60 seconds | Dexterity training in both groups | left M1-SO | 20/4 weeks | Live video all sessions; Soterix device with unlock codes + logs; daily safety checks; high feasibility with rapid recruitment & compliance | VAS, 9-HPT, DMMPUT, TPDS, MGPST, T25FWT, TUG, SDMT, PANAS, MS-QOL. | Home M1-SO tDCS enhances training outcomes and offers a promising intervention for improving and preserving hand dexterity. |
| Charvet 2025 [26] | USA | 117 | Adults aged 18–75 with definite MS, moderate fatigue, low depression, adequate cognition, no major comorbidities, medically cleared for tDCS, and relapse-free for one month. | Symmetric bicephalic montage | The device was programmed to automatically ramp up to 2 mA over 30 seconds, maintain that intensity for 19 minutes, then ramp down over 30 seconds. | Brief 60-second ramp-up and ramp-down phases at the start, middle, and end of each 20-minute session, without providing actual brain stimulation. | Cognitive training in both groups | left DLPFC | 30/6 weeks | Daily video verification of headset assembly/saline preparation; pre-programmed devices with 3-ramp sham and safety abort; continuous monitoring during BrainHQ training; 92% completed ≥25/30 sessions | Primary outcome: Change in PROMIS Fatigue score. Secondary outcomes: MFIS for physical, cognitive, and psychosocial fatigue. Safety: Pain and adverse events. | Home-based tDCS combined with cognitive training was well tolerated but showed no additional benefit over cognitive training alone in reducing MS-related fatigue. |
| Pagliari 2025 [27] | Italy | 40 | Ages 25–70, Italian native speakers, ≥8 years of education, right-handed, EDSS ≤6.5, no relapses or steroid use in the past 3 months, no visual/hearing impairments affecting rehab, and no tDCS contraindications (metal implants, pacemaker, seizure, head trauma, epilepsy, or stroke). | Bifrontal montage | Participants received real stimulation (2 mA for 20 min) during 5 sessions (Monday–Friday). Electrodes were placed over F3 (anode) and F4 (cathode). Sessions were supervised online, and safety and sensations were checked after each session. | 20-minute sessions, but the current was turned off after 15 seconds while the timer continued. This kept participants blinded. | Virtual reality telerehabilitation training in both groups | left DLPFC | 5/week | Synchronous therapist guidance during telerehabilitation sessions; smartphone photo reference for F3-F4 electrode placement; daily AE questionnaire post-session; median 28/30 sessions completed (93% adherence) | Primary outcome: Motor function measured by Mini-BESTest. Secondary outcomes: Gross manual dexterity (Box and Block Test), walking ability (12-item MS Walking Scale), cognitive function (SDMT), anxiety (STAI), depression (BDI). | Home-based RS-tDCS combined with telerehabilitation was well tolerated, enhanced gait and balance, and reduced anxiety but showed no impact on cognitive function, fatigue, or depression in patients with MS. |
MS, multiple sclerosis; SDMT, Symbol Digit Modalities Test; EDSS, Expanded Disability Status Scale; 9-HPT, Nine-Hole Peg Test; mA, milliampere; DLPFC, dorsolateral prefrontal cortex; M1, primary motor cortex; CWS, Cannabis Withdrawal Syndrome; FSS, Fatigue Severity Scale; PROMIS, Patient-Reported Outcomes Measurement Information System; VAS, Visual Analogue Scale; BDI, Beck Depression Inventory; DMPMUT, Difficult Manual Performance Manipulation Upper Test; TPDS, Time Per Digit Symbol; MGPST, Modified Grooved Pegboard Speed Test; T25FWT, Timed 25-Foot Walk Test; TUG, Timed Up and Go test; PANAS, Positive and Negative Affect Schedule; MS-QOL, Multiple Sclerosis Quality of Life; MFIS, Modified Fatigue Impact Scale; MoCA, Montreal Cognitive Assessment; STAI, State-Trait Anxiety Inventory.
| Study ID | Groups | Total Sample Size in Each Group | Males n (%) | Age mean (SD) | Disease duration | Baseline EDSS score | Baseline SDMT |
|---|---|---|---|---|---|---|---|
| Pilloni 2025 [29] | Active tDCS | 31 | 0 (0) | 41.5 (10.4) | 8.6 (8.1) | - | -1.9 (1.2) z-score |
| Sham tDCS | 16 | 0 (0) | 45.6 (8.9) | 8.4 (5.4) | - | -2.0 (1.5) z-score | |
| Charvet 2018 [25] | Active tDCS | 15 | 7 (46) | 44.8 (16.2) | 15.8 (9.4) | 4.75 (2.012) | - |
| Sham tDCS | 12 | 4 (33) | 43.4 (16.2) | 13.3 (11.3) | 3.875 (2.599) | - | |
| Pilloni 2024 [28] | Active tDCS | 31 | 10 (32.3) | 55.23 (8.73) | 17.14 (12.55) | 5.125 (1.46) | -0.85 (1.24) z-score |
| Sham tDCS | 29 | 7 (24.1) | 53.69 (7.73) | 16.57 (11.09) | 4.6 (1.629) | -0.83 (0.10) z-score | |
| Charvet 2025 [26] | Sham tDCS, EDSS: Low | 33 | 5 (15.2) | 45.06 (13.06) | - | - | -1.17 (1.17) z-score |
| Active tDCS, EDSS: Low | 35 | 8 (22.9) | 45.37 (13.04) | - | - | -0.62 (1.22) z-score | |
| Sham tDCS, EDSS: High | 23 | 5 (21.7) | 54.30 (7.87) | - | - | -1.12 (1.40) z-score | |
| Active tDCS, EDSS: High | 26 | 8 (30.8) | 53.65 (9.74) | - | - | -1.98 (1.42) z-score | |
| Pagliari 2025 [27] | Active tDCS | 20 | 7 (35) | 51.60 (8.46) | 14.15 (9.42) | 4.46 (2.29) | 45 (13.37) raw |
| Sham tDCS | 20 | 10 (50) | 47.55 (11.56) | 15.30 (10.14) | 4.5 (2.39) | 40 (13.32) raw |
tDCS, transcranial direct current stimulation; EDSS, Expanded Disability Status Scale; SDMT, Symbol Digit Modalities Test.
Discussion
This systematic review and meta-analysis evaluated the efficacy of RS-tDCS in individuals with MS, synthesizing evidence from five randomized controlled trials involving 291 participants with moderate disability and long disease duration. Overall, pooled analyses showed no significant RS-tDCS benefit across heterogeneous trials featuring co-interventions (4/5) and mixed objectives (cannabis subgroup in 1/5), limiting indirectness for standalone RS-tDCS efficacy in core MS domains.
The Pilloni et al. (2025) pilot trial represents a distinct clinical scenario, targeting MS patients with comorbid cannabis use disorder seeking substance reduction rather than core MS symptom management. This study’s unique patient population and primary objective limit its generalizability to broader MS therapeutic questions, warranting cautious interpretation within the pooled analyses.
Nevertheless, several individual trials reported domain-specific benefits, particularly reductions in fatigue, improvements in hand dexterity following primary motor cortex stimulation, and enhanced gait, balance, and anxiety outcomes when RS-tDCS was combined with structured rehabilitation or virtual reality-based telerehabilitation.
The biological rationale for RS-tDCS in MS lies in its ability to modulate cortical excitability and promote neuroplasticity through NMDA receptor-dependent mechanisms, potentially compensating for disrupted neural networks caused by demyelination and neurodegeneration [30,31].
These findings suggest that RS-tDCS may have adjunctive value when paired with task-oriented interventions rather than functioning as a standalone therapy. Across all studies, high adherence rates were observed [32,33,34].
Anodal stimulation of the dorsolateral prefrontal cortex and primary motor cortex has been shown to influence cognitive, motor, and affective domains by enhancing functional connectivity and corticospinal output [35,36]. Compared with earlier clinic-based studies, RS-tDCS enables extended stimulation protocols and broader participation, with emerging evidence supporting selective benefits when combined with rehabilitation strategies [37,38]. A subgroup analysis based on the sham protocol showed no difference between all subgroups. For more consistency, we suggest using a more active-feeling sham protocol in future trials to minimize between-group differences, so participants can’t easily tell if it’s active or sham.
Interpretation of these findings is limited by substantial heterogeneity across studies, including variability in stimulation parameters, cortical targets, number of sessions, number of patients and studies, indirect populations, concurrent adjunctive behavioral interventions, and outcome measures. Subgroup analyses did not yield significant improvements in SDMT performance, underscoring the exploratory nature of this meta-analysis. The small number of sham-controlled trials and short follow-up durations further limit certainty regarding long-term efficacy. Additional evidence search limitations include English-only publication restrictions and a lack of trial registry/grey literature searches, potentially missing non-English or unpublished data. Future research should focus on adequately powered, multicenter trials with standardized protocols, longer follow-up, and integration of neuroimaging or neurophysiological biomarkers to clarify therapeutic specificity and optimize personalized RS-tDCS interventions.
Conclusion
Current sham-controlled evidence does not demonstrate a clear benefit for pooled outcomes of RS-tDCS in MS. Future trials should test standardized RS-tDCS protocols within clearly defined standalone versus adjunctive treatment frameworks.
Key finding
Evidence from five heterogeneous RCTs, predominantly featuring co-interventions, shows no clear benefit of RS-tDCS for MS cognitive or functional outcomes (very low to low certainty). This highlights substantial uncertainty; larger standalone trials are required.
From the authors' abstract.
中文摘要
远程监督经颅直流电刺激在多发性硬化中的辅助作用:一项基于GRADE评估的假对照试验认知、疲劳、移动性和生活质量结果的荟萃分析
背景:多发性硬化(MS)是一种免疫介导的疾病,特征为中枢神经系统脱髓鞘,导致疲劳、疼痛、认知功能障碍和运动障碍。远程监督经颅直流电刺激(RS‑tDCS)是一种非侵入性、低成本、居家干预,可调节神经元兴奋性并增强神经网络功能,可能对MS患者有益。本荟萃分析旨在评估RS‑tDCS在MS中的疗效。
方法:在PubMed、Web of Science、Scopus和Cochrane Library中系统检索了评估RS‑tDCS在MS中的随机对照试验(RCT)。主要结局为信息处理速度。使用R软件(版本4.5.0)和随机效应模型进行统计分析,计算合并标准化均值差(SMD)和均值差(MD),并给出95%置信区间(CI)。使用Cochrane ROB‑2工具评估偏倚风险。
结果:共分析了五项RCT,主要包含在两组均使用RS‑tDCS的同时进行共干预的研究,其中一项专门针对患有大麻使用障碍的MS患者,样本总数为291人。活性RS‑tDCS未能显著改善信息处理速度(SMD = 0.20;95% CI: –0.06 to 0.45;P = 0.13,n = 4)。次要结局亦未见显著效应。
结论:来自五项异质RCT的证据,主要包含共干预,显示RS‑tDCS对MS认知或功能结果无明显益处(非常低至低置信度)。这凸显了显著的不确定性;需要更大规模的独立试验。
本中文摘要为机器辅助翻译,仅供参考;以英文摘要为准。 Machine-assisted Chinese translation of the English abstract; the English abstract is the version of record.
References
1. Khan G, Hashim MJ. Epidemiology of Multiple Sclerosis: Global, Regional, National and Sub-National-Level Estimates and Future Projections. J Epidemiol Glob Health. 2025;15(1):21. [PMID: 39928193, PMCID: PMC11811362, https://doi.org/10.1007/s44197-025-00353-6].
2. Haki M, Al-Biati HA, Al-Tameemi ZS, Ali IS, Al-Hussaniy HA. Review of multiple sclerosis: Epidemiology, etiology, pathophysiology, and treatment. Medicine (Baltimore). 2024;103(8):e37297. [PMID: 38394496, PMCID: PMC10883637, https://doi.org/10.1097/MD.0000000000037297].
3. Portaccio E, Magyari M, Havrdova EK, Ruet A, Brochet B, Scalfari A, Di Filippo M, Tur C, Montalban X, Amato MP. Multiple sclerosis: emerging epidemiological trends and redefining the clinical course. Lancet Reg Health Eur. 2024;44:100977. [PMID: 39444703, PMCID: PMC11496978, https://doi.org/10.1016/j.lanepe.2024.100977].
4. Sabatino JJ Jr, Cree BAC, Hauser SL. New Horizons for Multiple Sclerosis Therapy: 2025 and Beyond. Ann Neurol. 2025;98(2):317-28. [PMID: 40474602, PMCID: PMC12278195, https://doi.org/10.1002/ana.27270].
5. Cagol A, Schaedelin S, Pretzsch R, Kappos L, Sormani MP, Granziera C. The effect of disease-modifying therapies on brain volume loss and disability accumulation in multiple sclerosis: a systematic review and network meta-analysis. Lancet Reg Health Eur. 2025;59:101476. [PMID: 41080911, PMCID: PMC12509907, https://doi.org/10.1016/j.lanepe.2025.101476].
6. Wu X, Wang S, Xue T, Tan X, Li J, Chen Z, Wang Z. Disease-modifying therapy in progressive multiple sclerosis: a systematic review and network meta-analysis of randomized controlled trials. Front Neurol. 2024;15:1295770. [PMID: 38529035, PMCID: PMC10962394, https://doi.org/10.3389/fneur.2024.1295770].
7. Scavone C, Liguori V, Adungba OJ, Cesare DDG, Sullo MG, Andreone V, Sportiello L, Maniscalco GT, Capuano A. Disease-modifying therapies and hematological disorders: a systematic review of case reports and case series. Front Neurol. 2024;15:1386527. [PMID: 38957352, PMCID: PMC11217193, https://doi.org/10.3389/fneur.2024.1386527].
8. Tramacere I, Virgili G, Perduca V, Lucenteforte E, Benedetti MD, Capobussi M, Castellini G, Frau S, Gonzalez-Lorenzo M, Featherstone R, Filippini G. Adverse effects of immunotherapies for multiple sclerosis: a network meta-analysis. Cochrane Database Syst Rev. 2023;11(11):CD012186. [PMID: 38032059, PMCID: PMC10687854, https://doi.org/10.1002/14651858.CD012186.pub2].
9. Abboud H, Hill E, Siddiqui J, Serra A, Walter B. Neuromodulation in multiple sclerosis. Mult Scler. 2017;23(13):1663-76. [PMID: 29115915, https://doi.org/10.1177/1352458517736150].
10. Uygur-Kucukseymen E, Pacheco-Barrios K, Yuksel B, Gonzalez-Mego P, Soysal A, Fregni F. Non-invasive brain stimulation on clinical symptoms in multiple sclerosis patients: A systematic review and meta-analysis. Mult Scler Relat Disord. 2023;78:104927. [PMID: 37595371, https://doi.org/10.1016/j.msard.2023.104927].
11. Zhao H, Qiao L, Fan D, Zhang S, Turel O, Li Y, Li J, Xue G, Chen A, He Q. Modulation of Brain Activity with Noninvasive Transcranial Direct Current Stimulation (tDCS): Clinical Applications and Safety Concerns. Front Psychol. 2017;8:685. [PMID: 28539894, PMCID: PMC5423956, https://doi.org/10.3389/fpsyg.2017.00685].
12. Hsu WY, Cheng CH, Zanto TP, Gazzaley A, Bove RM. Effects of Transcranial Direct Current Stimulation on Cognition, Mood, Pain, and Fatigue in Multiple Sclerosis: A Systematic Review and Meta-Analysis. Front Neurol. 2021;12:626113. [PMID: 33763014, PMCID: PMC7982804, https://doi.org/10.3389/fneur.2021.626113].
13. Nombela-Cabrera R, Perez-Nombela S, Avendano-Coy J, Comino-Suarez N, Arroyo-Fernandez R, Gomez-Soriano J, Serrano-Munoz D. Effectiveness of transcranial direct current stimulation on balance and gait in patients with multiple sclerosis: systematic review and meta-analysis of randomized clinical trials. J Neuroeng Rehabil. 2023;20(1):142. [PMID: 37875941, PMCID: PMC10594930, https://doi.org/10.1186/s12984-023-01266-w].
14. Palm U, Kumpf U, Behler N, Wulf L, Kirsch B, Worsching J, Keeser D, Hasan A, Padberg F. Home Use, Remotely Supervised, and Remotely Controlled Transcranial Direct Current Stimulation: A Systematic Review of the Available Evidence. Neuromodulation. 2018;21(4):323-33. [PMID: 28913915, https://doi.org/10.1111/ner.12686].
15. Page MJ, McKenzie JE, Bossuyt PM, Boutron I, Hoffmann TC, Mulrow CD, Shamseer L, Tetzlaff JM, Akl EA, Brennan SE, Chou R, Glanville J, Grimshaw JM, Hrobjartsson A, Lalu MM, Li T, Loder EW, Mayo-Wilson E, McDonald S, McGuinness LA, Stewart LA, Thomas J, Tricco AC, Welch VA, Whiting P, Moher D. The PRISMA 2020 statement: an updated guideline for reporting systematic reviews. BMJ. 2021;372:n71. [PMID: 33782057, PMCID: PMC8005924, https://doi.org/10.1136/bmj.n71].
16. Cochrane Training. Cochrane Handbook for Systematic Reviews of Interventions. 2024. Available from: https://www.cochrane.org/authors/handbooks-and-manuals/handbook/current.
17. Clarivate Analytics. EndNote [software]. 2017.
18. Ouzzani M, Hammady H, Fedorowicz Z, Elmagarmid A. Rayyan-a web and mobile app for systematic reviews. Syst Rev. 2016;5(1):210. [PMID: 27919275, PMCID: PMC5139140, https://doi.org/10.1186/s13643-016-0384-4].
19. Sterne JAC, Savovic J, Page MJ, Elbers RG, Blencowe NS, Boutron I, Cates CJ, Cheng HY, Corbett MS, Eldridge SM, Emberson JR, Hernan MA, Hopewell S, Hrobjartsson A, Junqueira DR, Juni P, Kirkham JJ, Lasserson T, Li T, McAleenan A, Reeves BC, Shepperd S, Shrier I, Stewart LA, Tilling K, White IR, Whiting PF, Higgins JPT. RoB 2: a revised tool for assessing risk of bias in randomised trials. BMJ. 2019;366:l4898. [PMID: 31462531, https://doi.org/10.1136/bmj.l4898].
20. Schunemann HJ, Oxman AD, Brozek J, Glasziou P, Jaeschke R, Vist GE, Williams JW Jr, Kunz R, Craig J, Montori VM, Bossuyt P, Guyatt GH, GRADE Working Group. Grading quality of evidence and strength of recommendations for diagnostic tests and strategies. BMJ. 2008;336(7653):1106-10. [PMID: 18483053, PMCID: PMC2386626, https://doi.org/10.1136/bmj.39500.677199.AE].
21. McMaster University and Evidence Prime. GRADEpro GDT: GRADEpro Guideline Development Tool [Software]. 2025. Available from: https://www.gradepro.org.
22. Cochrane Handbook. Identifying and measuring heterogeneity. 2025. Chapter 9.5.2. Available from: https://handbook-5-1.cochrane.org/chapter_9/9_5_2_identifying_and_measuring_heterogeneity.htm.
23. Cochrane Handbook. Strategies for addressing heterogeneity. 2025. Chapter 9.5.3. Available from: https://handbook-5-1.cochrane.org/chapter_9/9_5_3_strategies_for_addressing_heterogeneity.htm.
24. Cochrane Handbook. Recommendations on testing for funnel plot asymmetry. 2025. Chapter 10.4.3.1. Available from: https://handbook-5-1.cochrane.org/chapter_10/10_4_3_1_recommendations_on_testing_for_funnel_plot_asymmetry.htm.
25. Charvet LE, Dobbs B, Shaw MT, Bikson M, Datta A, Krupp LB. Remotely supervised transcranial direct current stimulation for the treatment of fatigue in multiple sclerosis: Results from a randomized, sham-controlled trial. Mult Scler. 2018;24(13):1760-9. [PMID: 28937310, PMCID: PMC5975187, https://doi.org/10.1177/1352458517732842].
26. Charvet L, Goldberg JD, Li X, Best P, Lustberg M, Shaw M, Zhovtis L, Gutman J, Datta A, Bikson M, Pilloni G, Krupp L. Home-based transcranial direct current stimulation paired with cognitive training to reduce fatigue in multiple sclerosis. Sci Rep. 2025;15(1):4551. [PMID: 39915560, PMCID: PMC11802740, https://doi.org/10.1038/s41598-025-88255-2].
27. Pagliari C, Tella SD, Bonanno C, Cacciante L, Cioeta M, De Icco R, Jonsdottir J, Federico S, Franceschini M, Goffredo M, Rainoldi F, Rovaris M, Springhetti I, Calabro RS, Tassorelli C, Rossini PM, Baglio F, RIN TeleSM Group. Enhancing the effect of rehabilitation on multiple sclerosis: A randomized clinical trial investigating the impact of remotely-supervised transcranial direct current stimulation and virtual reality telerehabilitation training. Mult Scler Relat Disord. 2025;94:106256. [PMID: 39799756, https://doi.org/10.1016/j.msard.2024.106256].
28. Pilloni G, Lustberg M, Malik M, Feinberg C, Datta A, Bikson M, Gutman J, Krupp L, Charvet L. Hand functioning in progressive multiple sclerosis improves with tDCS added to daily exercises: A home-based randomized, double-blinded, sham-controlled clinical trial. Mult Scler. 2024;30(11-12):1490-502. [PMID: 39268655, https://doi.org/10.1177/13524585241275013].
29. Pilloni G, Pehel S, Ko T, Sammarco C, Charlson RE, Hanlon CA, Charvet L. Telehealth tDCS to reduce cannabis use: A pilot RCT in multiple sclerosis as a framework for generalized use. Drug Alcohol Depend. 2025;272:112706. [PMID: 40378662, PMCID: PMC12160002, https://doi.org/10.1016/j.drugalcdep.2025.112706].
30. Charvet LE, Kasschau M, Datta A, Knotkova H, Stevens MC, Alonzo A, Loo C, Krull KR, Bikson M. Remotely-supervised transcranial direct current stimulation (tDCS) for clinical trials: guidelines for technology and protocols. Front Syst Neurosci. 2015;9:26. [PMID: 25852494, PMCID: PMC4362220, https://doi.org/10.3389/fnsys.2015.00026].
31. Gough N, Brkan L, Subramaniam P, Chiuccariello L, De Petrillo A, Mulsant BH, Bowie CR, Rajji TK. Feasibility of remotely supervised transcranial direct current stimulation and cognitive remediation: A systematic review. PLoS One. 2020;15(2):e0223029. [PMID: 32092069, PMCID: PMC7039434, https://doi.org/10.1371/journal.pone.0223029].
32. Bjekic J, Zivanovic M, Stankovic M, Paunovic D, Konstantinovic U, Filipovic SR. The subjective experience of transcranial electrical stimulation: a within-subject comparison of tolerability and side effects between tDCS, tACS, and otDCS. Front Hum Neurosci. 2024;18:1468538. [PMID: 39507062, PMCID: PMC11537871, https://doi.org/10.3389/fnhum.2024.1468538].
33. Kasschau M, Reisner J, Sherman K, Bikson M, Datta A, Charvet LE. Transcranial Direct Current Stimulation Is Feasible for Remotely Supervised Home Delivery in Multiple Sclerosis. Neuromodulation. 2016;19(8):824-31. [PMID: 27089545, https://doi.org/10.1111/ner.12430].
34. Shaw M, Pilloni G, Charvet L. Delivering Transcranial Direct Current Stimulation Away From Clinic: Remotely Supervised tDCS. Mil Med. 2020;185(Suppl 1):319-25. [PMID: 32074357, https://doi.org/10.1093/milmed/usz348].
35. Cuypers K, Leenus DJ, Van Wijmeersch B, Thijs H, Levin O, Swinnen SP, Meesen RL. Anodal tDCS increases corticospinal output and projection strength in multiple sclerosis. Neurosci Lett. 2013;554:151-5. [PMID: 24036466, https://doi.org/10.1016/j.neulet.2013.09.004].
36. Tapsell LC, Pinto MD, Vallence AM, Whife C, Perez Armendariz ML, Senger S, Andringa-Bate J, Hince D, Murphy MC. What are the optimal transcranial direct current stimulation parameters and design elements to modulate corticospinal excitability? A systematic review and longitudinal meta-analysis. Neurol Res Pract. 2025;7(1):86. [PMID: 41219988, PMCID: PMC12606828, https://doi.org/10.1186/s42466-025-00449-1].
37. Kang J, Lee H, Yu S, Lee M, Kim HJ, Kwon R, Kim S, Fond G, Boyer L, Rahmati M, Koyanagi A, Smith L, Nehs CJ, Kim MS, Sanchez GFL, Dragioti E, Kim T, Yon DK. Effects and safety of transcranial direct current stimulation on multiple health outcomes: an umbrella review of randomized clinical trials. Mol Psychiatry. 2024;29(12):3789-801. [PMID: 38816583, https://doi.org/10.1038/s41380-024-02624-3].
38. Pilloni G, Vogel-Eyny A, Lustberg M, Best P, Malik M, Walton-Masters L, George A, Mirza I, Zhovtis L, Datta A, Bikson M, Krupp L, Charvet L. Tolerability and feasibility of at-home remotely supervised transcranial direct current stimulation (RS-tDCS): Single-center evidence from 6,779 sessions. Brain Stimul. 2022;15(3):707-16. [PMID: 35470019, https://doi.org/10.1016/j.brs.2022.04.014].
Data Availability Statement
The extracted dataset and R analysis code are provided as Supplementary Materials.
License
Copyright (c) 2026 Omar Khaled Abdelsalam, Mousa Almasalma, Ali Nagy Shelbaya, Ahmed Raja Albishti, Mohamed H. Khalil, Hamza Khelifa, Ahmed Abdelsalam, Asmaa Zakria Alnajjar

This work is licensed under a Creative Commons Attribution 4.0 International License.
Copyright and Licensing
All articles published in ASIDE Internal Medicine are open access and freely available online immediately upon publication, without embargo.
This journal applies the terms of the Creative Commons Attribution 4.0 International License (CC BY 4.0). Under this license, anyone may copy, redistribute, remix, transform, and build upon the material for any purpose, even commercially, provided that proper credit is given to the original author(s), a link to the license is provided, and any changes made are indicated.
-
License link: https://creativecommons.org/licenses/by/4.0/
-
Machine-readable license metadata is embedded in each article and its DOI record.
Copyright Holder
Copyright in all articles remains with the author(s). ASIDE Internal Medicine is published and owned by the American Society for Inclusion, Diversity, and Equity in Healthcare (ASIDE). By submitting a manuscript, authors agree to grant the publisher a non-exclusive license to publish, distribute, and archive the work under the terms of the CC BY 4.0 license.
Third-party Material
Any material (e.g., images, figures, or tables) not covered by CC BY 4.0 will be clearly indicated in the article. Users must obtain permission directly from the copyright holder for reuse of such third-party material.
Author Rights and Self-Archiving
Authors are permitted to deposit all versions of their work (preprint, author’s accepted manuscript, and version of record) in institutional or subject repositories of their choice immediately upon publication, without embargo, provided that the DOI and license information are included.

Additional Files
Published
How to Cite
Article history
- Received
- 4 Mar 2026
- Received in revised form
- 4 Apr 2026
- Accepted
- 13 Apr 2026
- Published
- 25 Apr 2026
