
Efficacy and Safety of Isotretinoin Plus Desloratadine versus Isotretinoin Alone for Acne Vulgaris: Systematic Review and Meta-analysis
DOI:
https://doi.org/10.71079/ASIDE.IM.020726257Abstract
Introduction: Acne vulgaris is a common inflammatory skin disorder affecting the sebaceous glands–rich areas, including the face, chest, and back. It typically arises during adolescence but can persist or appear in adulthood. Recent findings suggest that histamine, via H1 receptors on sebocytes, further contributes to inflammation and sebum secretion. Desloratadine, an H1 receptor antagonist, has anti-inflammatory effects and reduces sebum squalene levels, supporting potential as an adjunctive acne therapy. We assessed whether adding desloratadine to isotretinoin improves outcomes compared to isotretinoin monotherapy.
Methods: Following PRISMA guidelines, we searched PubMed, Web of Science, and Scopus targeting randomized controlled trials (RCTs) comparing isotretinoin plus desloratadine versus isotretinoin alone. Eligible studies reported the Global Acne Grading System (GAGS) score, inflammatory lesion count, or non-inflammatory lesion count. Results were pooled and expressed as differences (MD) with 95% confidence intervals (CI).
Results: Six RCTs, including 424 patients, met the inclusion criteria. Combination therapy demonstrated greater improvement in GAGS score (pooled MD −1.81, 95% CI [−2.52; −1.1], P < 0.00001). However, no significant differences were observed in inflammatory lesions (pooled MD 0.26, 95% CI [−1.01; 1.54], P = 0.68) or non-inflammatory lesions (pooled MD 0.30, 95% CI [−2.24; 2.84], P = 0.82). The addition of desloratadine to isotretinoin improved treatment efficacy and showed trends toward fewer flares and dry lips, although these differences did not reach statistical significance.
Conclusion: Desloratadine appears to enhance the efficacy and tolerability of isotretinoin, supporting its position as a promising adjunctive therapy for acne management.
Keywords:
Acne vulgaris, Retinoids, Isotretinoin, Desloratadine, AntihistaminesFull Text
Introduction
Acne vulgaris is a common inflammatory skin condition that typically appears on areas rich in sebaceous glands, such as the face, chest, and back. It presents with comedones, inflammatory papules, and pustules, and while it is most prevalent in adolescents, it can affect individuals of all ages [1].
The development of acne involves a complex interplay of multiple pathogenic mechanisms, including increased sebum production, follicular hyperkeratinization, colonization by Cutibacterium acnes, and an associated inflammatory immune response. Combined, these factors promote the formation of both non-inflammatory and inflammatory lesions, thereby complicating treatment. Currently, the range of therapies available includes topical solutions and oral medications. The primary treatments consist of topical retinoids, benzoyl peroxide, and antibiotics. In cases that are resistant or more severe, oral antibiotics, hormone-regulating treatments, or isotretinoin may be utilized [2].
In addition to these inflammatory mechanisms, the role of histamines and H1 receptor activation on sebocytes has been implicated in acne pathogenesis [3]. Recent studies have shown that H1-receptor antagonists may have a therapeutic role in acne treatment by reducing squalene levels, a key biomarker of sebum production [4]. To address this, researchers have introduced various dosing regimens and are developing new strategies to minimize sebum production. Furthermore, histamine may contribute to acne pathogenesis by acting as an inflammatory mediator during the immune response associated with inflammatory acne [5].
Currently, isotretinoin is the sole medication that effectively addresses all the underlying causes of acne. It is particularly advantageous in cases of acne that have not responded satisfactorily to alternative treatments. However, isotretinoin may result in adverse effects, including dry skin, chapped lips, erythema, and rashes. H1-antihistamines have historically been utilized to alleviate pruritic (itching) and allergic conditions. Moreover, histamine has been implicated as an inflammatory mediator in the pathogenesis of acne vulgaris through activation of histamine H1 receptors on human sebaceous glands, thereby inducing histamine and leukotriene release [6]. This is in conjunction with pH changes within the acne follicle induced by Propionibacterium acnes, which provide a favorable microenvironment for histamine production, thereby causing itching in patients with acne [6]. This suggests that antagonism of H1 receptors to reduce sebum production and alleviate pruritic symptoms provides a rationale for utilizing antihistamines in the treatment of acne.
Oral desloratadine (DESL) is a selective H1-receptor antagonist with anti-inflammatory properties. It inhibits interleukins (IL-4, IL-6, and IL-13), histamine, prostaglandins, and leukotrienes, which are involved in the pathogenesis of acne vulgaris. Additionally, DESL reduces sebum squalene levels, suggesting its potential for treating acne vulgaris (AV) [7]. Hence, this systematic review and meta-analysis aims to synthesize evidence from randomized controlled trials to determine whether adding desloratadine to isotretinoin therapy improves treatment efficacy and tolerability in patients with acne vulgaris, and whether the benefits justify and rationalize co-prescription in clinical practice.
Histamine signalling contributes directly to acne pathogenesis by binding to human sebocytes. The pathophysiology of this is that the functional H1 receptors expressed by Sebocytes promote pro-inflammatory signaling and stimulate lipid synthesis upon activation [8]. Primary evidence emphasizes that H1-antihistamines exert measurable sebostatic activity and that H1 blockade significantly reduced squalene, one of the lipids that contributes significantly to driving acne pathology, by around 60-70% in ex vivo sebocyte assays [9]. This supports the clinical observation that antihistamines may modulate both inflammation and sebum production, key components of acne pathogenesis. A recent systematic review, composed of multiple RCTs, also emphasizes that combination therapy with isotretinoin and desloratadine showed significantly greater reductions in Global Acne Grading Scale (GAGS) scores, and reduced inflammatory lesions, pruritus, acne flare-ups, and cheilitis compared with isotretinoin [10].
Desloratadine is the principal active metabolite of loratadine and is a selective peripheral H1-receptor antagonist administered once daily. In vitro studies demonstrate that desloratadine has a higher binding affinity for H1 receptors compared with loratadine, resulting in more sustained receptor occupancy [11]. Beyond classical antihistaminic activity, desloratadine exhibits inverse agonism at H1-receptor–linked inflammatory signalling pathways, including inhibition of both basal and histamine-stimulated NF-B activity, supporting a direct anti-inflammatory mechanism [9]. Its relevance to acne biology is further supported by the expression of H1 receptors on human sebocytes and experimental evidence showing that H1 antagonism significantly reduces squalene production, a key lipid mediator implicated in acne pathogenesis [12]. However, we acknowledge that direct head-to-head clinical evidence demonstrating the superiority of desloratadine over other second-generation antihistamines is limited. Accordingly, this review focuses on desloratadine because it is the adjunct evaluated in the included randomized controlled trials, rather than based on proven class superiority.
Methods
This study was designed in accordance with the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) guidelines [13]. In addition, the protocol was registered with PROSPERO (www.crdyork.ac.uk/PROSPERO/view/CRD420251041965 ) on 28 April 2025.
Criteria for Considering Studies for this Review
We used the following inclusion criteria:
We excluded articles that were case reports or case series, theses, conference abstracts, non-RCT studies, duplicate publications, or animal studies.
| Study ID | Study design | Location | Year | Population | Intervention | Comparator | Follow up duration | Outcome measures |
|---|---|---|---|---|---|---|---|---|
| El Ghareeb 2025 [14] | RCT | Egypt | 2025 | 64 patients with acne vulgaris | combined isotretinoin and desloratadine | isotretinoin | one month | GAGS score, cholesterol, triglyceride, SGOT, and SGPT levels |
| Asilian 2024 [15] | RCT | Iran | 2024 | 60 patients with acne vulgaris | combined isotretinoin and desloratadine | isotretinoin | NA | GAGS score, the number of inflammatory and non-inflammatory lesions and Laboratory parameters |
| Mansoor 2024 [16] | RCT | Pakistan | 2024 | 108 patients with acne | combined isotretinoin and desloratadine | isotretinoin | NA | GAGS score |
| Hazarika 2024 [7] | RCT | India | 2024 | 90 patients with acne | combined isotretinoin and desloratadine | isotretinoin | 3 months | Acne lesion count, GAGS score and patient satisfaction with treatment (assessed by using 4-point Likert scale as excellent, good, average, poor). |
| Van 2019 [17] | RCT | Vietnam | 2019 | 62 patients with acne | combined isotretinoin and desloratadine | isotretinoin | 4 months | GAGS score, number of inflammatory lesions and illness severity score |
| Lee 2014 [6] | RCT | Korea | 2014 | 40 patients with acne | combined isotretinoin and desloratadine | isotretinoin | 3 months | Acne lesion counts, Patient satisfaction |
RCT, randomized controlled trial; GAGS, Global Acne Grading System; NA, not available; SGOT, serum glutamic oxaloacetic transaminase; SGPT, serum glutamic pyruvic transaminase.
Search Strategy
We systematically searched the medical electronic databases PubMed, Web of Science, and Scopus from inception through May 2025 for relevant studies using the following search strategy: (acne OR acneiform) AND (isotretinoin OR "13-cis.-retinoic acid") OR (desloratadine OR clarinex). Two researchers performed the searches independently and in parallel.
Screening and Selection of Studies
The predefined selection criteria were applied in a two-step screening process. First, titles and abstracts were screened for relevance. Second, full-text articles of all potentially eligible studies were retrieved and assessed for inclusion in the meta-analysis. Two reviewers independently conducted the literature screening, and a third reviewer resolved any discrepancies.
Assessment of Risk of Bias in Included Studies
We used the revised Cochrane risk. -of-bias tool (RoB2) for RCTs to evaluate the risk of bias in the included clinical trials [18]. This assessment included the randomization process, concealment of the allocation sequence, deviations from the intended interventions, use of appropriate analyses to estimate the effect of the assigned intervention, outcome measurement, selection of the reported results, and overall risk of bias. The methodological quality of the studies was categorized as either low risk, some concerns, or high risk of bias. Two independent co-authors assessed the risk of bias, and disagreements were resolved through discussion with a third author.
Data extraction
Two reviewers independently extracted data into a standardized online data extraction sheet for all included studies, and a third reviewer resolved any conflicts. The extracted data were organized into four categories: Summary of included studies; baseline characteristics of the included studies’ population; risk of bias (across the five assessed domains); and study outcomes (Change in mean GAGS score, noninflammatory acne lesions, inflammatory acne lesions, and total acne lesions).
Outcomes
The primary outcome of interest was the change in Global Acne Grading System (GAGS) score from baseline to the primary timepoint (week 12). For studies that reported multiple time points, each was analyzed separately, and a pooled analysis was conducted at the end of follow-up.
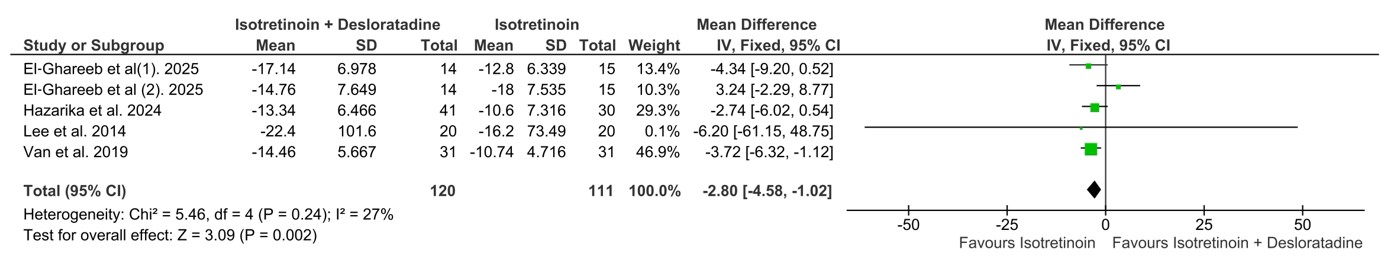
Secondary outcomes included changes in the number of inflammatory and non-inflammatory lesions from baseline to week 8 of treatment, liver function tests, lipids, and adverse events (acne flare, dry lips, pruritus, cheilitis, and xerosis).
Time windows and selection rules
To prevent selective inclusion, outcomes were extracted using the following hierarchy, prespecified before analysis:
All continuous outcomes were extracted as change from baseline, where available. When change scores were not reported, final values measured on the same scale and at comparable time points were used, in accordance with Cochrane guidance. No imputation of missing outcome data was required, and standard deviations were taken directly from trial reports or derived from reported variance measures where necessary. Because outcomes were measured on identical scales across studies, results were pooled using mean differences rather than standardized mean differences.
To ensure consistency, we applied a prespecified rule for safety outcomes: any adverse effect reported in ≥2 trials (clinical events or laboratory parameters) was meta-analyzed; outcomes reported in only a single trial were summarized descriptively.
Statistical Analysis
We used an inverse-variance fixed-effect model for all primary and secondary data analyses, as the included trials had I values between 0% and 27%, indicating minimal statistical heterogeneity (an I value between 0% and 40% may not be important according to Chapter 10, 10.2, of the Cochrane Handbook). A fixed-effects approach was used because was estimated to be zero across all outcomes, indicating no detectable heterogeneity between studies. Heterogeneity was assessed using the chi-square () test, I, and forest plots. When a small amount of heterogeneity was present, it was resolved through the sensitivity analyses we had already specified. As expected, fixed-effect and random-effect estimates were identical when I, confirming that the conclusions were independent of our model choice.
All statistical analyses were performed with the Review Manager statistical software package (Version 5.4.1). Continuous outcomes were presented as mean differences (MDs) with 95% confidence intervals (CIs), whereas dichotomous outcomes were presented as risk ratios (RRs) with 95% CIs.
Fixed-effect and random-effects models produced identical pooled estimates when assessing heterogeneity. Where small amounts of heterogeneity were observed, sensitivity analyses resolved these discrepancies without altering the direction or significance of the results. Therefore, findings were robust to model choice and study inclusion.
Heterogeneity was evaluated by visual inspection of forest plots and using two statistical tests: the chi-square () test and the I statistic. The test was used to assess statistical significance (), and the I statistic quantified the degree of heterogeneity. We interpreted I according to the Cochrane Handbook guidelines: 0–40% (not important), 30–60% (moderate heterogeneity), 50–90% (substantial heterogeneity), and 75–100% (considerable heterogeneity). We considered heterogeneity significant if the P-value from the test was .
Where outcomes were reported at multiple follow-up time points, each point was analyzed separately. In addition, a pooled end-of-.A follow-up analysis was conducted. Timepoint-stratified analyses were considered exploratory and were used to assess temporal patterns of treatment response rather than to test prespecified clinical effect modifiers.
Publication Bias
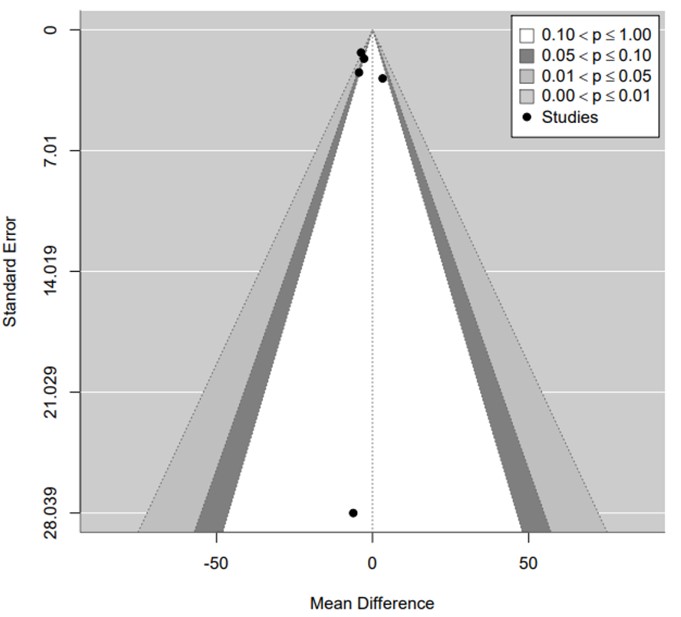
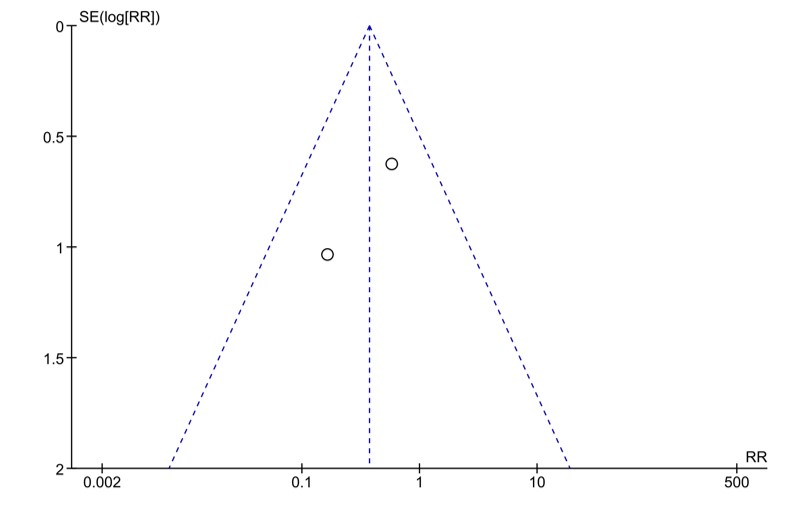
Small-study effects and potential publication bias were assessed using contour-.enhanced funnel plots, with contours corresponding to conventional levels of statistical significance Figure 4. Because tests for publication bias are unreliable with fewer than 10 studies [19,20]. We did not perform Egger’s test for funnel plot asymmetry in this meta-analysis.
Results
Search Results and Study Selection
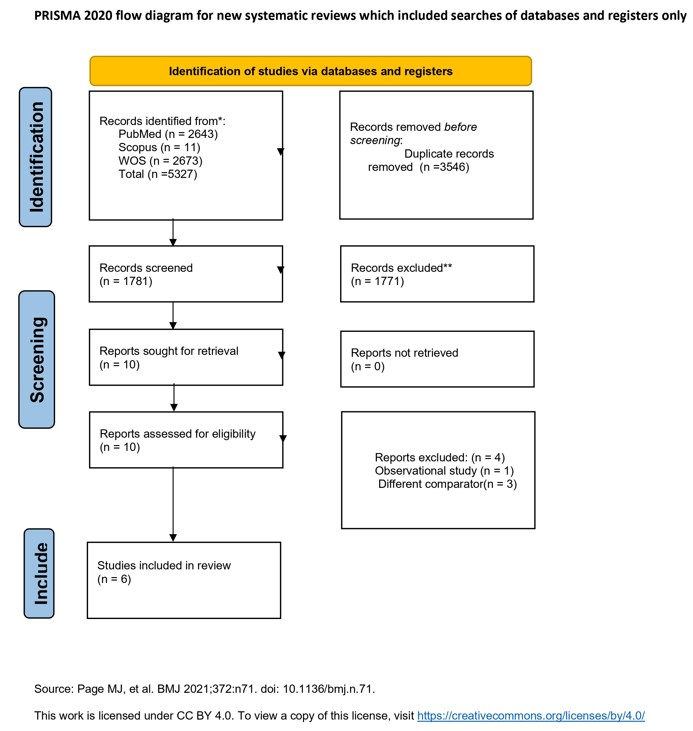
We identified 5,327 records from PubMed, Scopus, and Web of Science. After removing 3,546 duplicate entries, 10 unique articles were assessed for eligibility based on their titles and abstracts. Four of these were excluded because they did not meet the inclusion criteria. Six full-text papers were retrieved for detailed evaluation, and all six met the inclusion criteria Figure 1.
Characteristics of Included Studies
The six randomized controlled trials [15,14,7,6,16,17] The study included 424 patients and had follow-up durations of up to 4 months. Clinical and outcome data for these patients are summarized in Table 1.
| Author (Year) | Group | Age | Sex (male no (%)) | Duration (years) (mean ± SD) | GAGS score baseline (mean ± SD) | Weight (kg) (mean ± SD) |
|---|---|---|---|---|---|---|
| El Ghareeb 2025 [14] | Intervention 1 | 17.44 ± 2.07 | 8 (50%) | 3.34 ± 1.87 | 31.21 ± 7.04 | NA |
| Asilian 2024 [15] | Intervention 2 | 18.94 ± 1.73 | 9 (56.3%) | 3.25 ± 1.84 | 27.79 ± 6.94 | NA |
| Mansoor 2024 [16] | Control | 18.25 ± 3.26 | 5 (31.3%) | 4.23 ± 2.49 | 29.07 ± 5.68 | NA |
| Hazarika 2024 [7] | Control | 18.69 ± 2.94 | 9 (56.3%) | 4.38 ± 2.53 | 32.67 ± 7.3 | NA |
| Van 2019 [17] | Intervention | 22.64 ± 4.65 | 4 (14.2%) | 4.02 ± 2.49 | 25.04 ± 5.39 | NA |
| Control | 21.93 ± 4.03 | 5 (17.8%) | 4.23 ± 3.52 | 24.93 ± 6.19 | NA | |
| El Ghareeb 2025 [14] | Intervention | 15–25 years 38 (70.4%) | 13 (24.1%) | NA | 23.48 ± 3.07 | NA |
| Asilian 2024 [15] | Control | 15–25 years 34 (63.0%) | 16 (29.6%) | NA | 23.76 ± 3.44 | NA |
| Mansoor 2024 [16] | Intervention | 21.34 ± 3.79 | 20 (44.44%) | NA | 24.56 ± 5.63 | 53 (49–58) |
| Hazarika 2024 [7] | Control | 19.17 ± 3.36 | 28 (62.22%) | NA | 22.17 ± 6.42 | 54.5 (47.25–60) |
| Van 2019 [17] | Intervention | 21.90 ± 4.1 | 11 (35%) | NA | 22.90 ± 3.11 | 52.32 ± 8.56 |
| Control | 22.06 ± 4.20 | 12 (39%) | NA | 22.77 ± 3.03 | 57.61 ± 9.90 | |
| El Ghareeb 2025 [14] | Intervention | 21 ± 3.7 | 8 (40%) | 4.8 ± 2.76 | 28.2 ± 6.48 | NA |
| Control | 21.9 ± 2.1 | 8 (40%) | 4.8 ± 2.76 | 27.2 ± 6.09 | NA |
GAGS, Global Acne Grading System; SD, standard deviation; NA, not available; n, number; %, percentage; kg, kilograms.
| Outcome | No. of participants (studies) | Risk of bias | Inconsistency | Indirectness | Imprecision | Publication bias | Overall certainty of evidence (GRADE) |
|---|---|---|---|---|---|---|---|
| GAGS score at 12 weeks (Primary outcome) | 120 participants (5 RCTs) | Serious | Not serious | Not serious | Not serious | Not serious | Moderate |
| Change in inflammatory lesion count (Secondary outcome) | 332 participants (4 RCTs) | Serious | Not serious | Not serious | Serious | Suspected | Low |
| Change in non-inflammatory lesion count (Secondary outcome) | 290 participants (3 RCTs) | Serious | Not serious | Not serious | Serious | Suspected | Low |
| Acne flare (Secondary outcome) | 268 participants (3 RCTs) | Serious | Not serious | Not serious | Serious | Suspected | Low |
| Dry lips / cheilitis (Secondary outcome) | 348 participants (4 RCTs) | Serious | Not serious | Not serious | Serious | Suspected | Low |
| Xerosis (Secondary outcome) | 302 participants (3 RCTs) | Serious | Not serious | Not serious | Serious | Suspected | Low |
| Pruritus (Secondary outcome) | 284 participants (3 RCTs) | Serious | Not serious | Not serious | Serious | Suspected | Low |
| Liver function tests (ALT, AST) (Secondary outcome) | 3–4 RCTs | Serious | Serious | Not serious | Serious | Suspected | Low |
| Lipid parameters (total cholesterol, triglycerides) (Secondary outcome) | 3–4 RCTs | Serious | Serious | Not serious | Serious | Suspected | Low |
GRADE, Grading of Recommendations Assessment, Development and Evaluation; GAGS, Global Acne Grading System; RCT, randomized controlled trial; ALT, alanine aminotransferase; AST, aspartate aminotransferase.
Most studies included participants aged 15-25 years, reflecting the typical age at acne onset. The mean age of participants in the intervention groups ranged from 17.4 to 22.6 years, while in the control groups, it ranged from 18.2 to 22.1 years.
The percentage of male participants varied across studies. In the intervention groups, males accounted for 14.2%- 50%, whereas in the control groups, the range was 17.8%- 62.2%. Overall, both groups exhibited a mixed gender distribution, with some studies showing a slightly higher female representation in the control group Table 2.
Risk of Bias Assessment and Quality of Evidence
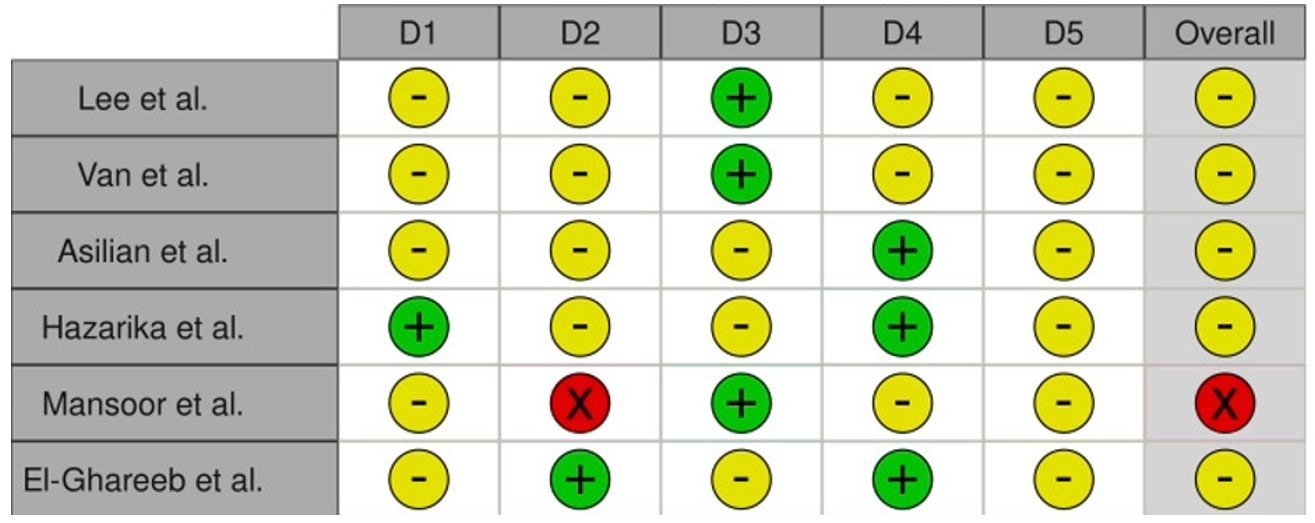
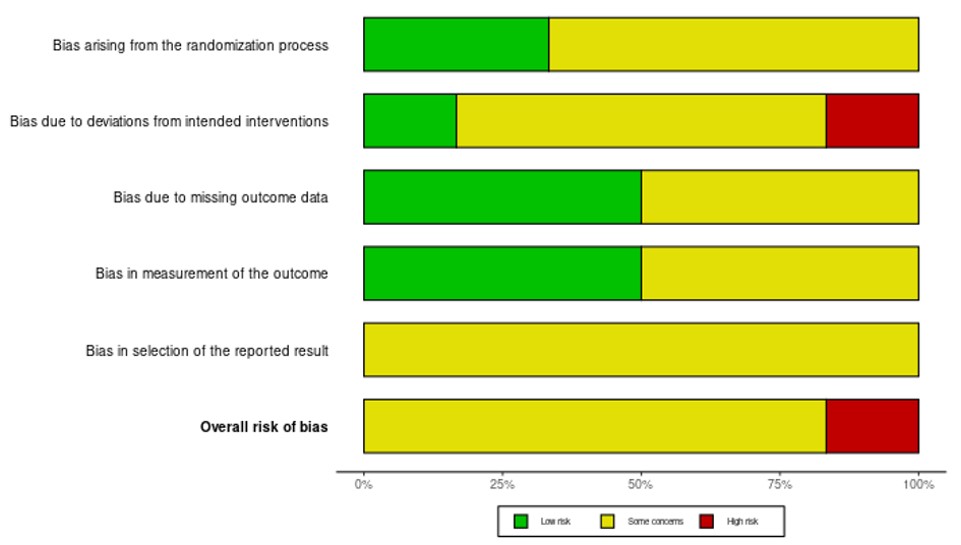
According to Cochrane’s RoB 2 tool, five studies were judged to have “some concerns” regarding the overall risk of bias, and one study was rated “high” risk of bias due to deviations from the intended interventions (Figure 2, Figure 3). Accordingly, the certainty of evidence for the primary outcome (GAGS score) was downgraded by one level for risk of bias.
No downgrading was applied for inconsistency, as heterogeneity across analyses was low (I² = 0–27%), confidence intervals overlapped, no effect reversals were observed, and no subgroup differences were detected (p = 0.41). Evidence was also not downgraded for indirectness, as all included studies directly matched the PICO framework with respect to population (moderate–severe acne), intervention (isotretinoin plus desloratadine), comparator (isotretinoin alone), and outcome. Imprecision was not downgraded for the primary outcome because confidence intervals were narrow, did not cross the line of no effect, and consistently favored the intervention despite sample sizes below the optimal information threshold. Publication bias was not downgraded, as outcomes were consistently reported, several trials were prospectively registered, and at least one study reported null findings.
For secondary outcomes, the certainty of evidence was downgraded by one level for risk of bias, as most trials had some concerns, and one was at high risk. Imprecision was reduced by wide confidence intervals that frequently crossed the no-effect line and by failure to meet the optimal information size. Publication bias was also downgraded owing to small sample sizes, few studies per outcome, and the inability to formally assess funnel plot asymmetry. Additionally, inconsistency was downgraded for laboratory outcomes only, as substantial heterogeneity was observed that resolved only after exclusion of a single influential study Table 3.
Visual inspection of the contour-enhanced funnel plot for the primary outcome showed only mild asymmetry Figure 4.
Global Acne Grading System (GAGS)
All six trials reported acne severity using the Global Acne Grading System. GAGS outcomes were analyzed at multiple follow-up time points (2, 4, 8, 12, and 16 weeks) and at the end of follow-up. Effect estimates were directionally consistent over time, with clearer separation between treatment groups observed at later time points. However, subgroup analysis showed no evidence of effect modification by follow-up duration (p = 0.41). These timepoint-stratified analyses were exploratory and should not be interpreted as evidence of differential treatment efficacy across subgroups.
Baseline to week 2
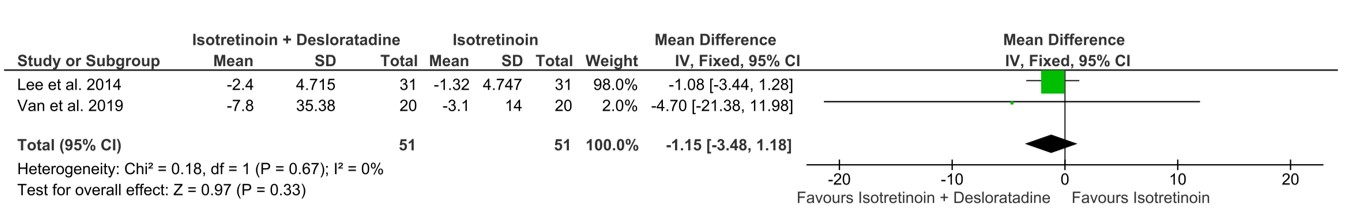
The pooled mean difference (MD) between combination therapy and isotretinoin monotherapy favored the combination group; however, this difference was not statistically significant (MD = –1.15, 95% CI –3.48 to 1.18, p = 0.33). Studies were homogeneous (Chi-square p = 0.67; I² = 0%) Figure 10.
Baseline to week 4
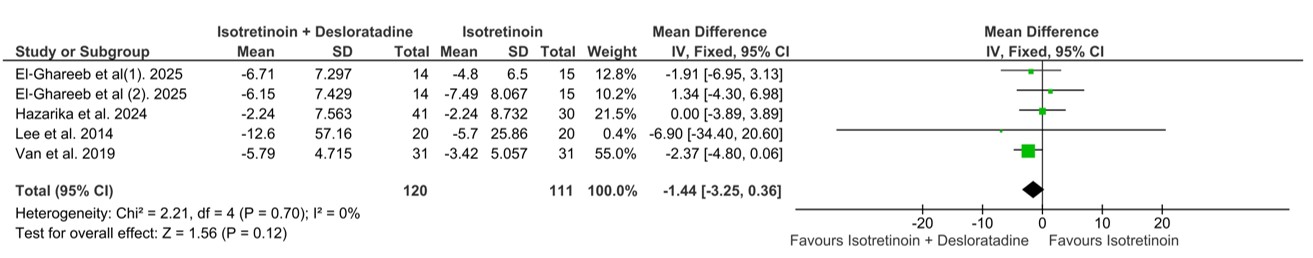
Although the point estimate favored combination therapy, the difference was not statistically significant (MD = –1.44, 95% CI –3.25 to 0.36, p = 0.12). Pooled studies were homogeneous (Chi-square p = 0.70; I² = 0%) Figure 9.
Baseline to week 8
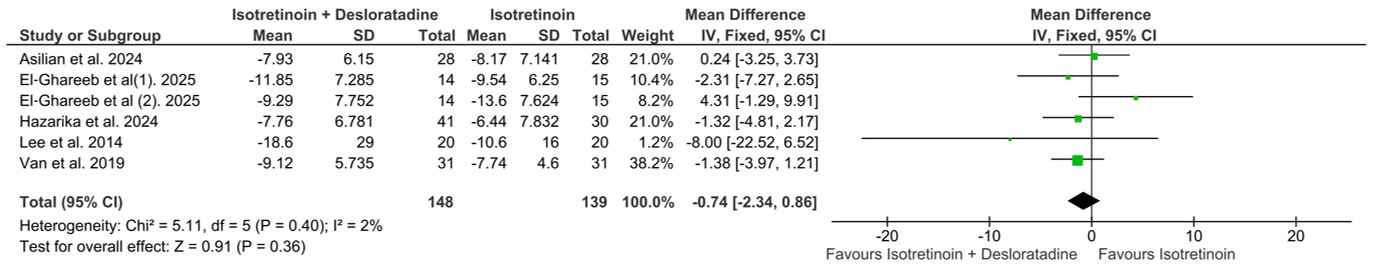
No difference was observed between treatment groups (MD = –0.74, 95% CI –2.34 to 0.86, p = 0.36). Studies were homogeneous (Chi-square p = 0.40; I² = 2%) Figure 8.
Baseline to week 12 (Primary endpoint)
The pooled mean difference favored combination therapy and was statistically significant (MD = –2.80, 95% CI –4.58 to –1.02, p = 0.002). Moderate heterogeneity was observed (Chi-square p = 0.24; I² = 27%) Figure 5.
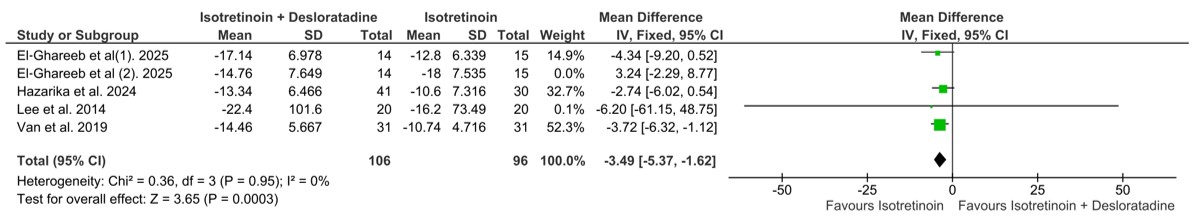
Sensitivity analyses were performed to explore heterogeneity. Exclusion of El-Gareeb et al. resolved heterogeneity (I² = 0%; p = 0.95), while the treatment effect remained statistically significant in favor of combination therapy (MD = –3.49, 95% CI –5.37 to –1.62, p = 0.003) Figure 6.
Baseline to week 16
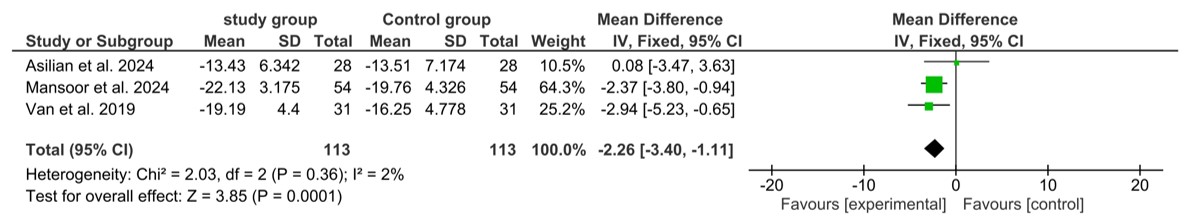
Combination therapy continued to demonstrate a statistically significant benefit compared to isotretinoin monotherapy (MD = –2.26, 95% CI –3.40 to –1.11, p = 0.00001). Pooled studies were homogeneous (Chi-square p = 0.36; I² = 2%) Figure 7.
Baseline to end of follow-up
At final follow-up, the pooled analysis favoured combination therapy with a statistically significant difference (MD = –1.81, 95% CI –2.52 to –1.10, p < 0.0001). Studies were homogeneous (Chi-square p = 0.52; I² = 0%) Figure 3.
MCID interpretation
To assess the clinical relevance of the observed change in Global Acne Grading System (GAGS) scores, we estimated the Minimal Clinically Important Difference (MCID) using the distribution-based 0.5 standard deviation (SD) method. This is a commonly accepted method in the absence of a validated patient.-derived (anchor-based) values [21]. Across the included studies, baseline GAGS scores ranged from 22.17 to 32.67, with corresponding SDs ranging from 3.03 to 7.3. Applying the 0.5 SD method, the estimated MCID ranged from approximately 1.52 to 3.65, with a mean MCID of 2.65 across studies. The pooled mean difference in GAGS score between combination therapy and isotretinoin monotherapy was –1.81 (95% CI: –2.52 to –1.10, P < 0.0.0001). Although statistically significant, this effect size falls slightly below the average estimated MCID, indicating that the clinical importance of the observed improvement remains uncertain. While some patients may experience meaningful benefit, the average effect did not exceed the conventional threshold for clinical relevance.
Lesion Counts
In addition to GAGS scores, treatment efficacy was further evaluated by changes in counts of inflammatory and non-inflammatory lesions.
Inflammatory lesions
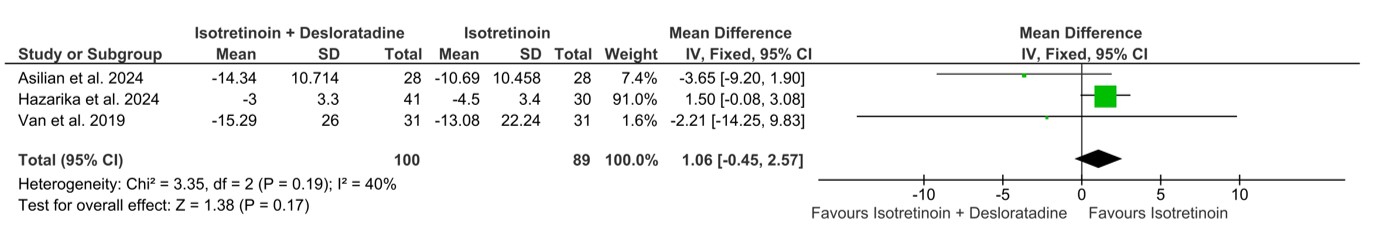
There was no significant difference between combination therapy and isotretinoin monotherapy (pooled MD = 1.06, 95% CI [–2.57 to 0.45], P = 0.17), with a non-significant trend towards higher lesion counts in the combination group. Moderate heterogeneity was observed ( P = 0.19; I = 40%) Figure 11.
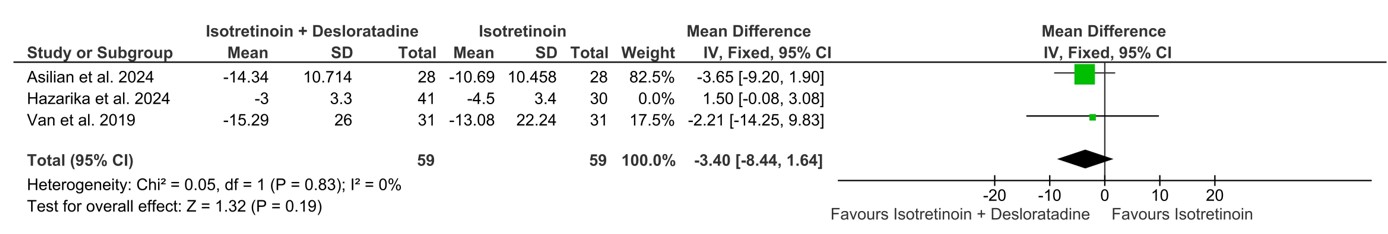
Sensitivity analysis identified Hazarika et al. as the main source of heterogeneity. After exclusion, heterogeneity was resolved ( P = 0.83; I = 0%). The pooled estimate showed a non-significant trend favoring combination therapy, with fewer inflammatory lesions (MD = –3.40, 95% CI [–8.44 to 1.64], P = 0.19) Figure 12.
Non-inflammatory lesions
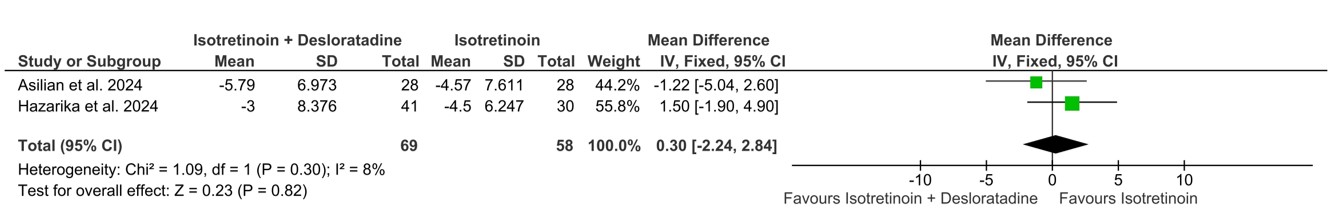
No significant difference was observed between groups (pooled MD = 0.30, 95% CI [–2.24 to 2.84], P = 0.82). Studies were homogeneous ( P = 0.30; I = 8%) Figure 13.
Safety outcomes
Across the included studies, a range of adverse effects were reported, including laboratory abnormalities (liver enzymes and lipid profiles) and clinical events such as acne flares, dry lips, cheilitis, xerosis, and pruritus. Accordingly, pooled analyses were performed for ALT, AST, total cholesterol, triglycerides, acne flare, dry lips, cheilitis, xerosis, and pruritus.
Laboratory safety outcomes are presented first, followed by clinical adverse events. Discontinuations due to adverse effects were rare, and no clinically meaningful differences in overall safety were observed between combination therapy and isotretinoin monotherapy.
Liver function tests
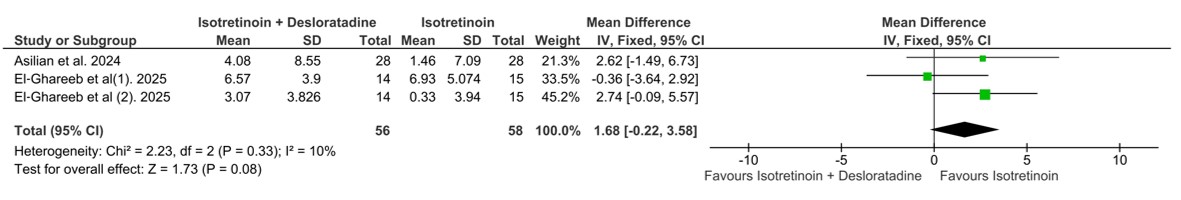
Alanine aminotransferase (ALT): No significant difference was observed between groups (pooled MD = 1.68, 95% CI [–0.22 to 3.58], P = 0.08). Studies were homogeneous ( P = 0.33; I = 10%) Figure 14.
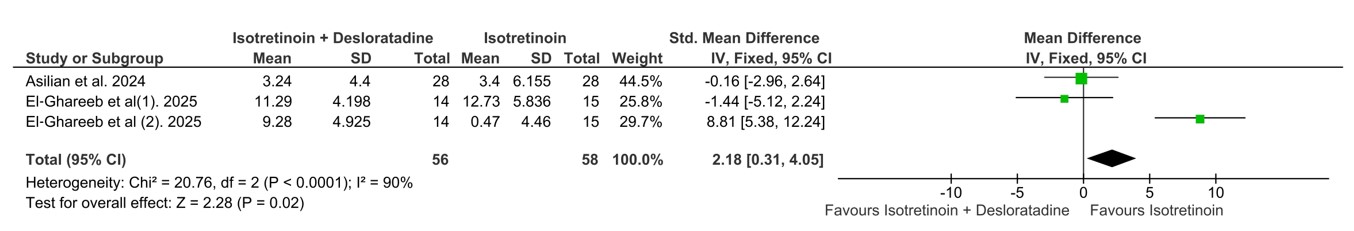
Aspartate aminotransferase (AST): Combination therapy initially favoured lower AST levels (pooled MD = 2.18, 95% CI [0.31 to 4.05], P = 0.02); however, substantial heterogeneity was present ( P < 0.001; I = 90%) Figure 15.
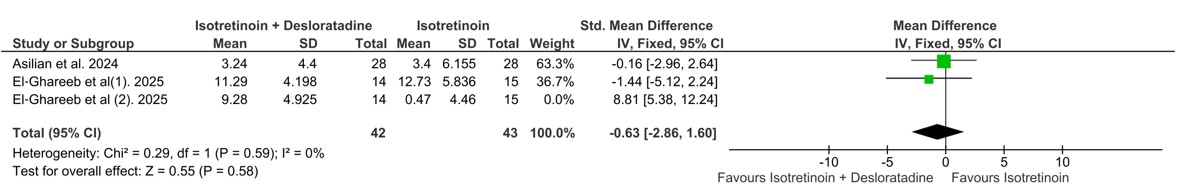
Sensitivity analysis identified El-Gareeb et al. as the primary contributor to heterogeneity. After exclusion, heterogeneity resolved ( P = 0.59; I = 0%), and the treatment effect was no longer significant (MD = –0.63, 95% CI [–2.86 to 1.60], P = 0.58) Figure 16.
Lipid profile
Total cholesterol
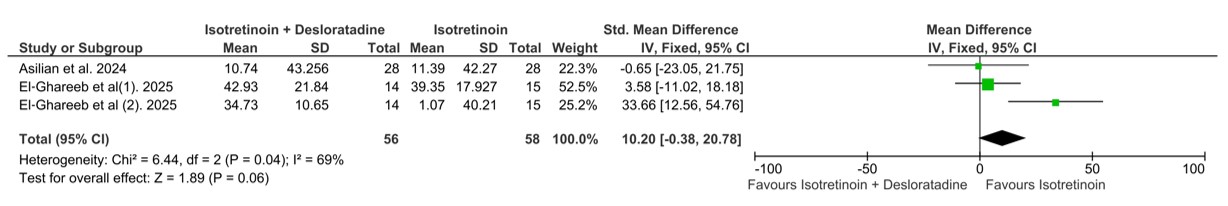
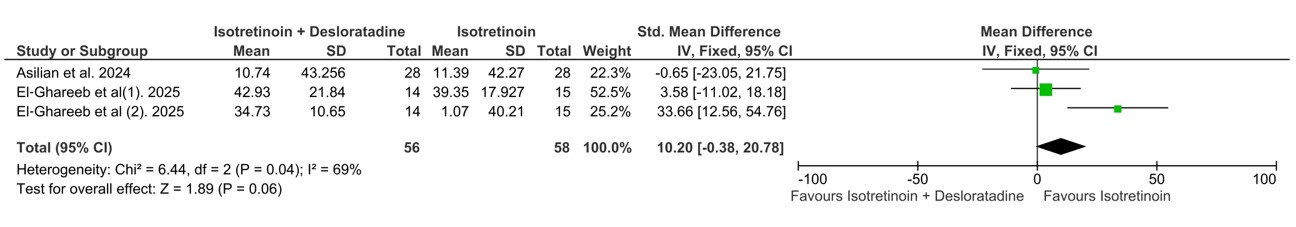
No significant difference was observed (pooled MD = 10.20, 95% CI [–0.38 to 20.78], P = 0.06). Substantial heterogeneity was present ( P = 0.04; I = 69%) Figure 17.
Exclusion of El-Gareeb et al. resolved heterogeneity ( P = 0.76; I = 0%), with no significant difference between groups (MD = 2.32, 95% CI [–9.91 to 14.55], P = 0.71) Figure 18.
Triglycerides
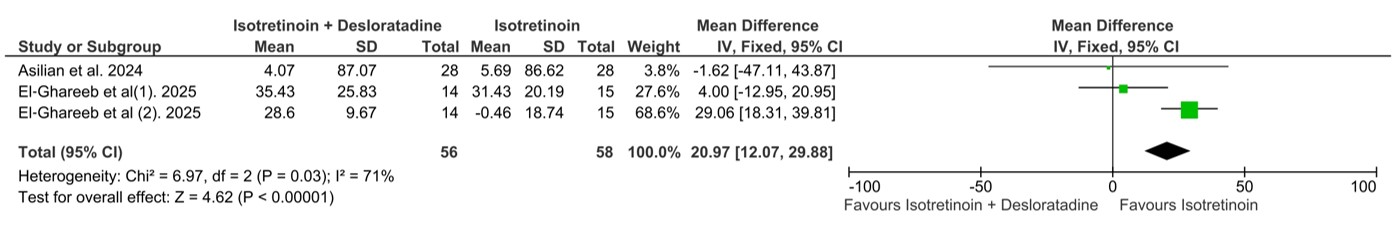
Combination therapy was initially associated with lower triglyceride levels (pooled MD = 20.97, 95% CI [12.07 to 29.88], P < 0.00001), with substantial heterogeneity ( P = 0.03; I = 71%) Figure 19.
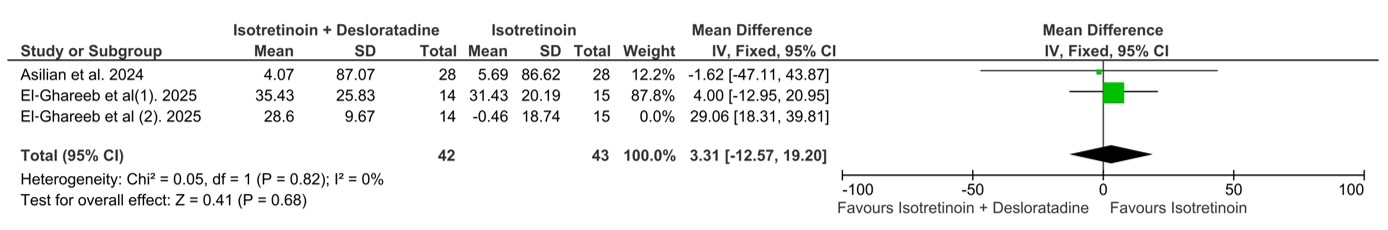
After excluding El-Gareeb et al., heterogeneity resolved ( P = 0.82; I = 0%), and the difference was no longer significant (MD = 3.31, 95% CI [–12.57 to 19.20], P = 0.68) Figure 20.
Clinical Adverse Events
Acne flare
When comparing combination therapy to isotretinoin monotherapy, the risk of acne flare did not differ significantly between groups, with a non-significant trend favouring combination therapy (RR = 0.37, 95% CI [0.13 to 1.03], P = 0.06). Pooled studies were homogeneous (Chi-square P = 0.29; I² = 11%) Figure 21.
Dry lips
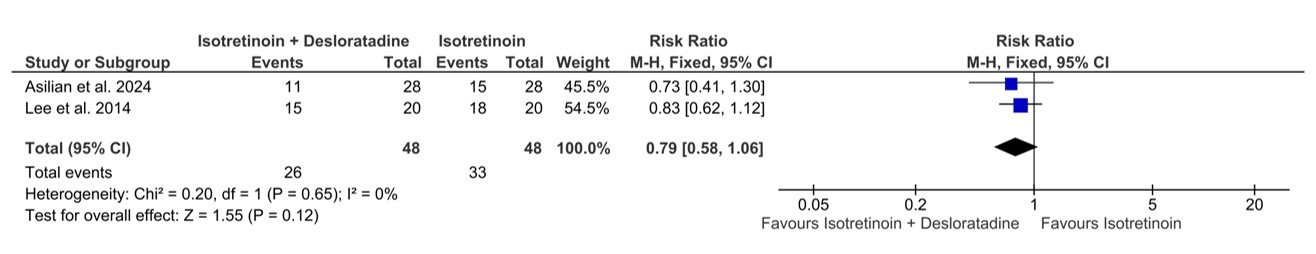
Similarly, there was no significant difference in dry lip incidence between the combination and monotherapy groups (RR = 0.79, 95% CI [0.58 to 1.06], P = 0.06). Pooled studies were homogeneous (Chi-square P = 0.65; I² = 0%) Figure 22.
Cheilitis
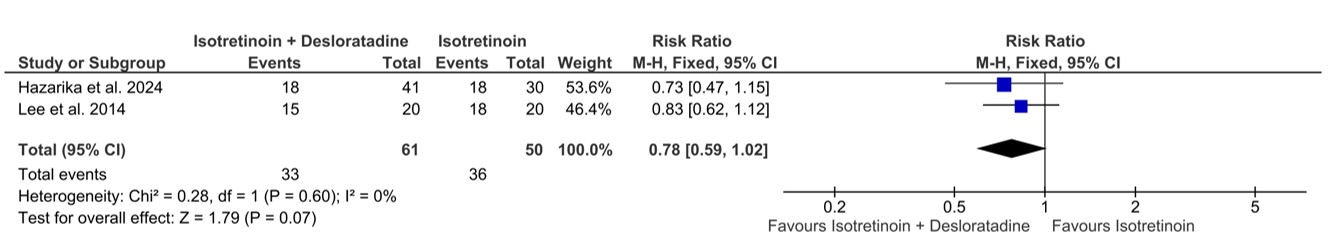
There was no significant difference in the incidence of cheilitis between the combination and monotherapy groups (RR = 0.78, 95% CI [0.59 to 1.02], P = 0.07). Pooled studies were homogeneous (Chi-square P = 0.60; I² = 0%) Figure 23.
Xerosis
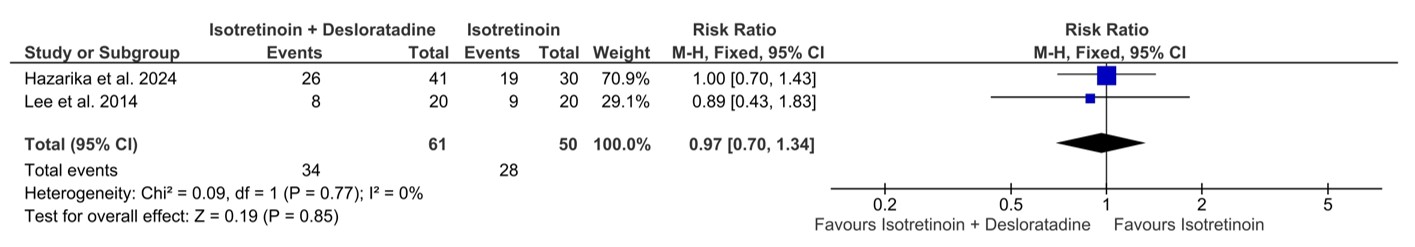
There was no significant difference in xerosis incidence between the combination and monotherapy groups (RR = 0.97, 95% CI [0.70 to 1.34], P = 0.85). Pooled studies were homogeneous (Chi-square P = 0.77; I² = 0%) Figure 24.
Pruritus
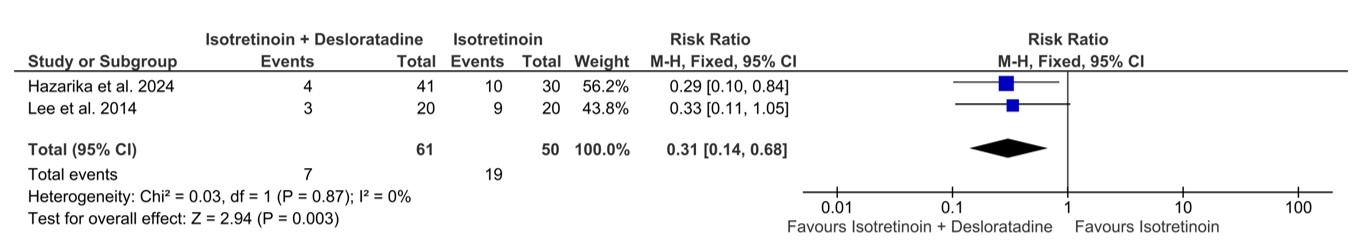
There was a statistically significant reduction in pruritus incidence in the combination group compared to monotherapy (RR = 0.31, 95% CI [0.14 to 0.68], P = 0.003). Pooled studies were homogeneous (Chi-square P = 0.87; I² = 0%) Figure 25.
Discussion
Acne vulgaris is among the most common skin conditions and often requires systemic treatment in moderate-to-severe cases. The gold-standard treatment for severe acne is isotretinoin, owing to its potent effects in reducing sebaceous gland activity and promoting epithelial turnover. While effective, isotretinoin often causes side effects, including dry lips, dry skin, and itching, which can lead patients to discontinue the medication [22]. Recently, there has been growing interest in improving the safety of isotretinoin by combining it with adjunctive agents. This systematic review and meta-analysis evaluated the efficacy and safety of combining isotretinoin with desloratadine, a second-generation antihistamine, compared with isotretinoin alone for the treatment of acne vulgaris.
Our analysis of six RCTs identified in our search indicates that combining isotretinoin with desloratadine is more effective than isotretinoin alone in reducing acne severity, as indicated by GAGS scores. This is consistent with findings from individual randomized controlled trials, including those by El-Ghareeb et al. [14] and Asilian et al. [15], both of which reported superior clinical outcomes with combination therapy. Similarly, Mansoor et al. [16] reported a significantly higher efficacy rate in the combination group (77.8%) compared to monotherapy (51.9%). This finding aligns with the results of Van et al. [17], which demonstrated greater reductions in inflammatory lesions and higher patient satisfaction with combination treatment. These findings support the hypothesis that adding desloratadine may enhance the therapeutic effects of isotretinoin therapy.
Although the reductions in inflammatory and non-inflammatory lesion counts were not statistically significant, desloratadine’s impact seems more pronounced in mitigating side effects. Pruritus and dry lips are among the most common side effects of isotretinoin. In this review, the risk ratio (RR) for acne flare and dry lips slightly favored combination therapy, with results approaching, but not achieving, statistical significance (RR = 0.37 and 0.79, respectively; p = 0.06). Nevertheless, some individual studies reported improved tolerability, higher patient satisfaction, and a reduced need for symptomatic treatment during therapy (Hazarika et al. [7]; Lee et al. [6]). These improvements may hold clinical significance for treatment adherence, particularly among adolescents and young adults who are most impacted by acne vulgaris. However, these observations should be interpreted cautiously, as the overall effect on patients’ important outcomes remains uncertain. Higher tolerability often translates into fewer treatment interruptions and better outcomes. Additionally, research by Van et al. [20] in Vietnam demonstrated that combination therapy achieved a higher cure rate (45.2% versus 22.6%) and a lower average number of inflammatory lesions (0.19% versus 0.94%) than isotretinoin alone. This implies that desloratadine may improve the efficacy of isotretinoin in treating acne.
While changes in GAGS scores were used to assess treatment efficacy, no study reported a validated anchor-based minimal clinically important difference (MCID) for this outcome. Although two trials (Lee et al. [6]; Pandey et al. [4]) included patient satisfaction scales, they did not correlate these with GAGS changes, preventing the derivation of an anchor-based MCID. To aid interpretation, we applied the commonly used distribution-based 0.5 SD method, estimating an average MCID of 2.65 across studies, with a pooled mean difference of -1.81. Although GAGS improved statistically, the average effect was below a distribution-based MCID; patient-important benefits remain uncertain pending anchor-based thresholds. Data on responder rates (e.g., proportion of patients achieving ≥1 GAGS category improvement) were inconsistently reported across the studies and could not be pooled, limiting further interpretation of clinical relevance.
Desloratadine, a second-generation antihistamine, has well-established anti-inflammatory effects. It works by blocking histamine H1 receptors, modulating cytokine production, including IL-6 and TNF-, and reducing vascular permeability and leukocyte migration [23]. Recent data suggest that acne vulgaris is a primary inflammatory disease, with inflammation present at each stage of lesion development. Antihistamines may address this by dampening the immune response [24]. Moreover, desloratadine may reduce sebum production via H1 receptors on sebocytes [25]. This sebostatic effect, together with desloratadine’s anti-inflammatory properties, may account for the observed decrease in acne severity and the reduction in side effects when used with isotretinoin.
These findings suggest that clinicians may consider adding desloratadine to isotretinoin therapy for patients suffering from moderate to severe acne, especially those prone to inflammatory flares or significant pruritus. However, the overall clinical benefit remains uncertain, and routine addition cannot be recommended without further high-quality evidence. Desloratadine’s dual role as an anti-inflammatory and symptom-.A relieving agent enhances its therapeutic value while maintaining a similar side-effect profile. Furthermore, because acne treatments often require months of therapy, improving tolerability without sacrificing efficacy is a crucial therapeutic objective. The use of antihistamines may allow lower doses of isotretinoin and potentially reduce the likelihood of treatment-related dropouts, but this has not been conclusively demonstrated.
This meta-analysis possesses several notable strengths that enhance the reliability and clinical relevance of its findings. First, the study adhered to PRISMA guidelines and used the Cochrane risk-of-bias tool, ensuring transparency and robust quality assessment across the included studies [18]. Secondly, this analysis focused solely on RCTS. As per the hierarchy of evidence, RCTs are considered high-quality study designs, which lend significant strength to the results, thereby boosting validity and reducing potential bias. Additionally, a wide range of outcomes was analyzed, including efficacy measures (e.g., GAGS scores and lesion counts) and adverse effects (e.g., dry lips and acne flares), enabling a balanced evaluation of the benefit-risk profile.
Despite promising results, this meta-analysis has some limitations. The first limitation is that the included RCTs had relatively small sample sizes, and most were single-center studies conducted in specific countries (e.g., Egypt, Iran, Pakistan). This may limit the statistical power of the findings, reduce the generalisability of the results to broader populations, and increase the chance of missing minor effects. Secondly, the included studies vary in treatment duration, dosage, and timing of outcome measurement, potentially introducing heterogeneity despite low pooled I2 values. Moreover, the follow-up durations of the RCTs were limited, ranging from 1 to 4 months. However, this provides insight into the short.-term effects, it precludes concluding the long-term efficacy and safety of the combined therapy. Furthermore, several studies were found to be at high risk of bias, particularly with respect to blinding and randomization, which could affect the results. Publication bias cannot be ruled out; studies with negative or neutral results may be underrepresented. Few studies have reported long-term outcomes, leaving the sustainability of the benefits and the long-term safety profile of the combination therapy unclear.
Conclusions
The combination of desloratadine and isotretinoin may yield modest improvements in GAGS, but the clinical significance of this is uncertain. There was no consistent reduction in inflammatory or non-inflammatory lesion counts, and safety benefits remain unproven. Further large-scale, blinded RCTs using core outcome sets are needed to confirm this approach as a standard component of acne treatment protocols.
Key finding
Desloratadine appears to enhance the efficacy and tolerability of isotretinoin, supporting its position as a promising adjunctive therapy for acne management.
From the authors' abstract.
中文摘要
异维A酸联合脱氯雷他定与异维A酸单药治疗痤疮的疗效与安全性:系统综述与荟萃分析
背景:痤疮是一种常见的炎症性皮肤疾病,主要影响富含皮脂腺的部位,包括面部、胸部和背部。它通常在青春期出现,但也可能持续或在成年后出现。最近的研究表明,组胺通过皮脂细胞上的 H1 受体进一步促进炎症和皮脂分泌。脱氯雷他定是一种 H1 受体拮抗剂,具有抗炎作用并能降低皮脂角鲨烯水平,提示其作为痤疮辅助治疗的潜力。我们评估了在异维A酸治疗中加入脱氯雷他定是否能改善疗效。
方法:依据 PRISMA 指南,我们检索 PubMed、Web of Science 和 Scopus,筛选比较异维A酸加脱氯雷他定与异维A酸单药的随机对照试验(RCT)。符合条件的研究报告了全球痤疮分级系统(GAGS)评分、炎性病变计数或非炎性病变计数。结果采用均值差(MD)并给出 95% 置信区间(CI)进行汇总。
结果:共有 6 项 RCT(共 424 名患者)符合纳入标准。联合治疗在 GAGS 评分上显示出更显著的改善(汇总 MD −1.81,95% CI [−2.52; −1.1],P < 0.00001)。然而,炎性病变(汇总 MD 0.26,95% CI [−1.01; 1.54],P = 0.68)和非炎性病变(汇总 MD 0.30,95% CI [−2.24; 2.84],P = 0.82)均未见显著差异。脱氯雷他定的加入在提升治疗效果方面表现出优势,并呈现出发作次数和唇部干燥的趋势性下降,尽管这些差异未达到统计学显著性。
结论:脱氯雷他定似乎能增强异维A酸的疗效和耐受性,支持其作为痤疮管理的有前景的辅助治疗。
本中文摘要为机器辅助翻译,仅供参考;以英文摘要为准。 Machine-assisted Chinese translation of the English abstract; the English abstract is the version of record.
References
1. Williams HC, Dellavalle RP, Garner S. Acne vulgaris. Lancet. 2012: 361 [PMID: 21880356, https://doi.org/10.1016/S0140-6736(11)60321-8]
2. Akuffo-Addo E, Ramsay K, Mohsen S, Boisvert J, Mukovozov I. Visible Light in the Treatment of Acne Vulgaris. J Cutan Med Surg. 2024: 567 [PMID: 39056372, https://doi.org/10.1177/12034754241265697]
3. Bharti S, Vadlamudi HC. A strategic review on the involvement of receptors, transcription factors and hormones in acne pathogenesis. J Recept Signal Transduct Res. 2021: 105 [PMID: 32787477, https://doi.org/10.1080/10799893.2020.1805626]
4. Pandey D, Agrawal S. Efficacy of Isotretinoin and Antihistamine versus Isotretinoin Alone in the Treatment of Moderate to Severe Acne: A Randomised Control Trial. Kathmandu Univ Med J (KUMJ). 2019: 14 [PMID: 31734672].
5. Artuc M, Steckelings UM, Grutzkau A, Smorodchenko A, Henz BM. A long-term coculture model for the study of mast cell-keratinocyte interactions. J Invest Dermatol. 2002: 411 [PMID: 12190864, https://doi.org/10.1046/j.1523-1747.2002.01838.x]
6. Lee HE, Chang IK, Lee Y, Kim CD, Seo YJ, Lee JH, Im M. Effect of antihistamine as an adjuvant treatment of isotretinoin in acne: a randomized, controlled comparative study. J Eur Acad Dermatol Venereol. 2014: 1654 [PMID: 25081735, https://doi.org/10.1111/jdv.12403]
7. Hazarika N, Yadav P, Bagri M, Chandrasekaran D, Bhatia R. Oral isotretinoin with desloratadine compared with oral isotretinoin alone in the treatment of moderate to severe acne: a randomized, assessor-blinded study. Int J Dermatol. 2024: 929 [PMID: 38546101, https://doi.org/10.1111/ijd.17129]
8. Zouboulis CC. Sebaceous gland receptors. Dermatoendocrinol. 2009: 77 [PMID: 20224688, https://doi.org/10.4161/derm.1.2.7804]
9. Pelle E, McCarthy J, Seltmann H, Huang X, Mammone T, Zouboulis CC, Maes D. Identification of histamine receptors and reduction of squalene levels by an antihistamine in sebocytes. J Invest Dermatol. 2008: 1280 [PMID: 18007585, https://doi.org/10.1038/sj.jid.5701160]
10. Geha RS, Meltzer EO. Desloratadine: A new, nonsedating, oral antihistamine. J Allergy Clin Immunol. 2001: 751 [PMID: 11295678, https://doi.org/10.1067/mai.2001.114239]
11. Wu RL, Anthes JC, Kreutner W, Harris AG, West RE, Jr. Desloratadine inhibits constitutive and histamine-stimulated nuclear factor-kappaB activity consistent with inverse agonism at the histamine H1 Receptor. Int Arch Allergy Immunol. 2004: 313 [PMID: 15564772, https://doi.org/10.1159/000082325]
12. Wozna J, Baloniak A, Stepka J, Polanska A, Mojs E, Zaba R. Efficacy of Combined Oral Isotretinoin and Desloratadine or Levocetirizine vs. Isotretinoin Monotherapy in Treating Acne Vulgaris: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. Biomedicines. 2025: 1847 [PMID: 40868102, https://doi.org/10.3390/biomedicines13081847]
13. Page MJ, McKenzie JE, Bossuyt PM, Boutron I, Hoffmann TC, Mulrow CD, Shamseer L, Tetzlaff JM, Akl EA, Brennan SE, Chou R, Glanville J, Grimshaw JM, Hrobjartsson A, Lalu MM, Li T, Loder EW, Mayo-Wilson E, McDonald S, McGuinness LA, Stewart LA, Thomas J, Tricco AC, Welch VA, Whiting P, Moher D. The PRISMA 2020 statement: an updated guideline for reporting systematic reviews. BMJ. 2021: n71 [PMID: 33782057, https://doi.org/10.1136/bmj.n71]
14. El-Ghareeb MI, Kandeel AH, Khayrullah NM. Efficacy and safety of combined oral isotretinoin and desloratadine vs. isotretinoin alone in acne vulgaris: a comparative study. Arch Dermatol Res. 2025: 689 [PMID: 40204949, https://doi.org/10.1007/s00403-025-04145-7]
15. Asilian A, Abedini M, Iraji F, Jahanshahi A. Comparing the efficacy of oral isotretinoin alone and in combination with desloratadine in treating moderate to severe acne vulgaris: a randomized clinical trial. Iranian Journal of Dermatology. 2024: 153
16. Mansoor M, Saeed W, Khan FN, Latif A, Altaf F. Efficacy of oral isotretinoin in combination with desloratadine versus oral isotretinoin alone in the treatment of moderate acne vulgaris2024:
17. Van TN, Thi LD, Trong HN, Van TC, Minh TT, Minh PPT, Huu ND, Cam VT, Huyen ML, Hau KT, Gandolfi M, Satolli F, Feliciani C, Tirant M, Vojvodic A, Lotti T. Efficacy of Oral Isotretinoin in Combination with Desloratadine in the Treatment of Common Vulgaris Acne in Vietnamese Patients. Open Access Maced J Med Sci. 2019: 217 [PMID: 30745963, https://doi.org/10.3889/oamjms.2019.054]
18. Sterne JAC, Savovic J, Page MJ, Elbers RG, Blencowe NS, Boutron I, Cates CJ, Cheng HY, Corbett MS, Eldridge SM, Emberson JR, Hernan MA, Hopewell S, Hrobjartsson A, Junqueira DR, Juni P, Kirkham JJ, Lasserson T, Li T, McAleenan A, Reeves BC, Shepperd S, Shrier I, Stewart LA, Tilling K, White IR, Whiting PF, Higgins JPT. RoB 2: a revised tool for assessing risk of bias in randomised trials. BMJ. 2019: l4898 [PMID: 31462531, https://doi.org/10.1136/bmj.l4898]
19. Egger M, Davey Smith G, Schneider M, Minder C. Bias in meta-analysis detected by a simple, graphical test. BMJ. 1997: 629 [PMID: 9310563, https://doi.org/10.1136/bmj.315.7109.629]
20. Terrin N, Schmid CH, Lau J, Olkin I. Adjusting for publication bias in the presence of heterogeneity. Stat Med. 2003: 2113 [PMID: 12820277, https://doi.org/10.1002/sim.1461]
21. Norman GR, Sloan JA, Wyrwich KW. Interpretation of changes in health-related quality of life: the remarkable universality of half a standard deviation. Med Care. 2003: 582 [PMID: 12719681, https://doi.org/10.1097/01.MLR.0000062554.74615.4C]
22. Zaenglein AL, Pathy AL, Schlosser BJ, Alikhan A, Baldwin HE, Berson DS, Bowe WP, Graber EM, Harper JC, Kang S, Keri JE, Leyden JJ, Reynolds RV, Silverberg NB, Stein Gold LF, Tollefson MM, Weiss JS, Dolan NC, Sagan AA, Stern M, Boyer KM, Bhushan R. Guidelines of care for the management of acne vulgaris. J Am Acad Dermatol. 2016: 945 [PMID: 26897386, https://doi.org/10.1016/j.jaad.2015.12.037]
23. Simons FE. Advances in H1-antihistamines. N Engl J Med. 2004: 2203 [PMID: 15548781, https://doi.org/10.1056/NEJMra033121]
24. Tanghetti EA. The role of inflammation in the pathology of acne. J Clin Aesthet Dermatol. 2013: 27 [PMID: 24062871, PMCID: PMC3780801].
25. Dreno B, Dagnelie MA, Khammari A, Corvec S. The Skin Microbiome: A New Actor in Inflammatory Acne. Am J Clin Dermatol. 2020: 18 [PMID: 32910436, https://doi.org/10.1007/s40257-020-00531-1]
Data Availability Statement
All data analyzed during this study are included in this published article.
License
Copyright (c) 2026 Ahmed S Mohamed, Mazen Kafienah, Meena Rabi, Paul Fabian, Ali Gebril Ali, Mohamed Ali Abdel Rahman, Ayla Amjad, Eslam Seddik

This work is licensed under a Creative Commons Attribution 4.0 International License.
Copyright and Licensing
All articles published in ASIDE Internal Medicine are open access and freely available online immediately upon publication, without embargo.
This journal applies the terms of the Creative Commons Attribution 4.0 International License (CC BY 4.0). Under this license, anyone may copy, redistribute, remix, transform, and build upon the material for any purpose, even commercially, provided that proper credit is given to the original author(s), a link to the license is provided, and any changes made are indicated.
-
License link: https://creativecommons.org/licenses/by/4.0/
-
Machine-readable license metadata is embedded in each article and its DOI record.
Copyright Holder
Copyright in all articles remains with the author(s). ASIDE Internal Medicine is published and owned by the American Society for Inclusion, Diversity, and Equity in Healthcare (ASIDE). By submitting a manuscript, authors agree to grant the publisher a non-exclusive license to publish, distribute, and archive the work under the terms of the CC BY 4.0 license.
Third-party Material
Any material (e.g., images, figures, or tables) not covered by CC BY 4.0 will be clearly indicated in the article. Users must obtain permission directly from the copyright holder for reuse of such third-party material.
Author Rights and Self-Archiving
Authors are permitted to deposit all versions of their work (preprint, author’s accepted manuscript, and version of record) in institutional or subject repositories of their choice immediately upon publication, without embargo, provided that the DOI and license information are included.

Published
Issue
Section
Categories
How to Cite
Article history
- Received
- 10 Sep 2025
- Received in revised form
- 20 Jan 2026
- Accepted
- 31 Jan 2026
- Published
- 7 Feb 2026
