
Ocular Trauma Patterns in the Middle East and North Africa: A Scoping Review with Emphasis on Iraq
DOI:
https://doi.org/10.71079/ASIDE.HS.042826665Abstract
Background: Ocular injury is one of the leading causes of preventable monocular blindness globally. These injuries have multiple etiologies, with socioeconomic factors and geopolitical instability as the main drivers. A unique combination of these factors can be seen in the MENA region.
Methods: This scoping review used a structured analysis of published research. We searched PubMed and Scopus (2004–2025) using terms for ocular trauma and MENA countries. Two reviewers independently screened titles, abstracts, and full texts against predefined inclusion criteria that accepted original research, reviews, and case series; a third reviewer resolved disagreements. Data were extracted using a standardized form and synthesized descriptively. No formal quality appraisal was performed.
Results: The search identified 918 records, of which 25 were included. Etiological patterns differed markedly across countries. In Iraq, conflict-related mechanisms (blasts, bullets) dominated in military cohorts, alongside civilian motorcycle accidents. In other MENA countries, road traffic accidents and occupational injuries were more frequently reported. Management challenges in Iraq were compounded by limited primary eye care infrastructure and high rates of enucleation. Pediatric trauma was also a major concern. Population‑based civilian data from conflict‑affected settings remain scarce.
Conclusion: Ocular trauma is a major health issue in Iraq, with patterns suggesting an association with decades of conflict. However, population‑based comparative data are very limited. This scoping review highlights evidence gaps, particularly the scarcity of population-based civilian data from conflict-affected settings.
Keywords:
Ocular Trauma, War Injuries, Blindness, MENA, Iraq, Scoping ReviewFull Text
Introduction
Ocular trauma is a critical public health problem, accounting for a substantial proportion of monocular blindness worldwide. It significantly affects individual quality of life, reducing their economic productivity and increasing healthcare costs.
The pattern of injury is largely linked to the local environment, culture, industry, and safety standards. The MENA region, with its vast geographic and political diversity, offers a critical lens for examining these relationships. While countries in the Gulf Cooperation Council (GCC) have advanced rapidly in healthcare, including ophthalmic care, others deal with the aftermath of conflict, economic instability, and limited healthcare resources. Iraq stands out within this continuum, having endured decades of war, economic sanctions, and internal conflict. The ophthalmological consequences of this are severe and distinct.
This review aims to evaluate the available scientific literature on ocular trauma in the MENA region by comparing the etiological factors and management challenges in Iraq with those of neighboring countries. Based on the available evidence, we interpret that prolonged conflict in Iraq is associated with a distinct profile of severe ocular injuries and treatment needs, though population-based comparative data remain limited.
Methods
Study Design and Selection
This review was conducted as a scoping review following the framework of Arksey and O’Malley and reported in accordance with the PRISMA ScR (Preferred Reporting Items for Systematic Reviews and Meta Analyses extension for Scoping Reviews) checklist. A protocol was not registered. We searched PubMed and Scopus for articles published between January 2004 and June 2025. An initial PubMed search identified relevant keywords. These were used in a systematic search strategy that combined free-text and Boolean terms applied to both databases. These search terms for ocular trauma and MENA countries included the following:
Two reviewers independently screened titles and abstracts, followed by full-text review. A third reviewer resolved disagreements. The inclusion criteria were original research, reviews, and case series in English reporting on the etiology, epidemiology, or management of ocular trauma in MENA countries. Exclusion criteria: non-English publications, studies not focused on trauma, editorials, preclinical studies, and studies conducted outside the MENA region.
Articles were systematically grouped by their primary country or region of focus, primary mechanism of injury (e.g., blast, road traffic accidents RTA, occupational), and key clinical themes (e.g., pediatric trauma, surgical outcomes, rehabilitation). Data relevant to Iraq were extracted and analyzed in parallel with data from other MENA nations, like Iran, Saudi Arabia, and Jordan, to enable a direct comparative analysis of epidemiological patterns, management protocols, and public health implications.
Data Extraction and Synthesis
Microsoft Excel was used to manage extracted data. Authors, year, country, study design, population (civilian, military, or mixed), primary injury mechanism, and key clinical findings were collected. Data were grouped by country Figure 1. Given heterogeneity in study designs and population, no meta-analysis was performed. Synthesis is descriptive and comparative. All included studies were summarized in a single table Table 2. Risk of bias assessment was not performed, consistent with scoping review methodology. Findings were presented as descriptive patterns rather than definitive comparative epidemiology.
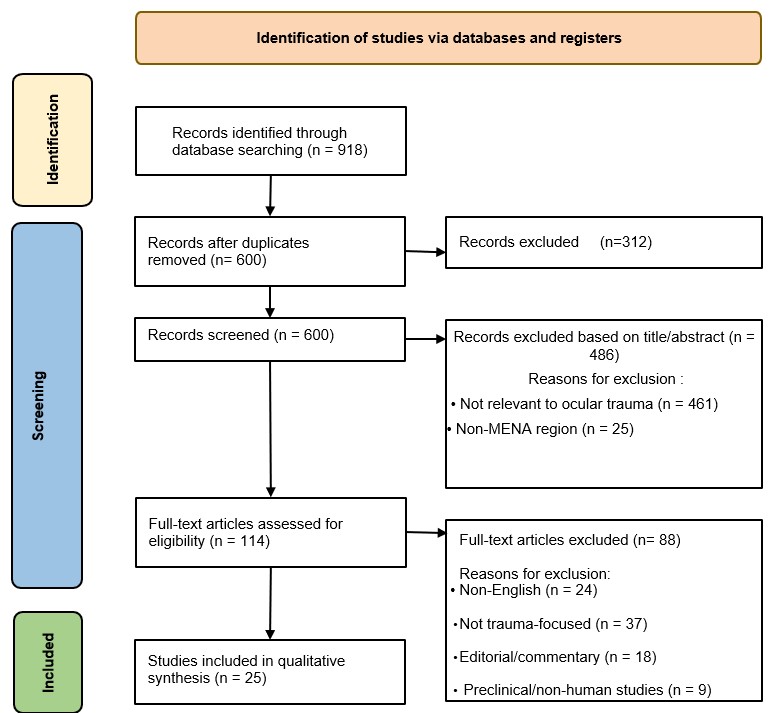
Results
The initial search yielded 918 records. After duplications had been removed, 600 titles and abstracts were screened, and 486 were excluded. The full text of 114 articles was assessed for eligibility. A total of 25 studies from the MENA region met the inclusion criteria and were included in the qualitative synthesis Figure 1. Of the 25 included studies, 11 focused on Iraq (including those that covered both Iraq and Afghanistan), 3 on Iran, 1 on Saudi Arabia, 1 on Jordan, 2 on Palestine/Gaza, 1 on the Levant, 1 on Turkey, and 1 examined the MENA region as a whole. Several studies involved military personnel, while others focused on civilian or pediatric populations. To ensure transparency, the evidence is presented in two tiers: primary epidemiologic studies (cross sectional, cohort, and case series reporting original trauma data) form the basis for all comparative statements about injury mechanisms, severity, and outcomes. Reviews, meta-analyses, and service-oriented papers are cited only for contextual background (e.g., infrastructure or rehabilitation discussions) and are not used for direct epidemiological comparisons.
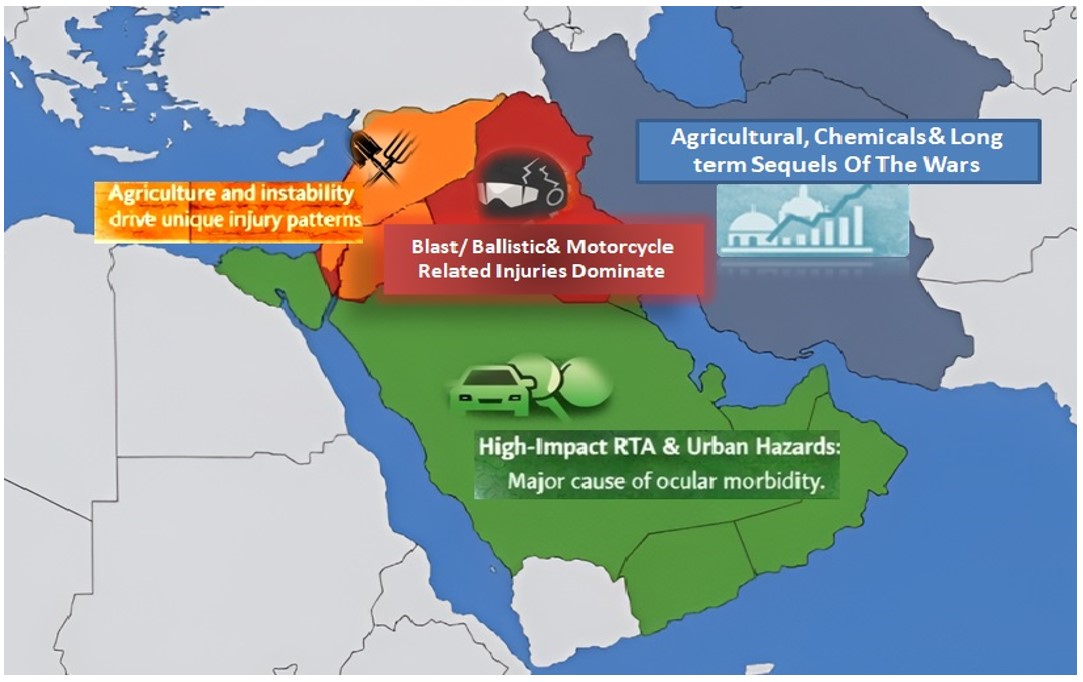
Epidemiological patterns and etiological comparison The etiology of ocular trauma in MENA is a direct reflection of local realities. The provided literature reveals a clear contrast between conflict-affected zones like Iraq and more stable regions. As shown in Table 1.
While Iraq represents an extreme within the conflict injury spectrum, a gradient of instability and resource scarcity exists across the region.
| Author(s), Year | Country/ Region | Study Design | Sample Size (N) | Study Setting | Denominator / Population at Risk | Population | Primary Mechanism(s) | Key Findings |
|---|---|---|---|---|---|---|---|---|
| Sulaiman II et al., 2024 | Iraq | Review/meta-analysis (Tier 2) | 688 | Military & civilian hospitals | Not applicable | Civilian/ military | Ballistic | High enucleation rates; penetrating orbital trauma |
| Blanch RJ et al., 2011† | Iraq | Case series | 63 | British military hospital (Iraq/Afghanistan) | All combat eye injuries referred | Military personnel | Blast/ fragmentation | 52% open globe |
| Justin GA et al., 2020† | Iraq | Cohort | 652 | U.S. military tertiary hospital | All orbital fractures referred | Military personnel | Blast | 31.3% NLP |
| Thach AB et al., 2008† | Iraq | Case series | 797 severe eye injuries | U.S. military registry | Combat zone injuries 2003–2005 | Military personnel | Blast/ fragmentation | 116 enucleations; 438 open globe |
| Hashim ZA et al., 2024† | Iraq | Cross sectional | 335 | Iraqi tertiary hospitals | Consecutive motorcycle accident patients | Civilian | Motorcycle accidents | 17% severe; lid/corneoscleral injuries |
| Yulish M et al., 2012† | Levant | Case series | 119 | Regional hospital | Agricultural workers presenting with eye injury | Agricultural workers | Olive harvesting | Corneal perforations |
| Hashemi H et al., 2015† | Iran | Cross sectional | 5190 | Population based | General population aged 40–64 | Civilian | Mixed | Lifetime trauma prevalence 8.57% (blunt 3.91%, sharp 3.82%, chemical 1.93%) |
| Challa NK et al., 2024† | Saudi Arabia | Cross sectional | 300 truck drivers | Truck driving company | All active drivers | Civilian | RTA | Refractive error linked to RTA risk |
| Odat TAM et al., 2014† | Jordan | Case series | 21 | Tertiary eye center | Consecutive cases | Civilian | Prickly pear spine | Keratoconjunctivitis |
| Al Barqi M et al., 2022† | Saudi Arabia | Case series | 3 | Tertiary eye center | Fireworks injuries during celebrations | Civilian | Fireworks | Severe open globe |
| Al Amry M et al., 2021† | Saudi Arabia | Case series | 36 | Tertiary eye center, Riyadh | Consecutive terror-related trauma | Civilian | Terror-related (blast) | 77.8% NLP; devastating outcomes |
| Harris JP et al., 2021† | Iraq | Cohort | 890 eyes | U.S. military registry | All combat open globe injuries | Military personnel | Blast | 32.02% open globe injuries |
| Shakarchi F., 2025 | Iraq | Cross-sectional (service) | 2805 primary health centers | National primary care survey | All PHCs in Iraq | Civilian | Mixed (context) | Only 2%(n=63) offer eye services |
| Bahremani E et al., 2023 | MENA region | Cross-sectional (burden study) | Not specified | Global Burden of Disease | MENA population | Civilian | Mixed (all cause) | Iraq age-standardized prevalence 7188.6/100,000 |
| Holmes CJ et al., 2019† | Iraq | Cohort | 19 | British military registry | All combat eye injuries requiring surgery | Military personnel | Blast/ fragmentation | Outcomes of evisceration/ enucleation |
| Keenan TDL et al., 2011† | Palestinian territories | Case series | 32 | Tertiary hospital, Gaza | Consecutive enucleations/ eviscerations | Civilian/ mixed | Conflict related | High rates of enucleation |
| Ciftci MD et al., 2023 | Turkey | Case series (surgical technique) | 9 | Tertiary eye center | Corneal perforations | Civilian | Corneal perforations | Sandwich technique + amniotic membrane is effective |
| Arevalo JF et al., 2012 | Saudi Arabia | Review (Tier 2) | Not applicable | Not applicable | Not applicable | Civilian | Penetrating trauma | Sympathetic ophthalmia prevention |
| Hayder Abdul Al Husain et al., 2023† | Iraq | Cross sectional | 120 pediatric patients | Pediatric ophthalmology clinic | Consecutive clinic attendees | Pediatric | Mixed | Home-occurring open globe wounds are preventable |
| Hosseini H et al., 2011† | Iran | Cross sectional | 278 | Tertiary hospital (southern Iran) | All pediatric ocular trauma | Pediatric | Sharp/blunt | Boys predominantly affected |
MENA, Middle East and North Africa; NLP, No Light Perception; PHC, Primary Health Center; RTA, Road Traffic Accident. † Denotes studies included in the primary ocular trauma analysis.
| Author(s), Year | Country/ Region | Study Design | Sample Size (N) | Study Setting | Denominator / Population at Risk | Population | Primary Mechanism(s) | Key Findings |
|---|---|---|---|---|---|---|---|---|
| Al Dahan D et al., 2019† | Saudi Arabia | Cross sectional | 199 pediatric prosthesis patients | Tertiary referral center | All pediatric prosthesis fittings | Pediatric | Mixed | Prosthesis indications after trauma |
| Masrur A et al., 2025† | Gaza (Palestine) | Observational cohort | 23 | 4 hospitals in Gaza | Consecutive CNN registry cases (March–Sept 2024) | Pediatric (<20 years) | Explosive / penetrating (conflict-related) | 11/23 (48%) ocular trauma; severe visual loss including NLP; communication barriers main challenge |
| Mousavi B et al., 2009 | Iran | Cross-sectional (chemical warfare) | 147 | Chemical warfare survivor’s registry | Iranian chemical warfare survivors | Civilian | Chemical weapons | Reduced quality of life |
| Geiling J et al., 2012 | Iraq | Review (Tier 2) | Not applicable | Not applicable | Not applicable | Military veterans | Conflict-related | Long-term care costs |
| Ramadhan HA et al., 2025† | Iraq | Cross-sectional | 71 | Halabja population survey | Chemically-exposed population | Civilian | Chemical weapons | Corneal injuries |
MENA, Middle East and North Africa; NLP, No Light Perception; PHC, Primary Health Center; RTA, Road Traffic Accident. † Denotes studies included in the primary ocular trauma analysis.
The data from Iraq is affected by the consequences of modern conflicts. Studies on military personnel from Operation Iraqi Freedom detail high rates of open globe wounds from blast and fragmentation injuries [1,2]. A study by Justin and his coworkers of U.S. personnel evacuated to a tertiary military hospital from Iraq (2001 – 2011) found that orbital fractures occurred in 34.2% (304/890) of eye injuries, with 31.3% (95/304) of those cases resulting in no light perception [3]. Earlier data from the 2003 – 2005 periods documented 797 severe eye injuries, which included 438 open globe injuries (49 bilateral) and 116 eyes requiring removal (enucleation/evisceration) [4]. Concurrently, civilian studies point to motorcycle accidents as a major cause [5] of ocular morbidity, suggesting a dual burden of conflict-related and conventional trauma. Hashim and his collaborators documented that Iraqi tertiary hospitals reported 335 ophthalmological accidents from motorcycle crashes, predominantly affecting young males (mean age 27.8 years) [5]. Injuries were classified as mild in 55.82%, moderate in 27.16%, and severe in 17.01% of cases, with lid lacerations (60.9%) and corneoscleral injuries (22.1%) being most common [5].
In contrast, studies from other regions highlight different priorities. Occupational hazards are prominent, including industrial accidents and olive-harvesting injuries in the Levant [6]. RTA is a universal cause, detailed in studies from Iran [7] and Saudi Arabia [8]. Unique environmental injuries include prickly pear spine keratoconjunctivitis in Jordan [9] and fireworks injuries during celebrations in Saudi Arabia [10]. Terror related ocular trauma is reported from a tertiary center in Saudi Arabia [11], indicating the high rate of ocular trauma in conflict affected settings; similar patterns are observed in Gaza [12,13]. Challa and Al Rasheed linked refractive error and abnormal stereopsis among truck drivers in Saudi Arabia to the risk of road traffic accidents, adding depth to the understanding of RTA etiologies [8]. This variation in the etiology of ocular trauma, from high-velocity conflict-related injuries to occupational and environmental mechanisms, directly influences the spectrum of injury severity, clinical presentation, and subsequent management challenges encountered across the region. These relationships between cause and clinical consequence are explored in the following section. The variation in the etiology of ocular trauma is illustrated in Figure 2.
Disparities in Clinical Management and Visual Prognosis
The nature of trauma determines its severity. Iraqi data emphasize high energy, devastating injuries often presenting with extensive tissue loss, multiple intraocular foreign bodies, and associated maxillofacial trauma [14,2]. In Iraq, the capacity to manage this trauma burden is severely constrained. A study revealed that only 2% of Iraq’s primary health centers offer eye-related services, which contributes to tertiary hospitals being overwhelmed; more than half of specialist hospital consultations are for conditions that are manageable at the primary level [15]. This systemic gap takes place in the context of a high overall burden of eyesight loss in Iraq (7.4% of Iraqis, all causes combined, including cataract, glaucoma, and trauma [16,15]), which is provided here only as background on the general eye health challenge.
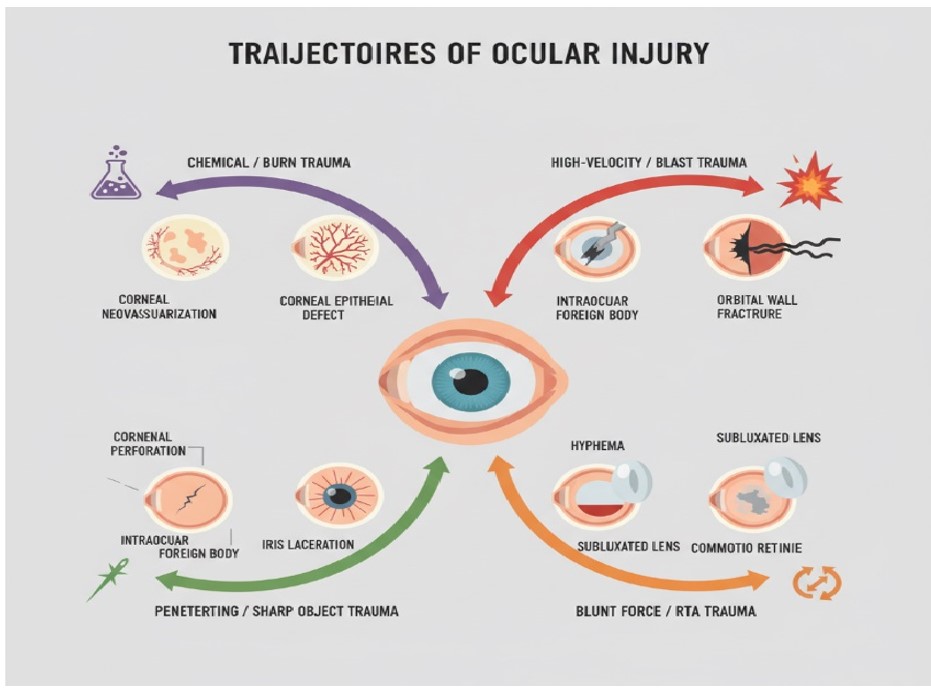
In other MENA settings, presentations, while serious, may more frequently involve isolated corneal abrasions, lid lacerations, or blunt trauma. Figure 3 shows the different kinds of trauma reported in many studies included in this review and reflects the variation in clinical courses and, consequently, the treatment needed.
The surgical burden differs accordingly. Evisceration and enucleation rates are significantly reported in the context of military trauma from Iraq [17,4] and in Palestinian territories [12], reflecting the severity of initial injuries and possibly delayed presentation. Surgical innovation is directed at complex reconstruction, such as managing orbital bullet injuries [2] and repairing corneal perforations using advanced techniques like the “sandwich” and amniotic membrane transplantation [18]. Managing sequelae like traumatic cataract and preventing sympathetic ophthalmia are critical concerns shared across the region [19] An important and recurrent theme is the high incidence of trauma among children, a vulnerable demographic across the MENA region. Ocular injury is a leading cause of preventable blindness in children all over the world. Studies from Iraq [20], Iran [21], and Saudi Arabia [22] consistently show that children represent a vulnerable demographic, suffering from domestic accidents and stray projectile injuries, often leading to lifelong visual disability and a need for prosthetic fitting.
The demand for pediatric prostheses following enucleation and evisceration was highlighted with this permanent need [13]. The challenges of delivering pediatric ophthalmic care in Gaza highlight how systemic collapse in conflict zones exacerbates trauma outcomes [13]. Furthermore, a study by Bahremani and colleagues confirmed that, while the prevalence of vision loss in MENA decreased by 11.1% from 1990 to 2019, the absolute number remains high at 32.5 million cases, with Iraq’s age-standardized prevalence rate at 7188.6 per 100,000 [16].
Furthermore, research on Iranian chemical warfare survivors provides clear evidence of the significant reduction in quality of life associated with ophthalmologic war injuries [23], a finding with direct relevance to the Iraqi civilian population [24,25].
Public Health Implications and Challenges
A distinguished variation exists between the advanced, well-resourced tertiary eye centers in the Gulf countries and the overwhelmed or fragmented systems in conflict zones. The Iraqi healthcare system bears a double burden: managing acute, complex war injuries requiring multi-specialty input and providing lifelong rehabilitation for survivors [2]. This includes not only prosthetic services but also low vision aid, psychological support for disfigurement and vision loss, and surgical management of late complications like glaucoma and retinal detachment. The strain on specialized ophthalmic surgical capacity is huge, Gaza, for example [12]. This disparity affects everything from timely primary repair to access to complex vitreoretinal surgery.
Etiology Specific Prevention Strategies
For Iraq, the primary preventive strategy is primarily political, focusing on conflict mitigation, mine clearance, and weapons control. Secondary prevention includes disseminating basic ocular first-aid knowledge to first responders and the public, and strengthening emergency trauma systems.
For other countries in the MENA region, effective strategies include enforcing occupational safety laws (e.g., mandatory eye protection in agriculture/industry), strict RTA prevention campaigns, public awareness on domestic hazards (fireworks, hazardous toys, chemicals), and community education on the dangers of traditional eye remedies.
Limitations and Future Directions
The nature of its source data limits this review. The dataset consists of English-language, predominantly hospital-based studies, which introduces publication bias and underrepresents cases that do not reach tertiary centers. There is an obvious scarcity of population-based incidence and prevalence studies from Iraq.
Future research efforts must prioritize several key directions to address the identified gaps. First, establishing standardized ocular trauma registries in Iraq is essential for capturing accurate national epidemiological data. Building on this foundation, conducting cost-effectiveness analyses of prevention strategies tailored to the Iraqi context, compared with other MENA countries, would help guide efficient resource allocation. Additionally, research is needed to develop and evaluate integrated care models capable of delivering proper ophthalmic trauma and rehabilitation services within resource-constrained, post-conflict primary health systems.
Conclusion
The etiology of ocular trauma in the MENA region is a potent indicator of its socioeconomic and political conditions. From workplace accidents to high-velocity traumas, Iraq presents itself as a significant case study in this review. The patterns observed suggest the long-term ophthalmological consequences of decades of conflict manifesting as a high volume of severe, sight-depriving injuries and a legacy of rehabilitation needs. Without population-based data, the full clinical burden of ocular trauma in conflict-affected communities remains undetermined.
Key finding
Ocular trauma is a major health issue in Iraq, with patterns suggesting an association with decades of conflict. However, population‑based comparative data are very limited. This scoping review highlights evidence gaps, particularly the scarcity of population-based civilian data from conflict-affected settings.
From the authors' abstract.
中文摘要
中东和北非地区眼外伤模式:以伊拉克为重点的范围性综述
背景:眼外伤是全球可预防单眼失明的主要原因之一。这些伤害具有多种病因,社会经济因素和地缘政治不稳定是主要驱动因素。中东和北非(MENA)地区呈现出这些因素的独特组合。
方法:本范围性综述采用结构化分析已发表研究。我们在 PubMed 和 Scopus(2004–2025)中使用眼外伤和 MENA 国家相关术语进行检索。两位评审员独立筛选标题、摘要和全文,依据预先定义的纳入标准(接受原始研究、综述和病例系列);第三位评审员解决争议。使用标准化表格提取数据并进行描述性综合。未进行正式质量评估。
结果:检索共识别 918 条记录,其中 25 条符合纳入标准。病因模式在各国之间差异显著。在伊拉克,冲突相关机制(爆炸、子弹)在军队队列中占主导地位,同时也有平民摩托车事故。在其他 MENA 国家,交通事故和职业伤害更为常见。伊拉克的管理挑战因初级眼科基础设施有限和眼球摘除率高而加剧。儿童外伤也是主要关注点。来自冲突影响地区的基于人群的平民数据仍然稀缺。
结论:眼外伤是伊拉克的主要健康问题,其模式表明与数十年的冲突相关。然而,基于人群的比较数据非常有限。本范围性综述突出了证据缺口,特别是冲突影响地区基于人群的平民数据的稀缺。
本中文摘要为机器辅助翻译,仅供参考;以英文摘要为准。 Machine-assisted Chinese translation of the English abstract; the English abstract is the version of record.
References
1. Blanch RJ, Bindra MS, Jacks AS, Scott RA. Ophthalmic injuries in British Armed Forces in Iraq and Afghanistan. Eye (Lond). 2011;25(2):218-23. [PMID: 21164529, PMCID: PMC3169213, https://doi.org/10.1038/eye.2010.190].
2. Sulaiman I, Al-Wassiti ASA, Bani Saad M, Mutar MT, Abdalridha RH, Al-Badri SG, Elboraay T, Ismail M. Penetrating orbital trauma: Comprehensive review and meta-analysis of bullet injuries. Surg Neurol Int. 2024;15:465. [PMID: 39777188, PMCID: PMC11704445, https://doi.org/10.25259/SNI_632_2024].
3. Justin GA, Turnage WA, Brooks DI, Davies BW, Ryan DS, Eiseman AS, Weichel ED, Colyer MH. Orbital Fractures and Associated Ocular Injuries in Operation Iraqi Freedom and Operation Enduring Freedom Referred to a Tertiary Care Military Hospital and the Effect on Final Visual Acuity. Ophthalmic Plast Reconstr Surg. 2020;36(1):55-60. [PMID: 31567916, https://doi.org/10.1097/IOP.0000000000001461].
4. Thach AB, Johnson AJ, Carroll RB, Huchun A, Ainbinder DJ, Stutzman RD, Blaydon SM, Demartelaere SL, Mader TH, Slade CS, George RK, Ritchey JP, Barnes SD, Fannin LA. Severe eye injuries in the war in Iraq, 2003-2005. Ophthalmology. 2008;115(2):377-82. [PMID: 17904224, https://doi.org/10.1016/j.ophtha.2007.04.032].
5. Hashim ZA, Mohammed SK, Abdulla MY, Fawzi HA. Presentations and Incidence of Ocular Injuries Caused by Motorcycle Accidents in Iraq. F1000Res. 2024;13:183. [PMID: 40183006, PMCID: PMC11966094, https://doi.org/10.12688/f1000research.142871.2].
6. Yulish M, Pikkel J. Olive-harvesting eye injuries. Middle East Afr J Ophthalmol. 2012;19(3):320-2. [PMID: 22837627, PMCID: PMC3401803, https://doi.org/10.4103/0974-9233.97939].
7. Hashemi H, Khabazkhoob M, Emamian MH, Shariati M, Mohazzab-Torabi S, Fotouhi A. Past History of Ocular Trauma in an Iranian Population-Based Study: Prevalence and its Associated Factors. Middle East Afr J Ophthalmol. 2015;22(3):377-82. [PMID: 26180480, PMCID: PMC4502185, https://doi.org/10.4103/0974-9233.159766].
8. Challa NK, Alrasheed SH. Refractive error and abnormal stereopsis association with road traffic accidents in Saudi Arabian truck drivers. Saudi J Ophthalmol. 2024;38(2):157-62. [PMID: 38988784, PMCID: PMC11232750, https://doi.org/10.4103/sjopt.sjopt_83_23].
9. Odat TA, Al-Tawara MJ, Hammouri EH. Prickly pear spine keratoconjunctivitis. Middle East Afr J Ophthalmol. 2014;21(1):61-5. [PMID: 24669148, PMCID: PMC3959044, https://doi.org/10.4103/0974-9233.124100].
10. Al Barqi M, Al Ghadeer H. Severe Ocular Trauma Caused by Fireworks Injury: A Case Series. Middle East Afr J Ophthalmol. 2022;29(2):103-5. [PMID: 37123429, PMCID: PMC10138128, https://doi.org/10.4103/meajo.meajo_217_22].
11. Al-Amry M, Chaudhry IA, Al-Kahatni E, Al-Ghadeer H. Terror-Related Ocular Trauma in Patients Presenting to a Tertiary Eye Center in the Middle East. Middle East Afr J Ophthalmol. 2021;28(4):226-9. [PMID: 35719291, PMCID: PMC9198528, https://doi.org/10.4103/meajo.meajo_316_21].
12. Keenan TD, Sargent NJ. Enucleation and evisceration in the palestinian territories. Middle East Afr J Ophthalmol. 2011;18(2):170-2. [PMID: 21731330, PMCID: PMC3119288, https://doi.org/10.4103/0974-9233.80708].
13. Masrur A, Yasin YAY, Alhalis EO, Abu Muaileq EAA. Challenges in providing ophthalmic care to children in Gaza. East Mediterr Health J. 2025;31(4):262-7. [PMID: 40448491, https://doi.org/10.26719/2025.31.4.262].
14. Harris JP, Justin GA, Brooks DI, Woreta FA, Agrawal RV, Ryan DS, Weichel ED, Colyer MH. Open-globe wounds in operation Iraqi Freedom and Operation Enduring Freedom: risk factors for poor visual outcomes and enucleation. Acta Ophthalmol. 2021;99(8):904-8. [PMID: 33565256, https://doi.org/10.1111/aos.14790].
15. Shakarchi F. Eye health in post-conflict and climate-vulnerable settings: Iraq as a case study for equitable, integrated primary eye care. AJO International. 2025;2(3). [https://doi.org/10.1016/j.ajoint.2025.100148].
16. Bahremani E, Alizadeh M, Nejadghaderi SA, Noori M, Sullman MJM, Kolahi AA, Safiri S. The burden of vision loss in the Middle East and North Africa region, 1990-2019. Arch Public Health. 2023;81(1):172. [PMID: 37749704, PMCID: PMC10521494, https://doi.org/10.1186/s13690-023-01188-y].
17. Holmes CJ, McLaughlin A, Farooq T, Awad J, Murray A, Scott R. Outcomes of ocular evisceration and enucleation in the British Armed Forces from Iraq and Afghanistan. Eye (Lond). 2019;33(11):1748-55. [PMID: 31165770, PMCID: PMC7002516, https://doi.org/10.1038/s41433-019-0480-5].
18. Ciftci MD, Selver OB. Sandwich Technique and Amniotic Membrane Transplantation as an Effective Method in Repairing Corneal Perforations. Middle East Afr J Ophthalmol. 2023;30(4):246-9. [PMID: 39959590, PMCID: PMC11823530, https://doi.org/10.4103/meajo.meajo_191_23].
19. Arevalo JF, Garcia RA, Al-Dhibi HA, Sanchez JG, Suarez-Tata L. Update on sympathetic ophthalmia. Middle East Afr J Ophthalmol. 2012;19(1):13-21. [PMID: 22346110, PMCID: PMC3277011, https://doi.org/10.4103/0974-9233.92111].
20. Abdul Al-Redha HAA. Epidemiological Trends of Pediatric Eye Diseases in Iraq: A Cross-Sectional Study. American Journal of Pediatric Medicine and Health Sciences. 2023;3.
21. Hosseini H, Masoumpour M, Keshavarz-Fazl F, Razeghinejad MR, Salouti R, Nowroozzadeh MH. Clinical and epidemiologic characteristics of severe childhood ocular injuries in southern iran. Middle East Afr J Ophthalmol. 2011;18(2):136-40. [PMID: 21731324, PMCID: PMC3119282, https://doi.org/10.4103/0974-9233.80702].
22. Al-Dahan D, Khan AO. Indications for Pediatric Ocular Prosthesis Fitting at a Referral Center in the Middle East. Middle East Afr J Ophthalmol. 2019;26(2):107-9. [PMID: 31543669, PMCID: PMC6737787, https://doi.org/10.4103/meajo.MEAJO_274_18].
23. Mousavi B, Soroush MR, Montazeri A. Quality of life in chemical warfare survivors with ophthalmologic injuries: the first results form Iran Chemical Warfare Victims Health Assessment Study. Health Qual Life Outcomes. 2009;7:2. [PMID: 19152700, PMCID: PMC2647906, https://doi.org/10.1186/1477-7525-7-2].
24. Geiling J, Rosen JM, Edwards RD. Medical costs of war in 2035: long-term care challenges for veterans of Iraq and Afghanistan. Mil Med. 2012;177(11):1235-44. [PMID: 23198496, https://doi.org/10.7205/milmed-d-12-00031].
25. Ramadhan HA, Mardan RE, Fattah FH, Mustafa AM, Habibullah IJ, Mohammed MS, Salih RQ, Mohammed KK, Mohammed SH, Abdalla BA, Ahmed SM, Kakamad FH. Prevalence of corneal injuries among Halabja populations exposed to chemical weapons: a cross-sectional study. Critical Public Health. 2025;35(1). [https://doi.org/10.1080/09581596.2025.2487206].
Data Availability Statement
No new primary data were generated in this scoping review. All data synthesized in this article were derived from previously published studies identified through PubMed and Scopus searches and from the sources cited in the reference list.
License
Copyright (c) 2026 Elaf Falih Abbas, Mohammed Mousa Imran, Mustafa Yahya Saleh, Huda Omran

This work is licensed under a Creative Commons Attribution 4.0 International License.
Copyright and Licensing
All articles published in ASIDE Health Sciences are open access and freely available online immediately upon publication, without embargo.
This journal applies the terms of the Creative Commons Attribution 4.0 International License (CC BY 4.0). Under this license, anyone may copy, redistribute, remix, transform, and build upon the material for any purpose, even commercially, provided that proper credit is given to the original author(s), a link to the license is provided, and any changes made are indicated.
-
License link: https://creativecommons.org/licenses/by/4.0/
-
Machine-readable license metadata is embedded in each article and its DOI record.
Copyright Holder
Copyright in all articles remains with the author(s). ASIDE Health Sciences is published and owned by PubPorta Publishing LLC. By submitting a manuscript, authors agree to grant the publisher a non-exclusive license to publish, distribute, archive, and identify itself as the original publisher of the work under the terms of the CC BY 4.0 license.
Academic oversight and scholarly guidance are provided by the American Society for Inclusion, Diversity, and Equity in Healthcare (ASIDE). Copyright and licensing arrangements are administered by the publisher.
Third-party Material
Any material (e.g., images, figures, or tables) not covered by CC BY 4.0 will be clearly indicated in the article. Users must obtain permission directly from the copyright holder for reuse of such third-party material.
Author Rights and Self-Archiving
Authors are permitted to deposit all versions of their work (preprint, author’s accepted manuscript, and version of record) in institutional or subject repositories of their choice immediately upon publication, without embargo, provided that the DOI and license information are included.

Published
Issue
Section
How to Cite
Article history
- Received
- 14 Mar 2026
- Received in revised form
- 18 Apr 2026
- Accepted
- 26 Apr 2026
- Published
- 28 Apr 2026
