Association of Irritable Bowel Syndrome with Dementia: A GRADE-Assessed Systematic Review and Meta-Analysis
Nawris AlhassanⒾ1, Mohamed Mohsen Helal2*, Jagdish LalⒾ3, Stanley Jung3, Lisa Worsley3
- 1Hope Clinic, Midvale, USA
- 2Faculty of Medicine, Zagazig University, Zagazig, Egypt
- 3Burnaby Chronic Pain & Rehabilitation, Burnaby, Canada
Abstract
Introduction: Numerous gastrointestinal (GI) diseases have been linked to an increased risk of dementia. Irritable bowel syndrome (IBS) is a prevalent GI disorder; however, existing studies investigating its association with dementia have reported mixed findings, and no prior meta-analysis has synthesized the available evidence.
Methods: A comprehensive search of MEDLINE (via PubMed), Scopus, and Web of Science was conducted in August 2025, with no language restrictions, to identify observational studies comparing the risk of all-cause dementia and dementia subtypes (e.g., Alzheimer's disease (AD)) in individuals with and without IBS. Pooled odds ratios (ORs) with 95% confidence intervals (CIs) were calculated using the DerSimonian–Laird random-effects model. The certainty of evidence was assessed using the GRADE approach.
Results: More than 750,000 participants were included from three cohort and two case-control studies. The pooled analysis showed that IBS was associated with significantly higher odds of all-cause dementia (OR = 1.22; 95% CI: 1.13–1.31; p < 0.00001; I² = 26%), with the overall certainty of evidence rated as high. The association remained robust across all sensitivity analyses. IBS was also significantly associated with higher odds of AD (OR = 1.27; 95% CI: 1.08–1.50; p = 0.005; I² = 64%), with the certainty of evidence rated as low.
Conclusion: Our findings consistently suggest that IBS is associated with higher rates of dementia outcomes; however, this association is derived from observational data and does not establish causality. Further well-designed prospective studies are needed to clarify the nature of this relationship.
Keywords: Irritable bowel syndrome, IBS, Dementia, All-cause dementia, Alzheimer’s
Article information
Introduction
Dementia represents a major global health challenge, primarily affecting older adults. In 2021, the estimated prevalence was approximately 57 million people worldwide, with an annual incidence of around 10 million new cases [1]. It is characterized by progressive cognitive, functional, and behavioral decline that significantly impairs daily functioning [2]. Due to its prolonged course and the high level of care required, dementia imposes substantial financial burdens, with healthcare expenditures averaging 57% higher than those for other chronic conditions [3]. Therefore, investigating the modifiable risk factors through the preclinical phase of the disease is a global public health priority, especially given the lack of approved disease-modifying therapies [4].
A growing body of evidence highlights the role of gut health in cognitive function [5]. Disturbances in gastrointestinal (GI) homeostasis have been linked to neurodegenerative processes, and some neurological disorders are thought to originate in the gut [6]. Studies suggest that gut inflammation, alterations in the gut microbiota, and changes in microbiota-derived metabolites may contribute to the pathogenesis of dementia [7]. These findings are supported by observational studies reporting significant associations between various GI disorders and the risk of developing dementia [8,9,10].
Among GI conditions, irritable bowel syndrome (IBS) is particularly common and impactful, affecting an estimated 5 – 10% of the global population [11]. It is characterized by recurrent abdominal pain or discomfort, altered visceral sensitivity, and changes in GI motility. While IBS is often diagnosed in individuals under 50, it can also affect older adults [12], making it a relevant condition to consider in dementia research.
According to recent observational research, there may be a connection between IBS and a higher risk of dementia. However, findings are inconsistent [13,14,15,16,17]. While multiple systematic reviews have examined GI disorders, namely liver diseases [18] and inflammatory bowel disease (IBD) [19,20], in relation to dementia, no comprehensive meta-analysis has focused on IBS. Given its high prevalence and distinct pathophysiology, IBS warrants separate investigation.
Therefore, this study aims to conduct a systematic review and meta-analysis to assess the association between IBS and dementia risk, including both incident risk estimates from cohort studies and exposure-outcome associations from case-control studies, and to explore potential differences by dementia subtype.
Methods
The protocol for this systematic review and meta-analysis was registered a priori on the International Prospective Register of Systematic Reviews (PROSPERO; ID: CRD420251124693). Reporting adhered to the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) guidelines, and all steps were conducted following guidelines stated in the Cochrane Collaboration Handbook [21].
Inclusion and exclusion criteria
Eligibility criteria were structured using the PICOS framework:
Only studies employing valid diagnostic methods for both IBS (exposure) and dementia (outcome) were eligible. No restrictions were placed on publication year or language. We excluded animal studies, non-comparative designs, reviews, editorials, and commentaries.
Study selection
A systematic literature search was conducted on August 5, 2025, across three electronic databases: PubMed, Scopus, and Web of Science. The search strategy contained terms related to irritable bowel syndrome (e.g., "IBS," "functional bowel disorder") and dementia (e.g., "Alzheimer’s disease," "cognitive impairment"). The full search syntax and fields for each database are provided in (Supplementary Table 1).
All identified records were imported into Rayyan software for screening. Two independent reviewers first screened titles and abstracts for relevance. Studies that appeared eligible were then subjected to full-text review against our inclusion criteria. In addition to the database search, a manual review of the reference lists of included studies was performed to capture any additional relevant evidence.
Data extraction and assessment of risk of bias
A standardized online form was developed to extract data on study characteristics, population details, outcome measures, adjustment for confounders, and risk-of-bias assessments. Data extraction was performed independently by two investigators. Web-based tools for data conversion, such as the Meta-Analysis Accelerator software [22], were used when necessary. For instance, in one study that did not report the mean age and standard deviation (SD) for the combined AD and control groups, we applied this tool to calculate the pooled mean and SD from the subgroup values.
The risk of bias for included studies was assessed using the Newcastle-Ottawa Scale (NOS) [23]. The NOS evaluates three domains: (1) selection of study participants (maximum 4 points), (2) comparability of groups (maximum 2 points), and (3) outcome assessment (cohort) or exposure ascertainment (case – control) (maximum 3 points). Scores range from 0 to 9, with 7 considered low risk of bias.
Statistical analysis
Statistical analysis plan
Our analysis examined the association between IBS diagnosis and dementia outcomes (all-cause and subtypes). This association is measured and reported in individual studies as an odds ratio (OR) or hazard ratio, with their corresponding 95% confidence intervals (CI). Given the relatively low incidence of dementia, these measures were considered approximately equivalent for pooling, an approach supported by established epidemiological principles and widely adopted in high-quality meta-analyses [24,25].
When multiple effect estimates with different levels of confounder adjustment were reported, the most fully adjusted estimate was extracted to better approximate the true association while minimizing residual confounding. We also performed subgroup analyses stratified by the level of confounder adjustment to explore its potential impact on the pooled estimates.
Main meta-analyses were performed using RevMan software (Cochrane Collaboration). Extracted ORs with their 95% CIs from each study were entered into RevMan’s built-in calculator, which automatically derives the log OR and its standard error. A random-effects model based on the DerSimonian – Laird (DL) method was employed to account for expected within- and between-study variability.
Given the small number of included studies and the anticipated substantial heterogeneity, the DL method’s tendency to underestimate between-study variance in such settings was a recognized limitation [26]. To assess the robustness of the primary pooled estimates, a sensitivity analysis was therefore conducted using the Restricted Maximum Likelihood (REML) estimator for , implemented in R (online version of RStudio; meta and metafor packages) [26]. REML provides a more conservative variance estimate than DL and was used to assess whether the main inference remained stable under a stricter model of heterogeneity. A p-value < 0.05 was considered statistically significant throughout.
Heterogeneity, sensitivity analyses, and subgroup analyses
Heterogeneity was assessed visually with forest plots and statistically using the chi-square test (p < 0.10 considered significant) and the I² statistic [25]. Publication bias was not formally assessed with funnel plots, consistent with recommendations by Sterne et al., as fewer than 10 studies were included [27].
Sensitivity analyses were performed using the leave-one-out method to assess the influence of individual studies on overall effect estimates and determine the robustness of findings.
Planned subgroup analyses were performed to investigate potential sources of heterogeneity, including study design, geographic region, and depth of confounder adjustment. For confounder adjustment, studies were categorized as minimal, moderate, or extensive based on the variables included. Minimal adjustment included only demographic factors; moderate adjustment included demographics plus clinical comorbidities (e.g., diabetes, stroke); and extensive adjustment included genetic factors (e.g., APOE allele).
Certainty of evidence assessment
The certainty of evidence was evaluated using the Grading of Recommendations Assessment, Development and Evaluation (GRADE) approach via GRADEpro software [28]. For observational studies evaluating prognostic associations (i.e., the association between IBS and dementia risk), GRADE begins with a high certainty rating [29]. It may be downgraded based on risk of bias, indirectness of evidence, inconsistency (heterogeneity), imprecision in effect estimates, and publication bias (when assessable). Upgrading was considered in cases of large effect sizes or evidence of dose-response relationships. The final certainty rating was categorized as high, moderate, low, or very low.
Study-specific methodological considerations
One included record (Konings et al., 2023) described two distinct studies that used the US-based TriNetX database [14]. First, the authors conducted a case-control study to examine the association between various diseases (including AD) and a prior diagnosis of IBS. To validate these findings, they performed a complementary cohort study within an IBS-diagnosed population from the same database, investigating the subsequent risk of developing AD. Because both analyses draw from the same database (TriNetX) during the same time frame (2005 to 2021), a single patient who has both an IBS diagnosis and a subsequent AD diagnosis would likely be included in both analyses. Including both estimates in the meta-analysis would therefore introduce double-counting of participants, violating the assumption of independent study samples and potentially inflating the pooled effect size [21]. Accordingly, only the primary (case-control) analysis was included and is referred to throughout as Konings et al. (2023); the cohort analysis was excluded from all pooled estimates.
Konings et al. (2023) reported the odds of developing AD (specifically AD rather than all-cause dementia) in relation to three distinct IBS subtypes (IBS with constipation, IBS with diarrhea, and IBS without diarrhea). Still, they did not provide a single combined effect estimate [14]. However, the authors did not clarify whether these subgroups were mutually exclusive or whether a hierarchical classification was applied to prevent overlap. Since IBS subtypes coded in routine data are often not mutually exclusive over time (patients can carry constipation and diarrhea codes at different encounters), combining these estimates in an internal meta-analysis could introduce unit-of-analysis errors and double counting. Therefore, we adopted a single-estimate approach and selected the estimate for “IBS without diarrhea” (ICD-10: K58.9) as the representative effect. We chose this specific endpoint because the authors define it as a synonym for "IBS not otherwise specified," and it constitutes the largest patient cohort in their study (N = 1,032 vs. N = 51 for IBS-Constipation and N = 143 for IBS-Diarrhea).
Another study (Tung et al. 2022) investigated the association between functional gastrointestinal disorders (FGIDs) and all-cause dementia without reporting IBS-specific data separately [15]. Nevertheless, this study was included because IBS is the most frequent FGID [30,31,32,33,34] and excluding it would omit relevant evidence.
| Study ID | Study design | Data source | Location | Study duration (years) | Total sample size | Mean age (SD) | Male n (%) |
|---|---|---|---|---|---|---|---|
| Chen 2016 | Cohort | NHIRD | Taiwan, Asia | 2000–2011 (11) | 161,490 | 51.1 (16.6) | 76,520 (47.3) |
| Konings 2023 | Case-control | TriNetX | US, North America | 2005–2021 (16.5) | 43,670 | 71.65 (8.53) | 24,233 (55.5) |
| Tung 2022 | Case-control | TPMI | Taiwan, Asia | 2013–2021 (8) | 6,600 | 73.0 (9.3) | 5,950 (90.2) |
| Yeh 2018 | Cohort | NHIRD | Taiwan, Asia | 2000–2015 (16) | 89,424 | 55.1 (18.3) | 47,920 (53.6) |
| Yuan 2024 | Cohort | UK Biobank | UK, Europe | 2006–2021 (15) | 458,181 | 56.7 (2.1) | 209,373 (45.7) |
NHIRD, National Health Insurance Research Database; TPMI, Taiwan Precision Medicine Initiative; US, United States; UK, United Kingdom; SD, standard deviation
To ensure strict comparability of both exposure and outcome definitions, the primary meta-analysis was restricted to studies evaluating all-cause dementia following an exclusive diagnosis of IBS. Therefore, Tung et al. 2022 (FGID as exposure) and Konings 2023 (AD as outcome only) were not included in the primary pooled analysis of the all-cause dementia outcome. A broader secondary analysis was subsequently conducted to provide a more comprehensive overview of dementia outcomes associated with IBS and related FGIDs by incorporating all five originally identified studies.
Results
Search results
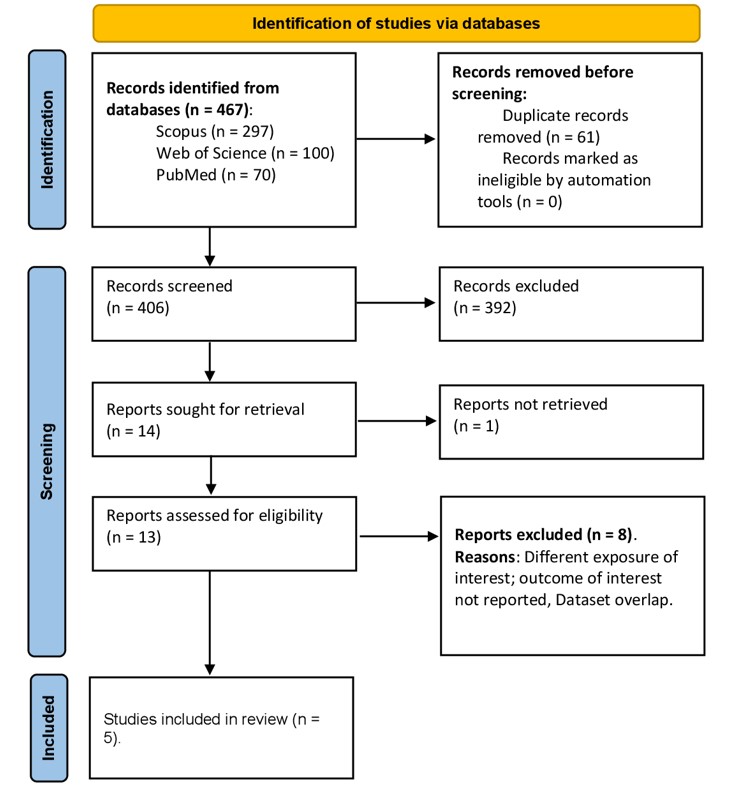
The initial search yielded 467 records. After removing 61 duplicates, 406 records remained for title and abstract screening. Of these, 392 records were excluded for failing to meet the eligibility criteria. A total of 13 studies underwent full-text review, and eight were excluded for two primary reasons: the exposure of interest was not IBS [35,36], or the studies did not report the risk of dementia or one of its subtypes [37,38,39] Figure 1. The manual search (citation analysis) identified no additional studies. Ultimately, five studies met all eligibility criteria and were included in the final systematic review and meta-analysis [13,14,15,16,17].
Study characteristics
This systematic review included five studies: three cohort studies [13,16,17] and two case-control studies [14,15]. Together, the studies had 759,365 participants, with sample sizes ranging from 6,600 to 458,181. The studies were conducted in three main countries: the United States (US), the United Kingdom (UK), and Taiwan. The male population in the studies ranged from 47.3% to 90.2%. General characteristics of the included studies and populations are summarized in Table 1.
The inclusion criteria varied slightly by study design. In case-control studies (Konings et al. 2023 and Tung et al. 2022), participants generally required a pre-existing diagnosis of dementia. In contrast, the cohort studies (Chen et al. 2016, Yeh et al. 2018, and Yuan et al. 2024) included participants with a newly diagnosed IBS. In most cases, diagnoses were established using the International Classification of Diseases (ICD)-9 or ICD-10 codes, although some studies also incorporated physician-confirmed diagnoses. Detailed inclusion and exclusion criteria, study methodologies, and dementia subtypes assessed are presented in Table 2.
Pooled risk of dementia
Some studies reported the risk of all-cause dementia alongside specific subtypes, including AD, VaD, or non-AD dementia, while others reported all-cause dementia as the sole outcome. The extracted effect estimates for each reported dementia outcome from individual studies are summarized in Table 3.
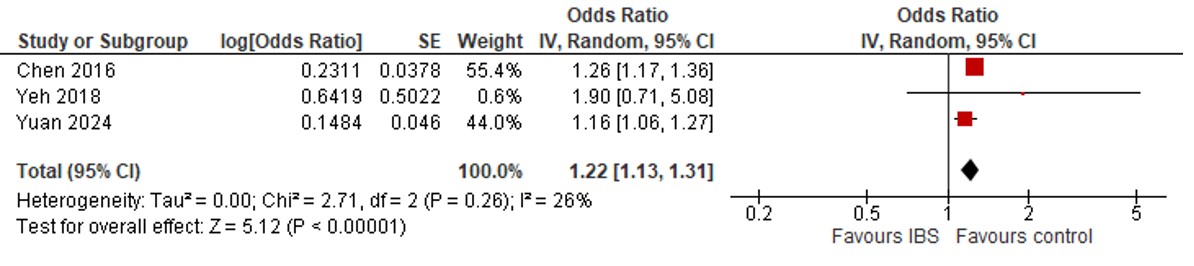
The primary restricted analysis, limited to IBS as the exposure and all-cause dementia as the outcome (n = 3 studies), demonstrated that individuals with IBS had 22% higher odds of developing all-cause dementia compared with controls (OR = 1.22; 95% CI: 1.13 – 1.31; p < 0.00001, I² = 26%) Figure 2.
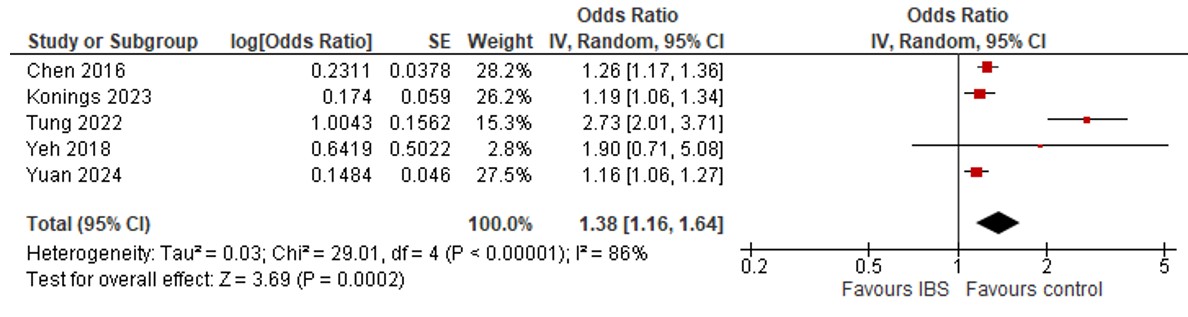
The broader secondary analysis incorporating all five studies (see Section 2.5) demonstrated that individuals with IBS/FGID had 38% higher odds of developing dementia outcomes compared with controls (OR = 1.38; 95% CI: 1.16 – 1.64; p = 0.0002). This analysis showed significant heterogeneity (I² = 86%, p < 0.0001) Figure 3.
Sensitivity analyses
To explore potential sources of heterogeneity and assess the robustness of the results, we performed a leave-one-out sensitivity analysis in both the primary and secondary analyses. Results remained consistent across all study exclusions in both analyses Table 4 and Table 5; (Supplementary Figures 1 and 2).
Exploratory subgroup analyses
Subgroup analyses were conducted to explore key influencing factors by stratifying studies according to study design, geographical area, and depth of confounder adjustment Table 6; (Supplementary Figures 3-5). These analyses were applied to the broader secondary dementia pool rather than the primary restricted pool, as the larger dataset reduced the risk of yielding single-study subgroups – an outcome that would limit any meaningful contribution to characterizing the IBS – dementia association.
Pooled risk of Alzheimer’s disease
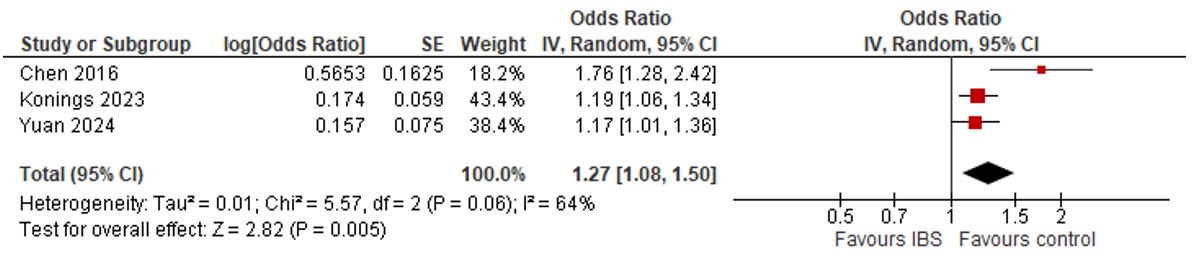
Among dementia subtypes, AD was the only outcome reported in more than one study Table 2, column "Type of dementia assessed"; Table 3. In the pooled analysis of three studies (Chen et al. 2016; Konings et al. 2023; Yuan 2024), IBS was significantly associated with increased odds of AD (OR = 1.27; 95% CI: 1.08 – 1.50; p = 0.005), with moderate heterogeneity (I² = 64%, p = 0.06) Figure 4.
In the leave-one-out sensitivity analysis, the direction of the association remained consistent across all iterations; however, statistical significance was lost upon individual exclusion of Konings et al. (2023) and Yuan et al. (2024), indicating that the pooled estimate is sensitive to these two studies.
Meta-analysis using the REML approach
To assess the robustness of the primary pooled estimates against a more conservative heterogeneity model, all meta-analyses were re-run using the REML approach. A comparative summary of the DL and REML estimates is presented in Table 7, with the corresponding REML forest plots provided in (Supplementary Figures 6 - 8).
Consistent with the statistical properties of the REML estimator, this method produced wider CIs and higher p-values across the included analyses. Despite these adjustments for between-study variance, neither the magnitude of the effect estimates nor the overall statistical significance was materially altered Table 7.
GRADE assessment
We applied the GRADE methodology to evaluate the certainty of evidence for the outcomes of this review Table 8. For the primary analysis of all-cause dementia, the certainty of evidence was rated as high. For the secondary analysis of dementia outcomes, certainty was rated as low, with downgrading applied in the domains of inconsistency/heterogeneity and indirectness. Although the observational nature of the included studies is inherently associated with greater heterogeneity in meta-analyses [40], and some authors consider these insufficient grounds for downgrading, we judged the degree of heterogeneity in this analysis to be substantial enough to warrant downgrading (I² = 83%; p < 0.0001).
For the AD outcome, certainty was similarly rated as low, with downgrading applied in the domains of inconsistency and indirectness. The downgrading for indirectness was driven by the fact that, in one of the three contributing studies, AD was not the primary outcome of interest; the study was primarily designed to investigate Parkinson’s disease [14].
Risk of bias assessment
The methodological quality of the included studies was evaluated using NOS Table 2. Scores ranged from 8 to 9 out of 9, indicating high quality and adequate fulfillment of most NOS domains.
| Study ID | Inclusion criteria | Exclusion criteria | Diagnosis of IBS | Subjects with IBS n (%) | Type of dementia assessed | Diagnosis of dementia | Dementia cases n (%) | NOS score |
|---|---|---|---|---|---|---|---|---|
| Chen 2016 | Patients aged 20 years with newly diagnosed IBS (2000–2011) identified from the LHID2000 database. A non-IBS cohort was randomly selected from individuals without IBS during the same period and matched. | Patients with a prior history of dementia or missing medical information. | ICD-9-CM codes | 32,298 (20.0) | All-cause, AD, non-AD dementia | ICD-9-CM codes | 4,062 (2.5) | 9 |
| Konings 2023 | First diagnosis of AD between ages 50–90, with 2 years of ambulatory visits before diagnosis (between Jan 1, 2005, and July 1, 2021). | Patients with a diagnosis of dementia before their first AD diagnosis. | ICD-10 codes | NA | AD | ICD-10 codes | 19,046 (43.6) | 9 |
| Tung 2022 | Dementia cases diagnosed between Jan 1, 2013, and Apr 30, 2021; controls without dementia up to Apr 30, 2021; age- and sex-matched at a 1:10 ratio. | Patients who did not consent to data inclusion. | NA | 282 (4.2) | All-cause dementia | ICD-9 codes | 600 (9.1) | 9 |
| Yeh 2018 | Adults with 3 outpatient visits for IBS within 1 year. | Patients 20 years or with psychiatric disorders diagnosed before 2000 or before the first IBS visit. | Rome criteria | 22,356 (25.0) | All-cause dementia | Diagnosed by psychiatrists | 672 (0.7) | 8 |
| Yuan 2024 | Adults without baseline dementia and with available genetic information. | Patients with dementia at baseline, dementia within the first year of follow-up, or missing genetic data. | Diagnostic codes from inpatient, primary care, registries, self-report | 480 (0.1) | All-cause dementia, AD, VaD | ICD-9/10 codes | 6,415 (1.4) | 9 |
IBS, irritable bowel syndrome; AD, Alzheimer’s disease; VaD, vascular dementia; ICD-9-CM, International Classification of Diseases, 9th Revision, Clinical Modification; ICD-10, International Classification of Diseases, 10th Revision; NOS, Newcastle–Ottawa Scale; NA, not available
| Study ID | Fully adjusted effect estimate | 95% CI (LL) | 95% CI (UL) | Variables adjusted for |
|---|---|---|---|---|
| Chen 2016 | All-cause dementia: HR = 1.26* | 1.17 | 1.35 | Age, sex, diabetes, hypertension, stroke, CAD, head injury, depression, epilepsy |
| AD dementia: HR = 1.76# | 1.28 | 2.43 | ||
| Non-AD dementia: HR = 1.24 | 1.15 | 1.33 | ||
| Konings 2023 | AD dementia: OR = 1.19*# | 1.06 | 1.34 | Age, sex, race, ethnicity |
| Tung 2022 | FGID and all-cause dementia: OR = 2.73* | 2.01 | 3.71 | APOE 4 allele, CVA, sleep, FGIDs |
| Yeh 2018 | All-cause dementia: HR = 1.90* | 0.71 | 2.57 | Age, sex, education, marital status, comorbidities (CCI), season, residence, insurance |
| Yuan 2024 | All-cause dementia: HR = 1.16* | 1.06 | 1.27 | Age, sex, deprivation index, education, BMI, activity, diet, smoking, alcohol, HTN, stroke, depression, polygenic risk score |
| AD dementia: HR = 1.17# | 1.01 | 1.35 | ||
| VaD dementia: HR = 1.38 | 1.13 | 1.70 |
AD, Alzheimer’s disease; IBS, irritable bowel syndrome; VaD, vascular dementia; HR, hazard ratio; OR, odds ratio; CI, confidence interval; LL, lower limit; UL, upper limit; FGID, functional gastrointestinal disorder; CAD, coronary artery disease; APOE, apolipoprotein E; CVA, cerebrovascular accident; FGIDs, functional gastrointestinal disorders; CCI, Charlson comorbidity index; BMI, body mass index; HTN, hypertension; * Estimates used in the dementia outcomes analysis; # Estimates used in the Alzheimer's disease analysis
| Excluded study | OR (95% CI) | p-value | Chi-squared p-value, I |
|---|---|---|---|
| Chen 2016 | 1.16 (1.06; 1.27) | 0.0009 | 0.33, 0% |
| Yeh 2018 | 1.21 (1.12; 1.32) | 0.16, 48% | |
| Yuan 2024 | 1.26 (1.17; 1.36) | 0.41, 0% |
Significant test p-values are bold.
| Excluded study | OR (95% CI) | p-value | Chi-squared p-value, I |
|---|---|---|---|
| Chen 2016 | 1.50 (1.13; 2.00) | 0.006 | , 90% |
| Konings 2023 | 1.50 (1.18; 1.90) | 0.001 | , 89% |
| Tung 2022 | 1.21 (1.15; 1.28) | 0.41, 0% | |
| Yeh 2018 | 1.37 (1.15; 1.63) | 0.0004 | , 89% |
| Yuan 2024 | 1.53 (1.18; 1.98) | 0.001 | , 88% |
Significant test p-values are bold.
| Number | OR (95% CI) | p-value | Chi-squared p-value, I | |
|---|---|---|---|---|
| All studies | 5 | 1.38 (1.16; 1.64) | 0.0002 | , 86% |
| Study design | ||||
| Cohort | 3 | 1.22 (1.13; 1.31) | 0.26, 26% | |
| Case-control | 2 | 1.78 (0.79; 4.01) | 0.16 | , 96% |
| Geographical region | ||||
| Asia (Taiwan) | 3 | 1.84 (0.97, 3.48) | 0.06 | , 92% |
| America (USA) | 1 | 1.19 (1.06; 1.34) | 0.003 | Not applicable |
| Europe (UK) | 1 | 1.16 (1.06; 1.27) | 0.001 | Not applicable |
| Depth of adjustment for confounders | ||||
| Minimal Adjustment | 1 | 1.19 (1.06; 1.34) | 0.003 | Not applicable |
| Moderate Adjustment | 2 | 1.26 (1.17, 1.36) | 0.41, 0% | |
| Extensive Adjustment | 2 | 1.76 (0.76, 4.06) | 0.19 | , 96% |
Significant test p-values are bold.
| Analysis | Model | OR (95% CI) | p-value |
|---|---|---|---|
| Exclusive IBS and all-cause dementia | DL | 1.22 (1.13; 1.31) | |
| REML | 1.22 (1.13; 1.32) | ||
| IBS/FGID and dementia outcomes | DL | 1.38 (1.16; 1.64) | 0.0002 |
| REML | 1.49 (1.08; 2.06) | 0.0165 | |
| IBS and AD | DL | 1.27 (1.08; 1.50) | 0.005 |
| REML | 1.29 (1.05; 1.57) | 0.014 |
OR, odds ratio; CI, confidence interval; DL, DerSimonian–Laird; REML, restricted maximum-likelihood; IBS, irritable bowel syndrome; FGID, functional gastrointestinal disorder; AD, Alzheimer's disease.
| Analysis | Number of studies | Study design | Risk of bias | Inconsistency | Indirectness | Imprecision | Other considerations* | Overall certainty |
|---|---|---|---|---|---|---|---|---|
| Exclusive IBS and all-cause dementia | 3 | Observational | not serious | not serious | not serious | not serious | none | High |
| IBS/FGID and dementia outcomes | 5 | Observational | not serious | serious | serious | not serious | none | |
| Low | ||||||||
| IBS and AD | 3 | Observational | not serious | serious | serious | not serious | none | |
| Low |
*Other considerations: publication bias, large effect, plausible confounding, dose-response gradient
Discussion
Summary of main findings
This systematic review and meta-analysis examined the association between IBS and dementia across three pre-specified analyses. In the primary analysis, restricted to cohort studies with IBS-exclusive exposure and all-cause dementia as the outcome, IBS was associated with a 22% increase in the odds of developing all-cause dementia (OR = 1.22; 95% CI: 1.13 – 1.31), with low heterogeneity (I² = 26%) and high-grade certainty of evidence. The secondary analysis, which incorporated all five studies including those with broader FGID exposure and mixed dementia outcomes, yielded a larger point estimate (OR = 1.38; 95% CI: 1.16 – 1.64), though this was accompanied by substantial heterogeneity (I² = 86%) and was rated as low certainty by GRADE. In the AD-specific analysis, IBS was associated with a 27% increase in the odds of AD (OR = 1.27; 95% CI: 1.08 – 1.50), with moderate heterogeneity (I² = 64%) and low-grade certainty.
The leave-one-out sensitivity analyses demonstrated that the primary and secondary pooled estimates were robust to the removal of any individual study, with the direction and magnitude of the association remaining consistent across all iterations. In contrast, the AD-specific estimate was sensitive to the individual exclusion of Konings et al. (2023) and Yuan et al. (2024), with statistical significance not maintained upon their removal, warranting cautious interpretation of this subtype finding.
Exploratory subgroup analyses applied to the secondary dementia pool revealed notable patterns. Cohort studies demonstrated smaller, statistically significant, and more consistent effects, whereas case-control studies showed larger but non-significant and highly heterogeneous estimates. This discrepancy may be attributed to inherent methodological limitations and the difficulty of establishing temporal relationships in case-control designs. Furthermore, an age-gap analysis revealed that case-control cohorts were approximately 15 – 20 years older than their longitudinal counterparts Table 1. Given that age is the primary driver of dementia incidence, this demographic shift likely amplifies the variance in effect sizes [41,42].
Moreover, studies conducted in Asian populations, comprising three studies, yielded a non-significant pooled estimate, suggesting that the IBS – dementia association may not be uniform across ethnicities and warrants further investigation in Asian cohorts. In contrast, the American and European subgroups each comprised a single study, precluding any meaningful regional interpretation for these populations. Similarly, the subgroup of studies employing extensive confounder adjustment – including genetic factors such as the APOE allele – produced a non-significant result, in contrast to the minimal and moderate adjustment subgroups, raising the possibility that part of the observed IBS – dementia association may be mediated or confounded by genetic susceptibility rather than IBS-specific pathophysiology.
Finally, re-running all pooled analyses using the REML estimator, a more conservative approach to between-study variance, produced wider confidence intervals and attenuated p-values, as expected. Despite this, neither the direction nor the overall statistical significance of the primary estimates was materially altered, supporting the robustness of the findings across heterogeneity modeling approaches.
Biological plausibility
Several biological mechanisms may underlie the observed association between IBS and dementia outcomes (all-cause and AD) in our analyses, with the link largely involving the brain – gut axis and shared pathological pathways [43]. In IBS, symptoms are driven by abnormal signaling within the bidirectional gut – brain axis, which integrates communication between the enteric nervous system (ENS), the central nervous system (CNS), and the gut microbiota [44]. Alterations in either the CNS or the GI tract can disrupt the gut microbiota, leading to dysbiosis and gut inflammation. These changes can signal back to the brain through vagal anti-inflammatory pathways [45], potentially contributing to altered brain function and neurodegeneration. In addition, IBS increases intestinal permeability, allowing bacterial products such as lipopolysaccharides (LPS) to enter circulation, thereby promoting neuroinflammation and increasing dementia risk [46].
Immune activation further supports this pathway: binding of LPS to Toll-like receptor 4 (TLR4) activates the NF-B pathway in CNS cells [47], triggering the release of proinflammatory cytokines such as IL-6, IL-1, and TNF- [48]. These cytokines not only influence enteric nerve activity but also stimulate the brain’s immune system, thereby promoting neuroinflammation, a key process in neurodegeneration and cognitive decline [49]. Cytokines have also been independently associated with increased dementia risk [46]. Moreover, studies [50,51] have shown strong pathological links between microbiome-derived neurotoxins and impaired synaptic signaling in AD. This process, combined with neuroinflammation, accelerates amyloid- deposition in memory-related regions such as the hippocampus and cerebral cortex [52].
Psychiatric and behavioral comorbidities provide additional explanatory pathways. IBS is commonly associated with depression, anxiety, and sleep disturbances [53], all established risk factors for dementia [54]. IBS patients also exhibit alterations in neurotransmitters such as serotonin, dopamine, GABA, and brain-derived neurotrophic factor (BDNF) [46], which regulate gut motility, visceral sensitivity, and brain function [48]. Finally, shared vascular and metabolic risk factors, including hypertension, diabetes, and obesity, may contribute to both GI dysfunction and cognitive decline [55].
Taken together, these multifaceted pathways suggest that the observed association likely reflects a cumulative, synergistic interplay between gut-derived neurotoxicity, systemic metabolic vulnerability, and the long-term cognitive burden of associated psychiatric comorbidities.
Limitations and strengths
This review has several limitations, many of which reflect concerns inherent to the existing evidence base on IBS and dementia risk. Potential surveillance or detection bias is a concern, as most studies relied on healthcare databases in which individuals with IBS are more likely to have frequent medical visits than the general population [13,56]. This increases the likelihood of cognitive assessment and earlier or more frequent dementia diagnosis, potentially inflating the observed association independent of a true biological link. Although studies adjusted for some confounders, residual bias related to healthcare access and diagnostic intensity cannot be excluded. Future research using designs that better control for healthcare utilization, such as matched cohorts with similar contact frequency or prospective population-based studies, is needed to clarify this effect.
Residual confounding also remains a concern. While most studies adjusted for basic demographic and clinical variables, several shared risk factors between IBS and dementia were not consistently controlled for Table 3. These include psychiatric comorbidities (e.g., depression and anxiety), sleep disturbances, medication burden (particularly psychotropic and anticholinergic drugs), and healthcare-seeking behavior. Given that these factors are strongly associated with both IBS and cognitive decline, they may partially explain the observed association [57,58,59,53,60]. Findings from exploratory subgroup analyses further support this interpretation, as studies with limited or moderate adjustment reported significant associations, whereas more extensively adjusted studies showed attenuated effects. Therefore, unmeasured or residual confounding cannot be ruled out, highlighting the need for future studies with more comprehensive adjustment and advanced analytical approaches, such as propensity score matching or causal inference methods, to better isolate the independent effect of IBS on dementia risk.
Reverse causation may also contribute to the observed association. Early neurodegenerative changes during the prodromal phase of dementia may influence GI function through autonomic dysregulation or behavioral changes, leading to IBS-like symptoms before formal dementia diagnosis and increased healthcare utilization, thereby raising the likelihood of an IBS diagnosis [61,62,63]. Consequently, the observed association may partly reflect early neurodegeneration rather than a causal effect of IBS on dementia risk. This issue is particularly relevant in retrospective database studies. It highlights the need for longitudinal designs with clear temporal separation between IBS onset and dementia diagnosis, as well as the application of lag-time analyses.
Variability in exposures and outcomes across included studies is an additional limitation. Although we restricted the primary analysis to IBS-exclusive exposure and all-cause dementia as the outcome – and the AD-specific analysis to IBS and AD only – this resulted in only three studies contributing to each analysis, constituting a limited evidence base.
Furthermore, the primary objective of Konings et al. (2023) was to investigate the association between IBS and Parkinson’s disease, with AD data reported as a secondary outcome [14]. Although this limitation was formally accounted for through downgrading of the certainty of evidence for indirectness in the AD-specific GRADE assessment [64], study power and reliability for the AD outcome remain inherently lower than in studies specifically designed to investigate it. Finally, three of the five included studies were conducted in Taiwan, which may limit generalizability to other populations.
This review also has several notable strengths. To our knowledge, it is the first meta-analysis to comprehensively synthesize evidence on the association between IBS and dementia. The large, pooled sample size (>750,000 participants) conferred substantial statistical power, and the included studies were of high methodological quality, with NOS scores of 8 to 9 out of 9, indicating low risk of bias. The review was conducted in accordance with the principles of the Cochrane Handbook and adhered to PRISMA reporting guidelines. Methodological rigor was further ensured through explicit handling of participant overlap to avoid double-counting (Section 2.5), referencing the excluded studies in the full-text screening and transparent reporting of all study-level inputs Table 3 to ensure reproducibility, and the use of two complementary meta-analytic models (DL and REML) to assess the stability of pooled estimates across heterogeneity modeling approaches.
Position in the relevant literature
The gut – brain axis seems not to be only a preclinical theory demonstrated in vitro or in animal models. Especially in neurodegeneration, many GI diseases have been linked to an increased risk of various neurodegenerative disorders, particularly AD. Among these GI disorders, IBD and NAFLD (non-alcoholic fatty liver disease) have attracted major interest, with a large number of observational studies exploring their association with AD and all-cause dementia and several meta-analyses already establishing this evidence [19,18,20]. Other GI diseases are now entering this line of investigation in observational studies but still lack strong and comprehensive meta-analytic evidence; for example, peptic ulcers, gastritis, and colorectal cancer [65,66,67,68].
Implications
This systematic review and meta-analysis suggest a potential association between IBS and higher odds of all-cause dementia and AD. However, the evidence derives from a limited number of observational studies. It is subject to substantial heterogeneity and potential biases, including surveillance bias, residual confounding, and reverse causation, which may partially or wholly account for the observed relationship.
Accordingly, IBS should not be construed as an independent causal risk factor for dementia based on current evidence. Rather, these hypothesis-generating findings highlight the importance of vigilance in patients with IBS who carry additional shared risk factors, such as depression, sleep disturbance, or extensive medication burden, where cumulative risk may be clinically meaningful. Current data do not justify changes in dementia-specific clinical management for IBS patients; however, they reinforce the value of comprehensive, longitudinal patient assessment in this population.
Future research should prioritize clarifying the direction and underlying mechanisms of the IBS-dementia association through well-designed prospective studies with clearly defined exposures and outcomes, adequate temporal separation between IBS onset and dementia diagnosis, lag-time analyses, and rigorous control for confounding. Separate evaluation of dementia subtypes, including AD, VaD, and non-AD dementia, is also needed, as pooling across subtypes may obscure clinically distinct pathophysiological pathways [69]. Mechanistic studies exploring the gut-brain axis, gut microbiota composition, and systemic neuroinflammation may further elucidate the biological basis of any true association.
There is also rationale for testing dual-purpose interventions, in which IBS treatments may simultaneously reduce dementia risk. Precedent exists in other chronic conditions, including heart failure and diabetes, where disease-directed interventions have demonstrated concurrent reductions in dementia risk [4,70]. For IBS specifically, probiotics have been evaluated as symptom relievers [71], although their effect on dementia risk remains unclear [72]. Interventions targeting gut health through probiotics, dietary modifications, or anti-inflammatory therapies could provide novel strategies for dementia prevention.
Conclusion
This meta-analysis provides the first synthesized evidence on the association between IBS and dementia, drawing on data from over 750,000 participants. Across analyses, IBS was consistently associated with statistically significantly higher odds of all-cause dementia and AD. These findings position IBS within a growing body of literature linking gastrointestinal disorders to neurodegenerative outcomes through shared gut-brain axis pathways.
However, the evidence remains observational, and the contributions of various types of bias cannot be excluded. IBS should not be regarded as an established causal risk factor for dementia based on current evidence, and no changes to dementia-specific clinical management are justified at this stage.
Well-designed prospective studies with IBS-specific exposure definitions, standardized dementia ascertainment, and rigorous control for confounders are needed to confirm and extend these findings. Mechanistic investigation of the gut-brain axis in IBS populations and subtype-specific dementia analyses represent equally important priorities. Finally, if the association is substantiated by future research, therapeutics targeting IBS pathophysiology may warrant evaluation as dual-purpose interventions, simultaneously managing IBS symptoms and potentially attenuating dementia risk.
Conflicts of Interest
They declare that they have no conflicts of interest to disclose.
Funding Source
No funding was received for this study.
Acknowledgments
None.
Institutional Review Board (IRB)
This article is a systematic review of published literature and does not contain any studies with human participants or animals performed by any of the authors. Ethics approval was not required for this systematic review.
Large Language Model
No use of artificial intelligence was made for the manuscript preparation.
Authors Contribution
MMH contributed to conceptualization, software, writing review and editing, visualization, writing the original draft, data curation, formal analysis, resources, and methodology. NA and JL contributed to conceptualization, software, validation, supervision, writing review and editing, visualization, writing the original draft, data curation, formal analysis, resources, project administration, and methodology. SJ and LW contributed to software, writing review and editing, visualization, writing the original draft, data curation, resources, and methodology. All authors read and approved the final manuscript.
Data Availability
The data generated in this study are available upon request from the corresponding author.
References
- Stephan B. C. M., Cochrane L., Kafadar A. H., Brain J., Burton E., Myers B., Brayne C., Naheed A., Anstey K. J., Ashor A. W., Siervo M.. Population attributable fractions of modifiable risk factors for dementia: a systematic review and meta-analysis. Lancet Healthy Longev. 2024;5(6):e406-e421. doi:10.1016/S2666-7568(24)00061-8 PMID: 38824956 PMCID: PMC11139659
- Payton N. M., Marseglia A., Grande G., Fratiglioni L., Kivipelto M., Backman L., Laukka E. J.. Trajectories of cognitive decline and dementia development: A 12-year longitudinal study. Alzheimers Dement. 2023;19(3):857-867. doi:10.1002/alz.12704 PMID: 35715929
- White L., Fishman P., Basu A., Crane P. K., Larson E. B., Coe N. B.. Medicare expenditures attributable to dementia. Health Serv Res. 2019;54(4):773-781. doi:10.1111/1475-6773.13134 PMID: 30868557 PMCID: PMC6606539
- Helal M. M., Almosilhy N. A., Hamam N. G., Abdelbaset M. A. A., Shelbaya A. N., Musse H. A. Y., Prasad A.. Sacubitril/Valsartan Reduces the Risk of All-Cause Dementia in Patients with Heart Failure: A Systematic Review and Meta-Analysis. Drugs Aging. 2025;42(10):907-920. doi:10.1007/s40266-025-01233-1 PMID: 40728824
- Megur A., Baltriukiene D., Bukelskiene V., Burokas A.. The Microbiota-Gut-Brain Axis and Alzheimer's Disease: Neuroinflammation Is to Blame?. Nutrients. 2020;13(1). doi:10.3390/nu13010037 PMID: 33374235 PMCID: PMC7824474
- Stadlbauer V., Engertsberger L., Komarova I., Feldbacher N., Leber B., Pichler G., Fink N., Scarpatetti M., Schippinger W., Schmidt R., Horvath A.. Dysbiosis, gut barrier dysfunction and inflammation in dementia: a pilot study. BMC Geriatr. 2020;20(1):248. doi:10.1186/s12877-020-01644-2 PMID: 32690030 PMCID: PMC7372911
- Qian X. H., Song X. X., Liu X. L., Chen S. D., Tang H. D.. Inflammatory pathways in Alzheimer's disease mediated by gut microbiota. Ageing Res Rev. 2021;68:101317. doi:10.1016/j.arr.2021.101317 PMID: 33711509
- Newton J. L., Hollingsworth K. G., Taylor R., El-Sharkawy A. M., Khan Z. U., Pearce R., Sutcliffe K., Okonkwo O., Davidson A., Burt J., Blamire A. M., Jones D.. Cognitive impairment in primary biliary cirrhosis: symptom impact and potential etiology. Hepatology. 2008;48(2):541-9. doi:10.1002/hep.22371 PMID: 18563843
- Shang Y., Widman L., Hagstrom H.. Nonalcoholic Fatty Liver Disease and Risk of Dementia: A Population-Based Cohort Study. Neurology. 2022;99(6):e574-e582. doi:10.1212/WNL.0000000000200853 PMID: 35831178 PMCID: PMC9442617
- Zhang B., Wang H. E., Bai Y. M., Tsai S. J., Su T. P., Chen T. J., Wang Y. P., Chen M. H.. Inflammatory bowel disease is associated with higher dementia risk: a nationwide longitudinal study. Gut. 2021;70(1):85-91. doi:10.1136/gutjnl-2020-320789 PMID: 32576641
- Huang K. Y., Wang F. Y., Lv M., Ma X. X., Tang X. D., Lv L.. Irritable bowel syndrome: Epidemiology, overlap disorders, pathophysiology and treatment. World J Gastroenterol. 2023;29(26):4120-4135. doi:10.3748/wjg.v29.i26.4120 PMID: 37475846 PMCID: PMC10354571
- Lovell R. M., Ford A. C.. Global prevalence of and risk factors for irritable bowel syndrome: a meta-analysis. Clin Gastroenterol Hepatol. 2012;10(7):712-721 e4. doi:10.1016/j.cgh.2012.02.029 PMID: 22426087
- Chen C. H., Lin C. L., Kao C. H.. Irritable Bowel Syndrome Is Associated with an Increased Risk of Dementia: A Nationwide Population-Based Study. PLoS One. 2016;11(1):e0144589. doi:10.1371/journal.pone.0144589 PMID: 26731277 PMCID: PMC4701489
- Konings B., Villatoro L., Van den Eynde J., Barahona G., Burns R., McKnight M., Hui K., Yenokyan G., Tack J., Pasricha P. J.. Gastrointestinal syndromes preceding a diagnosis of Parkinson's disease: testing Braak's hypothesis using a nationwide database for comparison with Alzheimer's disease and cerebrovascular diseases. Gut. 2023;72(11):2103-2111. doi:10.1136/gutjnl-2023-329685 PMID: 37620120
- Tung H., Lin C. H., Chen Y. M., Lee W. J., Chien L. S., Sun T. H., Liao C. S., Lin Y. Y., Hsiao T. H.. Utilizing apolipoprotein E genotypes and associated comorbidities for the assessment of the risk for dementia. Front Aging Neurosci. 2022;14:927656. doi:10.3389/fnagi.2022.927656 PMID: 36578446 PMCID: PMC9790994
- Yeh H. W., Chien W. C., Chung C. H., Hu J. M., Tzeng N. S.. Risk of psychiatric disorders in irritable bowel syndrome-A nationwide, population-based, cohort study. Int J Clin Pract. 2018;72(7):e13212. doi:10.1111/ijcp.13212 PMID: 29920876
- Yuan S., Dan L., Zhang Y., Wu J., Zhao J., Kivipelto M., Chen J., Ludvigsson J. F., Li X., Larsson S. C.. Digestive System Diseases, Genetic Risk, and Incident Dementia: A Prospective Cohort Study. Am J Prev Med. 2024;66(3):516-525. doi:10.1016/j.amepre.2023.10.017 PMID: 37918457
- Lu L. Y., Wu M. Y., Kao Y. S., Hung C. H.. Non-alcoholic fatty liver disease and the risk of dementia: A meta-analysis of cohort studies. Clin Mol Hepatol. 2022;28(4):931-932. doi:10.3350/cmh.2022.0259 PMID: 36064305 PMCID: PMC9597230
- Liu N., Wang Y., He L., Sun J., Wang X., Li H.. Inflammatory bowel disease and risk of dementia: An updated meta-analysis. Front Aging Neurosci. 2022;14:962681. doi:10.3389/fnagi.2022.962681 PMID: 36275009 PMCID: PMC9581261
- Peng T. R., Lin H. H., Yang L. J., Huang Y. Y., Wu T. W., Chao Y. C.. The impact of inflammatory bowel disease on dementia risk: a current systematic review and meta-analysis. Sci Rep. 2025;15(1):12852. doi:10.1038/s41598-025-96331-w PMID: 40229330 PMCID: PMC11997168
- Page M. J., McKenzie J. E., Bossuyt P. M., Boutron I., Hoffmann T. C., Mulrow C. D., Shamseer L., Tetzlaff J. M., Akl E. A., Brennan S. E., Chou R., Glanville J., Grimshaw J. M., Hrobjartsson A., Lalu M. M., Li T., Loder E. W., Mayo-Wilson E., McDonald S., McGuinness L. A., Stewart L. A., Thomas J., Tricco A. C., Welch V. A., Whiting P., Moher D.. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. Int J Surg. 2021;88:105906. doi:10.1016/j.ijsu.2021.105906 PMID: 33789826
- Abbas A., Hefnawy M. T., Negida A.. Meta-analysis accelerator: a comprehensive tool for statistical data conversion in systematic reviews with meta-analysis. BMC Med Res Methodol. 2024;24(1):243. doi:10.1186/s12874-024-02356-6 PMID: 39425031 PMCID: PMC11487830
- The Newcastle-Ottawa Scale (NOS) for Assessing the Quality of Non-Randomized Studies in Meta-Analysis.
- Cummings P.. The relative merits of risk ratios and odds ratios. Arch Pediatr Adolesc Med. 2009;163(5):438-45. doi:10.1001/archpediatrics.2009.31 PMID: 19414690
- Higgins J. P. T., Thomas J., Chandler J., Cumpston M., Li T., Page M. J.. Cochrane Handbook for Systematic Reviews of Interventions. Version 6.5 (updated August 2024). 2024.
- Veroniki A. A., Jackson D., Viechtbauer W., Bender R., Bowden J., Knapp G., Kuss O., Higgins J. P., Langan D., Salanti G.. Methods to estimate the between-study variance and its uncertainty in meta-analysis. Res Synth Methods. 2016;7(1):55-79. doi:10.1002/jrsm.1164 PMID: 26332144 PMCID: PMC4950030
- Sterne J. A., Gavaghan D., Egger M.. Publication and related bias in meta-analysis: power of statistical tests and prevalence in the literature. J Clin Epidemiol. 2000;53(11):1119-29. doi:10.1016/s0895-4356(00)00242-0 PMID: 11106885
- Prasad Manya. Introduction to the GRADE tool for rating certainty in evidence and recommendations. Clinical Epidemiology and Global Health. 2024;25. doi:10.1016/j.cegh.2023.101484
- Foroutan F., Guyatt G., Zuk V., Vandvik P. O., Alba A. C., Mustafa R., Vernooij R., Arevalo-Rodriguez I., Munn Z., Roshanov P., Riley R., Schandelmaier S., Kuijpers T., Siemieniuk R., Canelo-Aybar C., Schunemann H., Iorio A.. GRADE Guidelines 28: Use of GRADE for the assessment of evidence about prognostic factors: rating certainty in identification of groups of patients with different absolute risks. J Clin Epidemiol. 2020;121:62-70. doi:10.1016/j.jclinepi.2019.12.023 PMID: 31982539
- Amin Hussein S., Irfan Farhana, Karim Syed I., Almeshari Saif M., Aldosari Khaled A., Alzahrani Abdullah M., Almogbel Adnan T., Alfouzan Saad M., Alsaif Anas A.. The prevalence of irritable bowel syndrome among Saudi population in Riyadh by use of Rome IV criteria and self-reported dietary restriction. Saudi Journal of Gastroenterology. 2021;27(6):383-390. doi:10.4103/sjg.sjg_43_21
- Devanarayana N. M., Adhikari C., Pannala W., Rajindrajith S.. Prevalence of functional gastrointestinal diseases in a cohort of Sri Lankan adolescents: comparison between Rome II and Rome III criteria. J Trop Pediatr. 2011;57(1):34-9. doi:10.1093/tropej/fmq039 PMID: 20525779
- Lopez-Colombo A., Morgan D., Bravo-Gonzalez D., Montiel-Jarquin A., Mendez-Martinez S., Schmulson M.. The epidemiology of functional gastrointestinal disorders in Mexico: a population-based study. Gastroenterol Res Pract. 2012;2012:606174. doi:10.1155/2012/606174 PMID: 22474443 PMCID: PMC3313569
- Shivaji U. N., Ford A. C.. Prevalence of functional gastrointestinal disorders among consecutive new patient referrals to a gastroenterology clinic. Frontline Gastroenterol. 2014;5(4):266-271. doi:10.1136/flgastro-2013-100426 PMID: 28839783 PMCID: PMC5369735
- Smiliotopoulos T., Zampelas A., Houliaras G., Sgouros S. N., Michas G., Bamias G., Panagiotakos D., Cholopoulos N., Chrousos G. P., Roma E., Magriplis E.. Association of fructose consumption with prevalence of functional gastrointestinal disorders manifestations: results from Hellenic National Nutrition and Health Survey (HNNHS). Br J Nutr. 2023;130(11):1961-1972. doi:10.1017/S0007114523001198 PMID: 37197939 PMCID: PMC10630147
- Huang K. Y., Yu Z. Z., Tu J. J., Tang X. Y., Huang J. M., Lu T. M., Lu Y. Q., Huang M. C., Zhou J., Maier A. B., Ye K. X., Yang Z., Feng L., Lu G. D.. Positive association between constipation and mild cognitive impairment in elders: A cross-sectional study. Medicine (Baltimore). 2024;103(40):e39943. doi:10.1097/MD.0000000000039943 PMID: 39465768 PMCID: PMC11460931
- Wang F., Fei M., Hu W. Z., Wang X. D., Liu S., Zeng Y., Zhang J. H., Lv Y., Niu J. P., Meng X. L., Cai P., Li Y., Gang B. Z., You Y., Lv Y., Ji Y.. Prevalence of Constipation in Elderly and Its Association With Dementia and Mild Cognitive Impairment: A Cross-Sectional Study. Front Neurosci. 2021;15:821654. doi:10.3389/fnins.2021.821654 PMID: 35140587 PMCID: PMC8819140
- Adewuyi E. O., O'Brien E. K., Porter T., Laws S. M.. Relationship of Cognition and Alzheimer's Disease with Gastrointestinal Tract Disorders: A Large-Scale Genetic Overlap and Mendelian Randomisation Analysis. Int J Mol Sci. 2022;23(24). doi:10.3390/ijms232416199 PMID: 36555837 PMCID: PMC9784325
- Berrill J. W., Gallacher J., Hood K., Green J. T., Matthews S. B., Campbell A. K., Smith A.. An observational study of cognitive function in patients with irritable bowel syndrome and inflammatory bowel disease. Neurogastroenterol Motil. 2013;25(11):918-e704. doi:10.1111/nmo.12219 PMID: 23981191
- Ding W., Chen L., Pei B., Gao D., Xia J., Li X., Wang Y.. Causal link between mental disorders and gastrointestinal diseases: a Mendelian randomization study. Front Endocrinol (Lausanne). 2025;16:1288619. doi:10.3389/fendo.2025.1288619 PMID: 40331137 PMCID: PMC12052545
- Rijnhart J. J. M., Rabbers A., Rizzuto S., Howard A. M., Valente M. J.. An umbrella review reveals that control variables are rarely considered as a source of heterogeneity in systematic reviews of observational studies. J Clin Epidemiol. 2025;184:111826. doi:10.1016/j.jclinepi.2025.111826 PMID: 40368221
- Cleveland M. L.. Preserving Cognition, Preventing Dementia. Clin Geriatr Med. 2020;36(4):585-599. doi:10.1016/j.cger.2020.06.003 PMID: 33010896
- Tari A. R., Walker T. L., Huuha A. M., Sando S. B., Wisloff U.. Neuroprotective mechanisms of exercise and the importance of fitness for healthy brain ageing. Lancet. 2025;405(10484):1093-1118. doi:10.1016/S0140-6736(25)00184-9 PMID: 40157803
- Daulatzai M. A.. Chronic functional bowel syndrome enhances gut-brain axis dysfunction, neuroinflammation, cognitive impairment, and vulnerability to dementia. Neurochem Res. 2014;39(4):624-44. doi:10.1007/s11064-014-1266-6 PMID: 24590859
- Mayer E. A., Ryu H. J., Bhatt R. R.. The neurobiology of irritable bowel syndrome. Mol Psychiatry. 2023;28(4):1451-1465. doi:10.1038/s41380-023-01972-w PMID: 36732586 PMCID: PMC10208985
- Raskov H., Burcharth J., Pommergaard H. C., Rosenberg J.. Irritable bowel syndrome, the microbiota and the gut-brain axis. Gut Microbes. 2016;7(5):365-83. doi:10.1080/19490976.2016.1218585 PMID: 27472486 PMCID: PMC5046167
- Krstic D., Madhusudan A., Doehner J., Vogel P., Notter T., Imhof C., Manalastas A., Hilfiker M., Pfister S., Schwerdel C., Riether C., Meyer U., Knuesel I.. Systemic immune challenges trigger and drive Alzheimer-like neuropathology in mice. J Neuroinflammation. 2012;9:151. doi:10.1186/1742-2094-9-151 PMID: 22747753 PMCID: PMC3483167
- Warren A., Nyavor Y., Zarabian N., Mahoney A., Frame L. A.. The microbiota-gut-brain-immune interface in the pathogenesis of neuroinflammatory diseases: a narrative review of the emerging literature. Front Immunol. 2024;15:1365673. doi:10.3389/fimmu.2024.1365673 PMID: 38817603 PMCID: PMC11137262
- Buckley M. M., O'Mahony S. M., O'Malley D.. Convergence of neuro-endocrine-immune pathways in the pathophysiology of irritable bowel syndrome. World J Gastroenterol. 2014;20(27):8846-58. doi:10.3748/wjg.v20.i27.8846 PMID: 25083058 PMCID: PMC4112880
- Ishioh M., Nozu T., Okumura T.. Brain Neuropeptides, Neuroinflammation, and Irritable Bowel Syndrome. Digestion. 2024;105(1):34-39. doi:10.1159/000533275 PMID: 37673052
- Li B., He Y., Ma J., Huang P., Du J., Cao L., Wang Y., Xiao Q., Tang H., Chen S.. Mild cognitive impairment has similar alterations as Alzheimer's disease in gut microbiota. Alzheimers Dement. 2019;15(10):1357-1366. doi:10.1016/j.jalz.2019.07.002 PMID: 31434623
- Zhong S. R., Kuang Q., Zhang F., Chen B., Zhong Z. G.. Functional roles of the microbiota-gut-brain axis in Alzheimer's disease: Implications of gut microbiota-targeted therapy. Transl Neurosci. 2021;12(1):581-600. doi:10.1515/tnsci-2020-0206 PMID: 35070442 PMCID: PMC8724360
- Nagpal R., Neth B. J., Wang S., Craft S., Yadav H.. Modified Mediterranean-ketogenic diet modulates gut microbiome and short-chain fatty acids in association with Alzheimer's disease markers in subjects with mild cognitive impairment. EBioMedicine. 2019;47:529-542. doi:10.1016/j.ebiom.2019.08.032 PMID: 31477562 PMCID: PMC6796564
- Staudacher H. M., Black C. J., Teasdale S. B., Mikocka-Walus A., Keefer L.. Irritable bowel syndrome and mental health comorbidity - approach to multidisciplinary management. Nat Rev Gastroenterol Hepatol. 2023;20(9):582-596. doi:10.1038/s41575-023-00794-z PMID: 37268741 PMCID: PMC10237074
- Richmond-Rakerd L. S., D'Souza S., Milne B. J., Caspi A., Moffitt T. E.. Longitudinal Associations of Mental Disorders With Dementia: 30-Year Analysis of 1.7 Million New Zealand Citizens. JAMA Psychiatry. 2022;79(4):333-340. doi:10.1001/jamapsychiatry.2021.4377 PMID: 35171209 PMCID: PMC8851362
- Richards E. M., Li J., Stevens B. R., Pepine C. J., Raizada M. K.. Gut Microbiome and Neuroinflammation in Hypertension. Circ Res. 2022;130(3):401-417. doi:10.1161/CIRCRESAHA.121.319816 PMID: 35113664 PMCID: PMC8852773
- Tornkvist N. T., Aziz I., Whitehead W. E., Sperber A. D., Palsson O. S., Hreinsson J. P., Simren M., Tornblom H.. Health care utilization of individuals with Rome IV irritable bowel syndrome in the general population. United European Gastroenterol J. 2021;9(10):1178-1188. doi:10.1002/ueg2.12153 PMID: 34599559 PMCID: PMC8672084
- Bai C., Feng T., Huang N., Wang Q., Chen J., Zhao D., Chen B., Li Y., Chen J., Guo X., Wang J., Zhao Z., Liang B., Huang T., Yuan J.. The association between depression, anxiety, sleep disturbances and dementia: a prospective cohort study of 350,186 adults. BMC Neurol. 2026;26(1):105. doi:10.1186/s12883-026-04676-0 PMID: 41612219 PMCID: PMC12903354
- Fond G., Loundou A., Hamdani N., Boukouaci W., Dargel A., Oliveira J., Roger M., Tamouza R., Leboyer M., Boyer L.. Anxiety and depression comorbidities in irritable bowel syndrome (IBS): a systematic review and meta-analysis. Eur Arch Psychiatry Clin Neurosci. 2014;264(8):651-60. doi:10.1007/s00406-014-0502-z PMID: 24705634
- Grover M., Kolla B. P., Pamarthy R., Mansukhani M. P., Breen-Lyles M., He J. P., Merikangas K. R.. Psychological, physical, and sleep comorbidities and functional impairment in irritable bowel syndrome: Results from a national survey of U.S. adults. PLoS One. 2021;16(1):e0245323. doi:10.1371/journal.pone.0245323 PMID: 33444383 PMCID: PMC7808669
- Ungvari Z., Fekete M., Lehoczki A., Munkacsy G., Fekete J. T., Zabo V., Purebl G., Varga P., Ungvari A., Gyorffy B.. Sleep disorders increase the risk of dementia, Alzheimer's disease, and cognitive decline: a meta-analysis. Geroscience. 2025;47(3):4899-4920. doi:10.1007/s11357-025-01637-2 PMID: 40214959 PMCID: PMC12181552
- Fereshtehnejad S. M., Lokk J.. Healthcare Complexities in Neurodegenerative Proteinopathies: A Narrative Review. Healthcare (Basel). 2025;13(15). doi:10.3390/healthcare13151873 PMID: 40805906 PMCID: PMC12345698
- Pellegrini C., Daniele S., Antonioli L., Benvenuti L., D'Antongiovanni V., Piccarducci R., Pietrobono D., Citi V., Piragine E., Flori L., Ippolito C., Segnani C., Palazon-Riquelme P., Lopez-Castejon G., Martelli A., Colucci R., Bernardini N., Trincavelli M. L., Calderone V., Martini C., Blandizzi C., Fornai M.. Prodromal Intestinal Events in Alzheimer's Disease (AD): Colonic Dysmotility and Inflammation Are Associated with Enteric AD-Related Protein Deposition. Int J Mol Sci. 2020;21(10). doi:10.3390/ijms21103523 PMID: 32429301 PMCID: PMC7278916
- Zabihi S., Bestwick J. P., Jitlal M., Bothongo P. L., Zhang Q., Carter C., Roche M., Morgan-Trimmer S., Birks Y., Wilberforce M., Dobson R., Noyce A. J., Robson J., Walter F. M., Cooper C., Marshall C. R.. Early presentations of dementia in a diverse population. Alzheimers Dement. 2025;21(2):e14578. doi:10.1002/alz.14578 PMID: 40008622 PMCID: PMC11863067
- Guyatt G. H., Oxman A. D., Vist G. E., Kunz R., Falck-Ytter Y., Alonso-Coello P., Schunemann H. J., GRADE Working Group. GRADE: an emerging consensus on rating quality of evidence and strength of recommendations. BMJ. 2008;336(7650):924-6. doi:10.1136/bmj.39489.470347.AD PMID: 18436948 PMCID: PMC2335261
- Chiu R. H., Lu S. R., Liang F. W., Lin C. L., Ho C. H., Hsiao P. C.. Risk of dementia in colorectal cancer patients receiving chemotherapy: A nationwide cohort study. Cancer Epidemiol. 2022;76:102083. doi:10.1016/j.canep.2021.102083 PMID: 34920341
- Choi H. G., Soh J. S., Lim J. S., Sim S. Y., Jung Y. J., Lee S. W.. Peptic ulcer does not increase the risk of dementia: A nested case control study using a national sample cohort. Medicine (Baltimore). 2020;99(33):e21703. doi:10.1097/MD.0000000000021703 PMID: 32872044 PMCID: PMC7437840
- Kang D. W., Lee J. W., Park M. Y., Kim S. H., Um Y. H., Wang S. M., Lee C. U., Lim H. K.. Impact of Helicobacter pylori eradication on age-specific risk of incident dementia in patients with peptic ulcer disease: a nationwide population-based cohort study. Geroscience. 2025;47(1):1161-1174. doi:10.1007/s11357-024-01284-z PMID: 39129052 PMCID: PMC11872846
- Momtaz Y. A., Hamid T. A., Ibrahim R.. Gastritis May Boost Odds of Dementia. Am J Alzheimers Dis Other Demen. 2014;29(5):452-6. doi:10.1177/1533317513518654 PMID: 24408749 PMCID: PMC10852707
- Karantzoulis S., Galvin J. E.. Distinguishing Alzheimer's disease from other major forms of dementia. Expert Rev Neurother. 2011;11(11):1579-91. doi:10.1586/ern.11.155 PMID: 22014137 PMCID: PMC3225285
- Kuate Defo A., Bakula V., Pisaturo A., Labos C., Wing S. S., Daskalopoulou S. S.. Diabetes, antidiabetic medications and risk of dementia: A systematic umbrella review and meta-analysis. Diabetes Obes Metab. 2024;26(2):441-462. doi:10.1111/dom.15331 PMID: 37869901
- Zhang T., Zhang C., Zhang J., Sun F., Duan L.. Efficacy of Probiotics for Irritable Bowel Syndrome: A Systematic Review and Network Meta-Analysis. Front Cell Infect Microbiol. 2022;12:859967. doi:10.3389/fcimb.2022.859967 PMID: 35433498 PMCID: PMC9010660
- Santiago J. A., Potashkin J. A.. The Impact of Disease Comorbidities in Alzheimer's Disease. Front Aging Neurosci. 2021;13:631770. doi:10.3389/fnagi.2021.631770 PMID: 33643025 PMCID: PMC7906983